Abstract
The spread of pandemic viruses and invasive species can be catastrophic for human societies and natural ecosystems. SARS-CoV-2 demonstrated that the speed of our response is critical, as each day of delay permitted exponential growth and dispersion of the virus. Here we propose a global Nucleic Acid Observatory (NAO) to monitor the relative frequency of everything biological through comprehensive metagenomic sequencing of waterways and wastewater. By searching for divergences from historical baseline frequencies at sites throughout the world, NAO could detect any virus or invasive organism undergoing exponential growth whose nucleic acids end up in the water, even those previously unknown to science. Continuously monitoring nucleic acid diversity would provide us with universal early warning, obviate subtle bioweapons, and generate a wealth of sequence data sufficient to transform ecology, microbiology, and conservation. We call for the immediate construction of a global NAO to defend and illuminate planetary health.
Keywords: Metagenomic sequencing, wastewater, environmental DNA, biosecurity, ecology, conservation
Introduction
The SARS-CoV-2 pandemic has demonstrated our profound vulnerability to exponentially spreading viruses. Even though the first cases were estimated to have occurred in November or possibly October1, they were not detected until December2. Had governments acted just a few weeks earlier, the virus may have been excluded from many more countries or even eradicated before becoming a global pandemic, as was accomplished for SARS-CoV-1 in 20033 and Ebola in 2014-20154,5. Notably, those places that responded swiftly and aggressively to SARS-CoV-2 fared best early on, including New Zealand, Vietnam, China, South Korea, and Australia6. When an enemy can spread exponentially, an early detection and response requires exponentially fewer resources to achieve containment and eradication.
The same logic holds for invasive species, which devastate natural ecosystems and cause immense damage to the agriculture and forestry sectors7. Invasions were estimated to cost an inflation-adjusted $54 billion per year in the United States8 and a minimum of $47-$163 billion worldwide, with costs roughly doubling every six years from 1970-20179. The U.S. and China have the most to lose from future invasions10.
Analyses of containment and eradication programs targeting 136 invasive plants11,12 and 130 insects13 consistently found that the larger the geographic area of the infestation, the lower the odds of success 14. The ease of detecting the target pest was one of the most critical factors associated with eradication success.
These dynamics underscore the importance of early warning systems to contain and eradicate biological invasives. Pandemic viruses and pests share one critical feature with all other living things: their genomes are made of nucleic acids. In every region of the world, these fragments of DNA and RNA are washed into local bodies of water, where new techniques have begun to permit their reliable detection15,16.
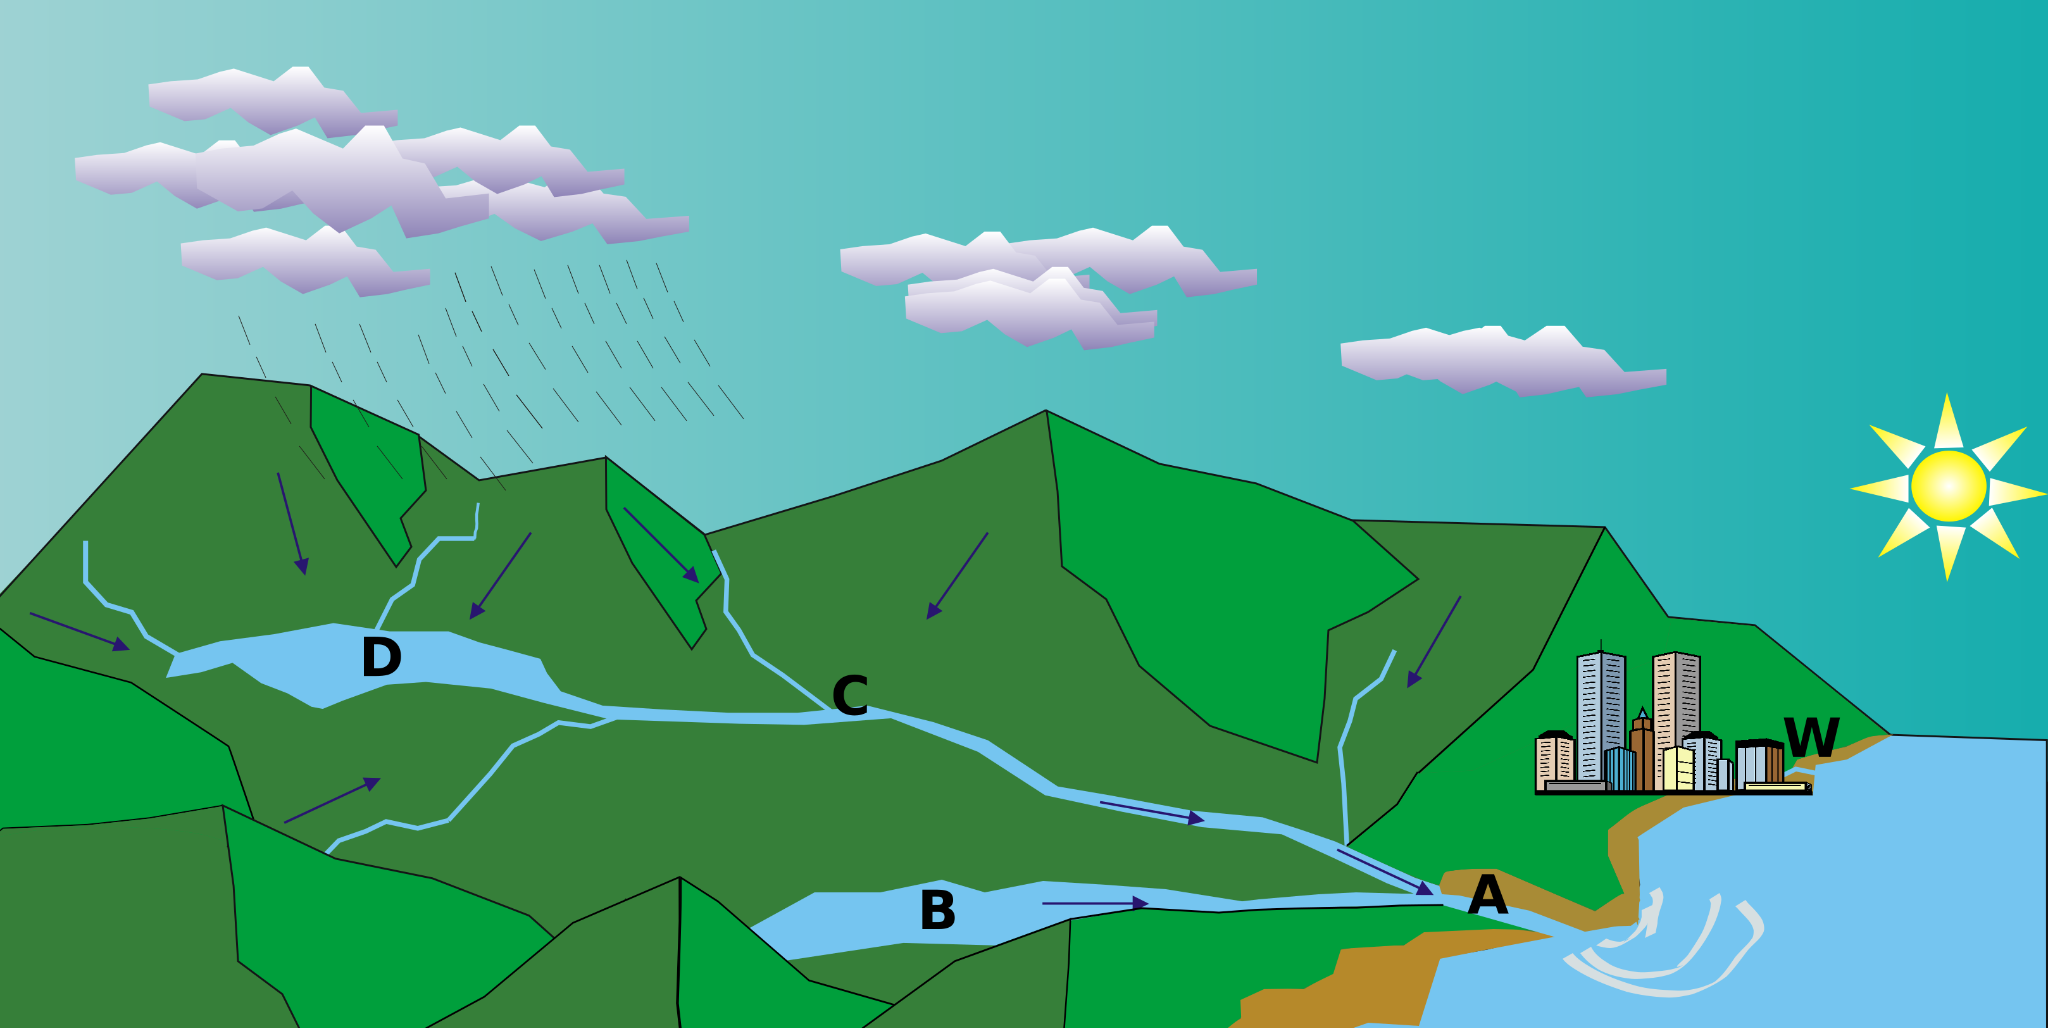
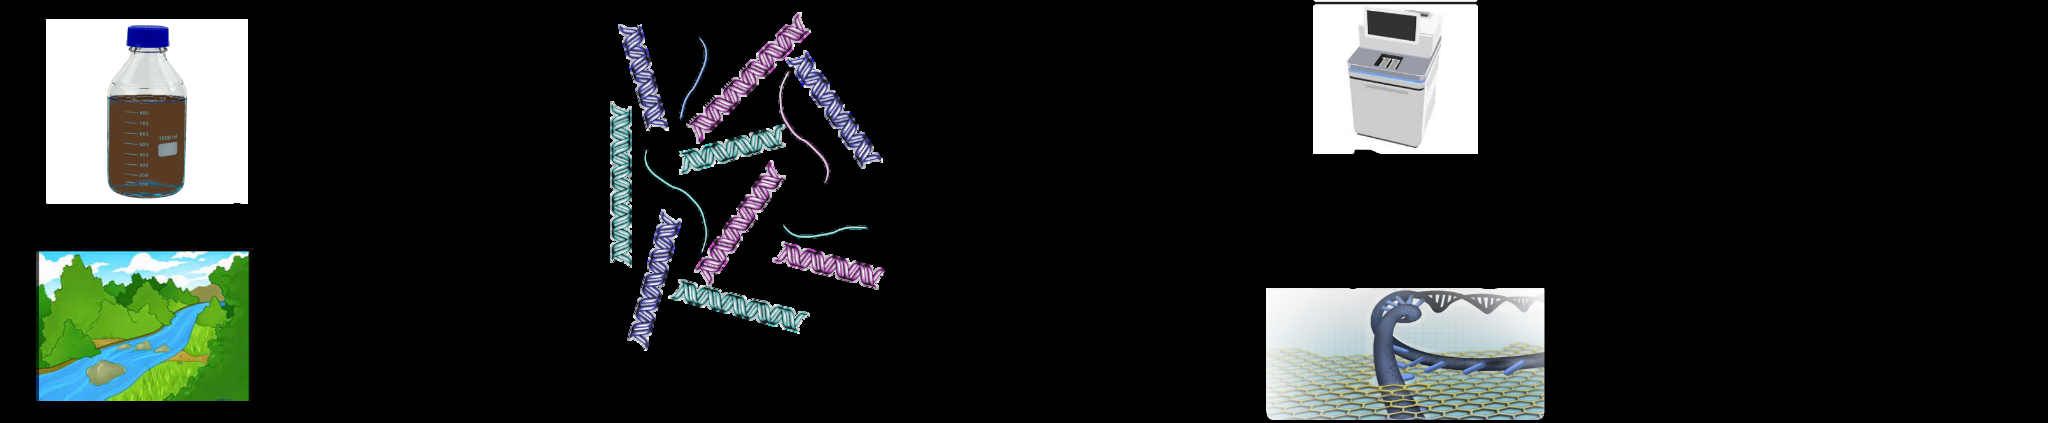
SARS-CoV-2 has been detected in wastewater days before the first clinical cases being reported in surrounding communities17; wastewater sequencing has even detected and identified variants of the virus18–21 as well as many other viruses22–29 and antibiotic resistance genes30. Laboratories using metagenomic sequencing to analyze samples of river water have successfully detected signatures of species from throughout the associated watershed15, including terrestrial macrofauna16, and can distinguish between closely related species31 (Fig. 1). Even low-throughput metagenomic sequencing can detect spiked-in samples of pathogen DNA in less than 8 hours32,33. While most of these studies suggest that shotgun metagenomics alone has a higher limit of detection relative to quantitative PCR, there are exceptions in both environmental 34,35 and clinical samples36,37, and it is widely agreed that performing parallel unbiased and target-specific amplification before sequencing can confer qPCR-level sensitivity to specific sequences of interest while maintaining the ability to detect previously unknown agents38,39 or strains with mutations in commonly used RT-PCR primer binding sites22. Therefore, a system that combines unbiased amplification to detect previously unknown or foreign biological agents with more sensitive monitoring of particular species of concern from both wastewater and natural waterways appears to offer the best of both worlds (Fig. 2).
The case study dramatizing the importance of early detection used a much older technology: in 2013, Israel’s poliovirus-specific environmental monitoring program detected a nascent outbreak in wastewater samples from the town of Rahat using plaque assays and swiftly initiated mass oral vaccination, eliminating the virus before even a single child came down with paralytic symptoms40. Today, we have the potential to detect any virus or invasive species, even novel pandemic-class agents unknown to science, through the comprehensive metagenomic sequencing of waterways. Here we propose to build a Nucleic Acid Observatory to continuously monitor the global environment for past, present, and future pandemic viruses and invasive pests.
Figure 1 | Watershed and wastewater metagenomic sequencing can detect pandemic viruses, invasive species, and engineered genes while monitoring the populations of different species. Sampling at site A detects nucleic acids from the entire watershed, including agricultural and rural regions; upstream sampling at B, C, D can pinpoint sources.
Sequencing at M monitors the health of the marine ecosystem, while wastewater sequencing at W can sensitively detect human-specific pathogens. Figure 2 | Overview of sample processing, sequencing, and analysis. Processed samples are sequenced with and without targeted amplification of known agents. Unbiased sequencing can detect any exponential threat by monitoring the abundance of different k-mer fragments over time. The k-mers comprising any exponentially growing biological agent will increase in frequency as a group, permitting identification of the agent. Once identified, the threat can be added to the list of targets for sequence-specific amplification or enrichment, which will maximize sensitivity and immediately determine whether the new threat is present at any other sites of the Observatory. Targeted sequencing of stored samples could determine the time of introduction to any given site, aiding subsequent investigations. Alternative sequence-specific detection methods such as RT-PCR or LAMP may be used as appropriate.
Biodefense
The world’s demonstrated vulnerability to SARS-CoV-2 appears reason enough to invest in a comprehensive early-warning system. The United States has lost more citizens to the pandemic than it has in all military conflicts in the past century, yet it devotes less than 1% of its defense budget to biodefense41.
Indeed, not a single line of the nearly $700 billion 2020 defense appropriations bill mentioned anything biological42. Most of the small investment in biosecurity is focused on anthrax and other chemical weapon equivalents, whose theoretical worst-case tolls are orders of magnitude lower than those of pandemics and other autonomously spreading pathogens while being far less accessible due to the need for a sophisticated aerosol delivery system43,44.
Agriculture and natural ecosystems are equally, if not more, susceptible to autonomous pathogens. Historical fungal blights afflicting staple crops have led to massive famines in the past, most infamously in Ireland; many still cause tremendous losses today45. Concerted outbreaks afflicting multiple crops could be devastating for the world, especially given our increasing reliance on near-monocultures46. Livestock can also suffer: the ~1% case fatality rate of SARS-COV-2 is dwarfed by the 80-100% lethality of African swine fever in pigs47. An estimated 13-27% of all the world’s swine were lost to the 2018-2019 outbreak48.
For the moment, we largely lack the capacity to engineer biological agents capable of spreading invasively in the wild. The sole current exception, CRISPR-based gene drive technologies capable of editing populations of sexually reproducing organisms49, underscores the critical importance of a Nucleic Acid Observatory. Relative to viruses, gene drive systems are slower to spread and far more reliably countered50, as any given example can be overwritten by building and releasing a corresponding "immunizing reversal" drive system49,51. Even so, a harmful drive system could cause tremendous damage if permitted to grow exponentially; for some species, individuals with relevant technical skills could build and release such a construct single-handedly. Genome sequencing, whether of at-risk organisms or of metagenomes, appears to be the only reliable method of detecting engineered gene drive systems in the environment, and is therefore required for defense. Despite defense projects aimed at sensitively detecting engineered sequences in the environment52, no such system has been constructed at scale.
The possibility that individuals could single-handedly edit wild species had never been previously imagined before the invention of CRISPR-based gene drive, raising the unsettling possibility that we may stumble upon similarly unanticipated ways of engineering exponential spread. Even if the unknown unknowns prove harmless, a number of emerging threats are clearly visible today. For example, several current avenues of research promise to identify publicly53–55 and reveal ways to enhance and weaponize
Understanding Factors Governing
transmissibility57 or immune evasion58. Such agents would be less readily countered than would a gene drive construct59,60. Constructing an early warning system could simultaneously deter attack and maximize the time available for defenders to develop and apply suitable countermeasures.
To be effective, monitoring systems should not rely on any particular phenotype, symptom profile, or sequence to be present in future natural outbreaks or bioweapons. Since very few viruses have been sequenced to date, detection systems based on known sequences may not be sensitive to future pandemic agents61. For example, multiplexed CRISPR-based diagnostics capable of detecting all current human pathogens have tremendous medical potential62, but they could miss future zoonotic agents. Older systems attempting to detect aerosolized agents63 are similarly limited to known threats, although they could be upgraded by applying metagenomic sequencing. Most importantly, any remotely sophisticated adversary would deliberately engineer a biological weapon to lack the sequences detected by any pre-existing diagnostics and defenses.
In contrast, the only way to evade detection by shotgun metagenomic sequencing would be to somehow engineer a pathogen that entirely lacks sequence-amenable nucleic acids in its genome. Since all known living organisms possess genomes that can be sequenced with current technologies and all nucleic acids present in the environment are thought to be detectable in the water15,64, analyses searching for sequences diverging from historical baselines could sensitively detect nucleic acids from any biological construct exhibiting exponential growth. As such, a Nucleic Acid Observatory could reliably detect any and all subtle pandemic viruses, bioweapons, or other autonomous biological agents targeting humans, agriculture, or natural ecosystems within days or weeks of introduction.
Conservation
Invasive species are a primary cause of extinction of native species around the world65–67. Any waterway-based metagenomic sequencing system capable of reliably detecting a pandemic virus or CRISPR-based gene drive system in a terrestrial organism living in the associated watershed should also be capable of detecting invasive species. Consider forests. The American chestnut was once the most common tree in North America; thanks to the invasive chestnut blight, it is nearly extinct. Other species have been devastated or are threatened by other agents such as Dutch elm disease, the emerald ash borer, Asian longhorned beetle, hemlock woolly adelgid, the gypsy moth, Rapid Ohi’a Death, and more14,68,69. Even farmed trees are vulnerable; citrus greening disease has destroyed the orange industry in Florida, costing the state 34,000 jobs70. Assuming that future invasions would be equivalently costly10, the NAO could nearly pay for itself simply by enabling detection and eradication before they become widespread.
In addition to detecting invasive species, environmental DNA in rivers can provide information on the abundance of native species, including terrestrial mammals71. Such methods have helped scientists monitor numerous endangered species72–75, including those that are challenging to track76,77. In aquatic environments, metagenomic sequencing was demonstrated to be superior to all conventional methods for species tracking78. A weekly census of species occupancy and abundance in environments could direct conservation resources more efficiently, and may be particularly relevant to assisting species imperiled by climate change.
A key question is whether shotgun metagenomics can monitor abundance as effectively as the metabarcoding more commonly used to detect particular marker genes in eukaryota. Recent studies suggest that the metagenomics approaches commonly used by microbial ecologists are nearly as sensitive79. In addition, sufficiently deep metagenomic sequencing permits the direct monitoring of genetic diversity within populations, which is widely considered a better metric of species robustness than simple abundance80–84.
Science
The environmental sequencing of waterways has revealed that a large fraction to an overwhelming majority of sequences of nucleic acids in the environment are not found in current repositories27,85–87. In other words, much of life remains entirely unknown to us.
The scientific benefits of sequencing most of the remaining genetic diversity on Earth would extend far beyond conservation; indeed, they are difficult to describe without superlatives. Microbial and macrofaunal ecology, population genetics, geochemistry, evolutionary biology, and many more disciplines would be utterly transformed by such a treasure trove of data. Virtually all of the tangible benefits arising from biological research were enabled or inspired by natural systems, from vaccines to antibiotics, aspirin to insulin, and genetic engineering, DNA sequencing, PCR and CRISPR. Sequence most living things, and we can reasonably expect to discover many more tools that may become pillars of biotechnology and medicine.
While the anticipated scientific benefits of a one-time spatial survey of genomic abundance and diversity would be staggering, the Nucleic Acid Observatory would go beyond a single snapshot by monitoring genetic diversity throughout the world for an extended time88. Large spatial and temporal series are considered the gold standard for ecological and evolutionary studies, but are seldom collected due to the considerable expense relative to the typically small funding streams available for ecological studies. For example, the entire U.S. National Ecological Observatory Network was funded for $434 million89, which is a rounding error compared to the cost of COVID-19 ($5.73 trillion in relief bills passed by the U.S. Congress alone) and the $3.2-$16 trillion estimated cost of the pandemic 90,91. If implemented in an even moderately standardized manner, the NAO would generate far and away the most comprehensive and useful ecological dataset ever collected.
Technical Options
On a high level, the Nucleic Acid Observatory would involve extracting nucleic acids from filters or concentrated water samples from rivers and sewage systems at many sites throughout the world, selectively amplifying any known sequences of concern that may be present, conducting metagenomic sequencing to generate snapshots of the nucleic acid diversity on that day27, performing bioinformatic analyses to screen for novel sequences that have become exponentially more common relative to past snapshots, then assembling those sequences to identify the responsible organism or virus. Each of these steps can be economically and technically optimized.
Experimental Strategies
There are a variety of sampling methods that should be evaluated to determine which combinations are optimal for cost-effectiveness at different depths and breadths of threat coverage. Sample collection routinely employs artificial filters, generally developed for medical use and adapted to environmental purposes to concentrate nucleic acids64,92–94. More recent developments include the use of passive samplers to which eDNA will bind95 and aquatic organisms that naturally concentrate exogenous DNA that can be cultivated and harvested, such as filter-feeding sponges, shellfish and other organisms96, with the caveat that concentrations of bivalves may or may not substantially reduce the total concentration of eDNA97,98 and the net dynamics of eDNA movement determinants in marine environments remain to be established98. Finally, the use of settlement plates and centrifugal concentration of water samples may also have utility in some settings64. Each approach has strengths and limitations. Artificial filters require periodic replacement and once samples are collected then storage may be challenging. Some automation of both approaches has been achieved in field deployable remote automated underwater vehicles and there is significant capacity to improve this further99. Living filters such as mussels and other shellfish also concentrate exogenous nucleic acids and may be suitable for monitoring, including some in pre-existing populations, but this concept remains very much in early development96,100.
Once concentrated and extracted, nucleic acids are typically selectively or indiscriminately amplified by one of several methods101. For the Nucleic Acid Observatory, selective and unbiased approaches would be used in parallel to sensitively detect known sequences of interest while retaining the ability to identify previously unknown sequences that are exponentially increasing in abundance.
Different combinations of sampling, filtering, extraction, and amplification methods differ in which source organisms and sequences they are able to detect15,18,19,102–104. Therefore several distinct methods should be used at each testing site to ensure coverage of diverse threats. For example, three protocols may be used to target DNA from cellular organisms, viral and cell-free DNA, and viral and cell-free RNA.
Once amplified, samples may be shotgun sequenced by short or long-read sequencing, or both. Short-read sequencing based on Illumina technology is currently the most cost-effective on a per-read basis and consequently offers the greatest sensitivity, meaning it may be optimal for wastewater105. Nanopore sequencing offers much longer reads, superior recognition of gene drive systems and other constructs that combine elements normally never found adjacent to one another, and the ability to sequence DNA containing non-standard bases such as the newly discovered aminoadenine106–108. It can also sequence RNA directly, offering a means of monitoring RNA viruses without reverse transcription109,110. Recent advances enabling adaptive nanopore sequencing to better detect low-abundance samples may allow it to approach the sensitivity of short-read sequencing111. For all methods, samples from different sites can be shipped to a single central laboratory located elsewhere, barcoded, and subjected to pooled sequencing112. Nanopore sequencing, which offers portable sequencing in remote environments, may be required in any areas where sample stability and logistics do not permit shipment.
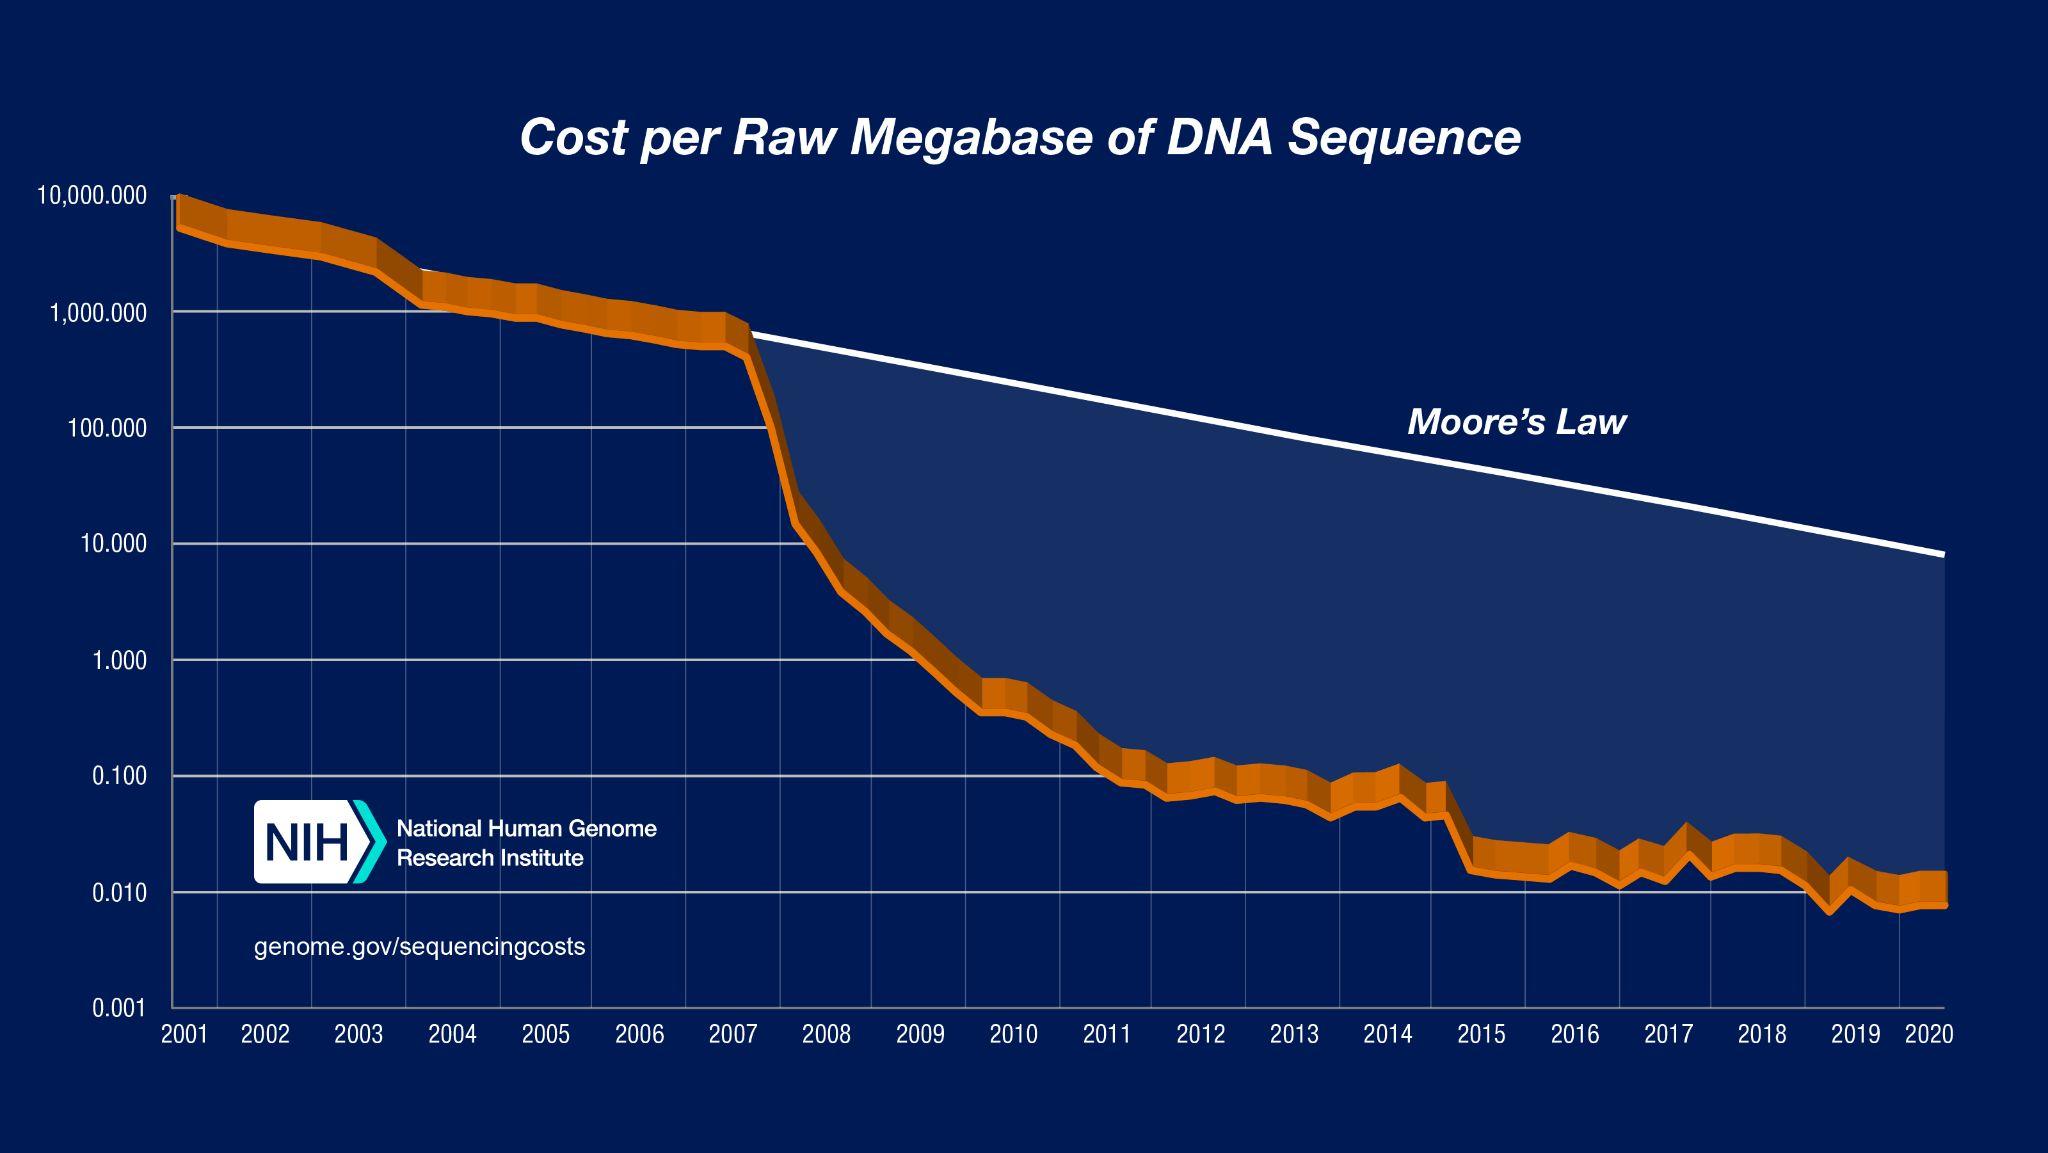
Sequencing costs for both short and long-read sequencing have dropped considerably faster than Moore's Law (Fig. 3), a trend that looks set to continue given a variety of early-stage alternatives to current practice113. Therefore, the efficacy of a NAO can reasonably be expected to grow with time.
Figure 3 | Historical cost of sequencing one million base pairs of DNA. Adopted from NHGRI114.
Computational Strategies
Once samples are collected and sequenced, the resulting data must then be bioinformatically analyzed and interpreted. Distinct strategies are needed to monitor known versus unknown threats. Known threats—agents or genetic elements with known sequences—can be detected by mapping sequencing reads (or their protein translations) to databases of reference sequences115–117 or by using classification, prediction, or screening methods derived from such databases116,118. Such databases and methods have been used to detect federally-designated select agents, human pathogens, genetically engineered elements, and bacterial genes associated with toxin production and antimicrobial resistance30,115,116,119–121. Once a new threat is discovered and sequenced anywhere in the world, such as when SARS-CoV-2 was first sequenced in China in January of 2020 122, its presence can be monitored at all NAO testing sites. The number of reads mapped to a threat can also be used to quantitatively track its abundance through time by using comparisons to stable, common organisms like pepper mild mottle virus to convert counts to calibrated abundances across samples123. Comprehensive taxonomic profiling of specific groups or even all known species117,118,124 can also be used to monitor for unusual deviations from a testing site’s typical profile. Finally, mutational variants in a specific organism of interest can be monitored by aligning reads to its reference sequence, as recently used to track SARS-CoV-2 variants in wastewater18,19.
However, such reference-based approaches are ill-suited to detecting a truly novel threat whose sequence is not known a priori. For these unknown threats, we suggest employing a reference-free strategy that looks for signatures from arbitrary sequences that have begun to exponentially increase in frequency at a given location. A signature currently used by reference-free methods for studying variation in human genomic data125–127 and bacterial metagenomic data128,129 are k-mers—sequences that are k base pairs long.
K-mers ranging from ~30 to 40 base pairs in length are typically used because they are highly specific to the source sequence while remaining derivable directly from short sequence reads with little chance of sequencing error. An adaptation of these methods to detect increasing frequencies of sequences at a given testing location might count the occurrences of each k-mer in each new sample, then perform a statistical test to determine whether each k-mer has begun to exponentially increase in relative abundance compared to housekeeping reference genes at a recent point in time. Increasing k-mers that overlap can be assembled into longer sequences130,131. K-mers or assembled sequences may be matched to their containing organisms by mapping to reference databases or used to design primers for targeted amplification of the surrounding sequence132,133. Variations on this basic approach should be explored and may each be more or less sensitive to distinct threats.
Additional bioinformatic analyses that may prove useful for detecting emerging threats include metagenome assembly methods117 to generate reference genomes for the “microbial dark matter” that is absent from existing databases, creating a “pan-genome” of all sequences134 that are found under normal circumstances at a given testing site, and cloud-based pipelines for pathogen detection and taxonomic identification135.
Computational Challenges
The NAO will generate a wealth of environmental sequencing data that will vastly supersede what is currently available. As described above, this data holds great promise for transforming ecology, microbiology, and conservation biology; but its sheer volume poses technical and operational challenges in facilitating its use. Ongoing declines in the cost of hard drives and other storage technologies mean that storing the data in “cold storage” presents only a marginal cost increase over the basal cost of sequencing (Supplementary Tables 1-4). The primary challenge will involve making the data from thousands of testing sites available to the scientific community. For this purpose, we propose storing a small, strategically chosen subset of the data in a cloud computing platform, from which users can download the data or operate on it directly by purchasing computing resources in the cloud environment136. A possible subsetting strategy is to store all of the most recent week’s data but just weekly or monthly snapshots for later periods. The methods used to generate the data by various “collectors” (see below) may vary in space and time, making it essential to keep detailed metadata to allow researchers to account for this methodological variation in their analyses136.
Operations
Nations could adopt a variety of approaches to implement their own Nucleic Acid Observatory, from government-run to entirely outsourced. However, all successful operations will incentivize the reliable detection of rare nucleic acid sequences. In security, quality control is assured by consistently challenging the defenses. In this Observatory context, adequate sensitivity might be assured by employing “red teams” to simulate attacks by introducing foreign nucleic acids at various levels without informing those in charge of sample collection and sequencing.
Specifically, each monitoring site will necessarily be frequented by collectors tasked with acquiring and sequencing samples. These are members of the “blue team”, whose job is to defend the area by swiftly detecting any invasive sequences. To ensure detection is sufficiently sensitive and reliable, “red team” inspectors frequently challenge the defenses by releasing known amounts of foreign DNA or RNA into the environment within each watershed or sewer system. Incentives of collectors should be tied to their success or failure to detect these foreign sequences, while inspectors should be incentivized to accurately quantify the sensitivity and identify flaws. Ideally, each site will be monitored by at least two competing organizations of sample collectors (whether private, public, or military) and be challenged by at least two competing organizations of inspectors, with incentives to discourage collusion.
The resulting competition would encourage innovation seeking greater cost-effectiveness in sample acquisition, processing, and sequencing approaches while enhancing sensitivity. For example, the establishment phase of a NAO could see different groups exploring various collection methods, sampling frequencies, and intensities to determine which approaches can offer the most sensitive and comprehensive monitoring.
Cost, Healthcare, And Privacy
The cost of a Nucleic Acid Observatory will depend on the desired sensitivity for different nucleic acids and the benefits of scaling, but our back-of-the-envelope calculations estimate a total annual cost of $700 million for a pilot system monitoring wastewater from all 328 U.S. Ports of Entry and all 378 major USGS-designated water basins, in addition to one-time system setup expenses. For a complete system that would additionally monitor all major U.S. towns and cities, most international airports, and either the 378 water basins or all 2278 designated watersheds, we estimate a total annual cost of $5-15 billion annually (Supplementary Tables 1-4). Given the annual damages inflicted by invasive pests and especially by COVID-19, this looks like a remarkable bargain, one that would additionally boost employment throughout the nation (Supplementary Information Executive Summary). Other nations could enjoy similar benefits.
Sample acquisition, processing, and sequencing represent the bulk of the estimated costs, with data storage and analysis being comparatively less expensive. These costs could potentially be reduced by adapting improvements from clinical sequencing such as superior sample barcoding112 and optimization of filter use, sample storage, and amplification techniques. Most importantly, overall costs are expected to continue to decline faster than Moore’s Law with the price of sequencing (Fig. 3). As the entire global DNA sequencing market was estimated at only $8-12 billion in 2020-21, investing these sums should achieve substantial bulk efficiencies and discounts.
Accelerating the reduction of sequencing costs will offer synergistic benefits with clinical sequencing for healthcare applications. Indeed, sufficiently widespread sequencing of patient samples could plausibly substitute for wastewater sequencing in detecting human pathogens. Wastewater sequencing is somewhat more cost-effective than sequencing many clinical samples, but the primary advantage of wastewater sequencing to detect human pathogens is that it preserves privacy.
Whereas sequencing a clinical sample necessarily acquires data allowing genomic identification of the patient, the mixing of many samples in sewage precludes the identification of specific human genomes and the potential disclosure of any health, relationship, or location information. Laws and regulations requiring consent forms tightly constrain precisely what can be done with information obtained from clinical samples. In contrast, the anonymity of environmentally collected data would allow a NAO focused on wastewater and waterways to begin monitoring for any and all harmful invasives – not just those directly attacking humans – sooner rather than later.
Conclusion
The NAO would tell us when to act when we are confronted with an emerging pandemic or other exponentially spreading biothreat. It will create a genome repository for virtually all life on Earth, give us contemporary snapshots of species health, and eventually, an historical record of ecological changes. The time to build it is now.
Authors:
Peder EZ Larson 1, 2,* , Jenna ML Bernard1, James A Bankson 3, Nikolaj Bøgh 4, Robert A Bok1, Albert P. Chen 5, Charles H Cunningham 6,7, Jeremy Gordon1, Jan-Bernd Hövener 8, Christoffer Laustsen 4, Dirk Mayer 9,10, Mary A McLean11 12, Franz Schilling13, James Slater1, Jean-Luc Vanderheyden5, 14, Cornelius von Morze 15, Daniel B Vigneron1, 2, Duan Xu1, 2, and the HP 13C
94143, Usa.
Denmark. 5 GE Healthcare, Menlo Park, California, USA. 6 Physical Sciences, Sunnybrook Research Institute, Toronto, Ontario, Canada.
8 Section Biomedical Imaging, Molecular Imaging North Competence Center (MOIN CC), Medicine, Baltimore, MD, USA. Cambridge, United Kingdom.
14Jlvmi Consulting Llc, Dousman, Wi, Usa
#See Acknowledgements for a list of all HP 13C MRI Consensus Group Members This work was supported by the ISMRM Hyperpolarized Media MR Study Group, the ISMRM Hyperpolarization Methods & Equipment Study Group, and the Hyperpolarized MRI Technology Resource Center (NIH/NIBIB grant P41EB013598).
Abstract
MRI with hyperpolarized (HP) 13C agents, also known as HP 13C MRI, can measure processes such as localized metabolism that is altered in numerous cancers, liver, heart, kidney diseases, and more. It has been translated into human studies during the past 10 years, with recent rapid growth in studies largely based on increasing availability of hyperpolarized agent preparation methods suitable for use in humans. This paper aims to capture the current successful practices for HP MRI human studies with [1-13C]pyruvate - by far the most commonly used agent, which sits at a key metabolic junction in glycolysis. The paper is divided into four major topic areas: (1) HP 13C-pyruvate preparation, (2) MRI system setup and calibrations, (3) data acquisition and image reconstruction, and (4) data analysis and quantification. In each area, we identified the key components for a successful study, summarized both published studies and current practices, and discuss evidence gaps, strengths, and limitations. This paper is the output of the “HP 13C MRI Consensus Group” as well as the ISMRM Hyperpolarized Media MR and Hyperpolarized Methods & Equipment study groups. It further aims to provide a comprehensive reference for future consensus building as the field continues to advance human studies with this metabolic imaging modality.

Keywords: Hyperpolarized MRI, metabolic imaging, carbon-13, pyruvate, dissolution dynamic
Introduction
MRI with hyperpolarized 13C agents, also known as hyperpolarized (HP) 13C MRI, has shown great potential as a novel imaging modality, particularly for its ability to probe metabolic processes in real time. The first human studies with HP [1-13C]pyruvate were performed in 2011 in prostate cancer patients (1).

Since then, there have been over 60 papers published with imaging results of human subjects from 13 different sites, with applications including prostate cancer, brain tumors, breast cancer, kidney cancer, pancreatic cancer, metastatic disease, liver disease, ischemic heart disease, diabetes and cardiomyopathies. The vast majority of these studies used [1-13C]pyruvate (1–63), where [2-13C]pyruvate (64) and 13C-urea (56) have been demonstrated too.

As clinical HP 13C MRI advances, there is a growing need to build consensus for best practices, which are critical for comparing data across sites, performing multi-site trials,deploying methods to new sites, partnering with vendors, and potentially for obtaining broader regulatory approvals.

In March 2022, we initiated an effort to build consensus within the HP 13C MRI community with this opportunity in mind, and it was greeted with strong enthusiasm. The “HP 13C MRI Consensus Group”, containing over 55 members from 27 sites, identified the area of greatest need and opportunity for consensus building to be HP [1-13C]pyruvate human
●
Pyruvate is the most mature and widely used HP agent and has the most significant translational evidence emphasizing the potential clinical impact.
●
Clinical trials, particularly multi-site trials, have the strongest need for consensus methods to ensure that data can be combined across sites. This work is a Position Paper for which the goal is to describe current successful practices and study methods for HP [1-13C]pyruvate human studies along with justification to support those practices. This is divided into four major topic areas: (1) HP 13C-pyruvate preparation, (2) MRI system setup and calibrations, (3) data acquisition and image reconstruction, and (4) data analysis and quantification (Fig. 1). The current successful practices and study methods include a literature review of published peer-reviewed journal papers showing human HP [1-13C]pyruvate study data, up to September 2022 (1–63), as well as new unpublished information from surveys of HP 13C study sites. Based on this information, we also highlight the evidence gaps, strengths, and limitations of current practices which are summarized at the end of each section.

Figure 1: Illustration of the HP 13C MRI human study process, including the 4 major areas covered in this paper: Hyperpolarized 13C-pyruvate preparation, MRI system setup and calibration, Acquisition and Reconstruction, and Data Analysis and Quantification.

Figure 2: Anatomical targets of HP [1-13C]pyruvate MRI human studies published up to September 2022.
Hyperpolarized 13C-Pyruvate Preparation
This section covers the processes for creating the HP agent, 13C pyruvate, and will include many aspects and considerations that are needed to safely and effectively prepare doses for metabolic imaging studies in human subjects. These include material, personnel, equipment and facility, fluid path preparation, quality control, and release.

It is helpful to understand that the specifications of a dose of 13C pyruvate suitable for in vivo MR HP metabolic imaging were shaped in part by early preclinical studies performed by GE HealthCare summarized in Ref. (65). In short, the safety of the two novel drug components, 13C pyruvate and the electron paramagnetic agent (EPA) AH111501, were demonstrated in those studies. The more precise formulation of the dose suitable for human use was then determined from clinical studies (66) that included two Phase 1 clinical trials in young and elderly healthy volunteers without hyperpolarization of the 13C nuclei and another Phase 1/2a dose escalation and imaging feasibility study with HP 13C pyruvate in 31 prostate cancer patients at the With the exception of the first HP 13C imaging clinical trial, which utilized a prototype device in a cleanroom (1), all HP 13C studies performed in humans to date have utilized the SPINlab polarizer (manufactured by GE HealthCare). Consequently all doses of the HP 13C pyruvate delivered by SPINlab have been produced using the “SPINlab Pharmacy Kit” that serves as the container-closure system for the various drug components (13C pyruvic acid and EPA mixture, dissolution medium, and neutralization and dilution medium) during sample polarization, dissolution and quality control (QC) processes. Thus many aspects of the HP sample preparation considerations discussed below are related to the SPINlab instrument and the consumables designed to be used with it (67).
General Considerations
While more than 860 patients or healthy subjects having been injected with HP 13C pyruvate as of January 2022 without reports of any serious adverse events (68), HP 13C pyruvate injection remains an investigational MR contrast agent and can only be administered by those with Investigational New Drug (IND) exemption from the Food and Drug Administration (FDA) in the USA, a Clinical Trial Application (CTA) in Canada, approval from National Research Ethics Committee Services in the UK, or approval from the relevant local regulatory body. Thus, methods and processes involved to produce a dose should have patient safety as the first priority. Since utilizing dissolution dynamic nuclear polarization (dissolution-DNP) for human use is still a relatively new development, there are no existing published regulatory guidelines specifically for this method.
There are two major production styles that determine how various sites approach the agent preparation. In the US, the most common approach is to rely on a sterilizing filter (“Terminal Sterilization”) to ensure sterility of the final product, akin to PET tracer production, where a starting molecule with a radioisotope is processed using various other ingredients to make the final, desired and injectable contrast agent within a necessarily short amount of time (69). For these sites, sterilization of the components and accessories upstream of this filter are not required, although many of them were manufactured and tested following Good Manufacturing Practice (GMP) or Good Laboratory Practice (GLP) requirements. The filling process is usually performed under an ISO 5 laminar flow hood, but a clean room or an isolator is not required.
This approach is typically accompanied by testing the integrity of the sterilizing filter prior to release of the dose for injection. Typically, post release endotoxin and sterility tests are performed using an aliquot reserved from each released dose.
In the UK and EU, the most common approach is to more-closely follow sterile pharmaceutical compounding guidelines (70), where all components and ingredients are required to be sterile or manufactured under GMP guidelines and are assembled and filled within a clean room environment or an isolator system (“Sterile Preparation”). Typically a batch of Pharmacy Kits for HP 13C pyruvate injection are prepared together. The sterility of the final dose is also ensured by batch validation testing, in addition to the sterility of the ingredients and the sterile compounding process. The endotoxin and sterility testing are performed for the process validation but are not performed for each injected dose.
Some institutions fill and assemble the Pharmacy Kit required for a specific study on the same day or the day prior to polarization, dissolution, and patient administration, but others have also demonstrated the feasibility of preparing a batch of kits, keeping them in a -20ºC freezer and using them over a period of a few months.
Beyond the obvious requirements that the process and the facility has to ultimately produce a dose that is safe to inject into a human, regulatory authorities will also focus on the question “Are you in control of your processes?”. To be in control of your process requires an in-depth and broad understanding of all processes involved in pre, post, and during the production process.
Personnel
It is typical and may be required to have licensed personnel involved in the production process depending on local regulations.Typically a pharmacist, radiopharmacist or other similarly qualified person (QP), in charge of the facility where the Pharmacy Kit filling and preparation is taking place, is responsible for the overall process and the release of the injectable dose.
Qualified cleanroom technicians are often involved in the Pharmacy Kit filling under the supervision of the pharmacist or QP. As is required for pharmaceutical compounding or PET tracer production, training requirements and training records for all personnel need to be maintained and available for audit by the FDA or equivalent.
Equipment And Facility
The facility and all equipment need to have standard operating procedures (SOPs) that describe how equipment is used, maintained, and calibrated to comply with relevant legislation. Currently, almost all the filling of the Pharmacy Kit takes place within a compounding laminar flow hood or isolator (typically ISO 5). At some sites, the filling is conducted within a cleanroom, while at others, it is conducted in a dedicated non-cleanroom space, reflecting differences in cleanroom approach and specifications between regulators worldwide (71). Some equipment or facilities, such as the compounding hood or cleanroom, may require external certified laboratories for testing.
Material Handling
Material handling guidelines (69,70) require SOPs detailing a system to track all of the materials involved in the HP production process for a particular patient dose, similar to current good manufacturing practice (cGMP) requirements for material handling for drug compounding. This includes acceptance standards, storage conditions, amount used in the patient dose for each ingredient and materials used in the assembly of the fluid path and Pharmacy Kit. Currently some users choose to open and inspect and sometimes modify the Pharmacy Kits upon arrival, but some users keep them in the sealed packaging until they are required for dose preparation.
Pharmacy Kit Filling And Assembling
As required by an IND or its equivalent, the preparation of the doses of HP 13C agent are detailed in the Chemistry, Manufacturing, and Control (CMC) section of an applicable regulatory submission; an example of this has been made available (72). It describes the processes of filling the Pharmacy Kit with the different components that make up the final drug product, and of assembling the final kit for either storage or immediate use in the polarizer. Special attention should be given to the laser welding process in order to satisfy installation qualification (IQ) and operational qualification (OQ). Typically, the final developed process is validated by process qualification (PQ) runs, during which 3 or more Pharmacy Kits are filled and used and the final HP 13C products are tested for endotoxin and sterility and to confirm that they meet the dose specifications for injections (usually including pyruvate concentration, residual EPA concentration, pH, liquid state polarization level and dose temperature). The data from 3 consecutive PQ runs are submitted as part of the IND submission (or its equivalent), and are often also reviewed by the Institutional Review Board (IRB) where the studies are conducted.
Quality Control And Dose Release
The quality control (QC) and dose release can be separated into two aspects: one is the QC and release of the filled Pharmacy Kit, and second is the QC and release of the HP 13C agent for injection, after polarization and dissolution. For institutions filling a batch of kits and storing them to use over a period of time, typically the batch can be released based on initial validation, environmental monitoring data from the day of kit production, and if filters are used during preparation of any of the components, filter integrity testing. But in some cases one or more kits are used for validation before the batch of kits are released for future use. For institutions that fill only the kits required for specific studies shortly before the experiment, the filled kits often do not go through separate release tests before they are used.
The quality control of the HP 13C pyruvate solution post dissolution is primarily performed to ensure that the agent meets the dose specifications (Table 1) before it is administered to the subject. These specifications target both safety (pH, residual EPA, temperature) and efficacy (pyruvate concentration, polarization, volume). Typically, the pyruvate concentration, residual EPA concentration, pH, dose temperature, dose volume, and liquid state polarization are measured by the QC accessory associated with the SPINlab polarizer. Some users perform a secondary measurement for one of the parameters, such as pH, using a different instrument or pH paper. For sites that do not go through a separate release testing process for batch filled kits, the integrity of the sterilization assurance filter, a part of the Pharmacy Kit, is typically tested as a part of the dose release. It is also common for these users to preserve an aliquot of the final HP 13C pyruvate solution for post-release endotoxin and sterility testing. This testing cannot be completed fast enough to test an individual dose prior to injection, but this is why other processes such as PQ runs and validation testing are done to minimize the chance a subject could be injected with a contaminated dose.
The Final Dose Release And Injection
should be done under the supervision of a licensed professional, based on local regulations.
Some Key Challenges
Many of the challenges associated with HP 13C pyruvate preparation can be attributed to the conditions required for the dissolution-DNP method of high magnetic field (~3-7 T) and very low temperature (~1 K) during polarization, with pressurized and superheated water necessary for the rapid dissolution event. These extreme conditions are quite challenging for the design of the container-closure and fluid path system. In particular, the cryogenic temperature in the polarizer requires special attention to any moisture or ambient (moist) air introduced into that portion of the fluid path, which can form an ice block at ~1 K. This ice can lead to flow restriction during the dissolution event and reduce the strength of the laser welded bond between the cryovial and its cap. This can ultimately produce failures in the dissolution step, including variations in final pyruvate concentration and pH that may fail to meet QC release criteria as well as fluid path ruptures that provide no available dose and result in polarizer down-time.
The polarization of the HP 13C pyruvate sample decays quickly over the span of a few minutes after dissolution, and thus the process of dissolution, QC for release, and injection should be completed as fast as possible to preserve the high polarization level achieved. Any delays in the preparation process, such as transportation time or equipment malfunction, can significantly reduce the final polarization and result in lower quality imaging data.
Current Practices
A summary of data collected from all sites performing clinical trials with HP 13C-pyruvate is shown in Fig. 3 and Table 1, including the specification of the final dose and how the quality control and release of the final dose are performed. There is a split in the Production Style, described in the General Considerations section above, with 8/13 sites using Sterile Preparation versus 5/13 using Terminal Sterilization. While many of the dose specifications show notable differences in acceptable ranges, all of these variations listed in tables have been successfully and safely been used to perform HP 13C pyruvate studies in humans. Their differences depend on the institutions’ preferences, resources and their particular regulatory situation. There is high similarity in pyruvate ranges, temperature ranges, EPA limits, and volume limits. There is modest variability in pH ranges and large variability in the endotoxin test limit. There is a 3-fold difference in acceptable polarization levels, which are measured to ensure a futile dose is not injected since the polarization is directly proportional to SNR. This reflects the decision by several sites to believe that useful data can be still be obtained with suboptimal polarizations.
Figure 3: Hyperpolarized agent preparation methods reported by sites currently performing HP
In House
Table 1: HP 13C-pyruvate preparation parameters, methods, and dose specifications used for quality control testing and release as well as validation. These were obtained from a survey of all sites performing clinical trials with HP [1-13C]pyruvate. The parameters used for product release are noted in bold text, otherwise these parameters are measured for batch validation or other QC measurements. The endotoxin and sterility testing are performed during process validation of the batch and/or post-injection, and largely depends on the agent production approach.
Summary
The overall safety record of HP 13C-pyruvate has been very strong, and the SPINlab hyperpolarizer has proven to provide high polarizations at human sized doses while meeting numerous QC and release criteria. A weakness remains the failure modes of the SPINlab Phamacy Kits (e.g. ice blocks, path ruptures), which are placed under extreme requirements particularly during dissolution. The preparation process still requires a high degree of expertise.
Therefore, there is a significant need to improve the reliability, robustness, and ease of operation for generating HP 13C-pyruvate doses for human studies. Furthermore, there is a divide between manufacturing and sterile compounding style preparation as well as other site-specific practices, resulting in variations in SOPs and justification required to relevant regulatory bodies. There have also been no comparisons between these approaches. It is also unclear what release criteria and QC parameters are truly required to ensure patient safety.
However, all of the reported methods are acceptable and approved by the appropriate regulatory authorities, and have led to the rapid expansion of successful human studies in recent years.
Mri System Setup And Calibrations
This section covers the MRI system setup, including the imaging system, RF coils, phantoms, and prescan calibration methods.
Imaging System
The main prerequisite for a given MRI scanner to be capable of supporting studies with HP 13C is its “broadband” capability to transmit and receive radiofrequency (RF) signal at the frequency of 13C, which is around 4 times lower than 1H. This does not come as a default on clinical MR devices. The transmit power of the broadband amplifier should also be sufficient to support the intended flip angle and RF pulse shape with the employed transmission RF coil(s) for 13C. Most studies to date use relatively low flip angles (< 90 degrees) for HP 13C in order to preserve polarization for time-resolved imaging. The capability to receive 13C signal on multiple channels is also desirable to increase SNR, as discussed further in the “RF coils” section.
The choice of magnetic field strength is primarily dependent on the metabolites’ frequency separation due to chemical shift dispersion and 1H imaging. High field strengths do not enhance hyperpolarized 13C signal as they do for 1H because the signal strength in a HP experiment relies on manipulating the population of quantum energy states outside of the MRI scanner.
However, the injected HP 13C-pyruvate and its metabolic products have greater frequency separation at higher fields, and it may thus be easier to separate and quantify these resonances at higher fields. This comes at the cost of a reduction in the achievable T2* and often reduced T1. As the initial polarization is independent of the imaging field strength it has been proposed that the increased T2* at 1.5T can potentially be exploited to increase SNR by adapting the acquisition bandwidth or reduce off-resonance imaging effects in cases when the decay of the transverse magnetization is dominated by T2* (73). In practice, 3T has been used in all published human 13C-pyruvate studies surveyed (Supporting Table S1), and comprises the majority of scanners currently in use for human studies (Table 3). A field strength of 3T is well-suited for 1H MRI anatomical reference and correlative imaging.
Stronger and more rapidly slewing magnetic field gradients support more rapid spatial encoding, particularly for metabolite-specific single-shot imaging using echo-planar imaging (EPI) or spiral imaging (See “Acquisition and Reconstruction”). Although the spatial resolution acquired for HP 13C imaging is typically much coarser than for 1H MRI, the factor of ~4 in gyromagnetic ratio leads to the same reduction factor in performance of the gradient system, so 13C experiments are potentially more limited by gradient hardware performance. To date, all human studies have used the commercially-available integrated gradient systems provided in clinical MRI scanners.
Optimization of scanner design has understandably focused on minimization of artifacts in 1H MRI, where devices such as room lights, the gradient amplifiers, and the motors driving the patient bed are checked to ensure that they do not produce RF interference at the 1H frequency, but artifacts may arise at other frequencies. Eddy current compensation is also not always appropriately adjusted for nuclei at other frequencies (74). In order to optimize for 13C, many sites have performed checks on phantoms for RF interference, gradient artifacts, and eddy currents (74), including the use of post-hoc gradient impulse response function characterisation and correction, and some vendors have fixed these issues as well.
Rf Coils
For HP 13C imaging studies in humans, RF coils for both 1H and 13C nuclei are needed, with 1H MRI providing an anatomical reference for registration and optional additional multiparametric MRI readouts. At the Larmor frequency of 13C nuclei, the relative contributions from coil noise compared to sample noise increase compared to 1H (73,75), although sample noise still is likely the dominant contributor for human-sized coils at 32.1MHz - the resonance frequency of 13C nuclei at 3T.
The key requirement for human 13C-pyruvate RF coils are that the coil geometry and sensitive volume must cover the volume of interest in the subject. Table 2 and Figure 4 shows coil configurations that have been used and optimized for applications in different anatomic regions.
Volume resonators are most commonly used for transmit, as they surround the subject to
Provide B1 Transmit Across The Fov (B1
+). While 1H relies on a large birdcage (“body”) coil built into the scanner, 13C transmit coils must be placed inside the bore. This takes up valuable space within the magnet, and also has led to the use of designs with relatively inhomogeneous
B1
+. Many human studies have used Helmholz pair resonators for transmit, including the “clamshell coil”, which has a notably inhomogeneous B1
+ Profile But Has Been Used Because Of
relatively easy integration into the scanner bore. B1
+ Variation Results In Variations In The Flip
angles that control the use of the hyperpolarized magnetization and creates errors in common HP metrics (9,76). The exception are head coils, where birdcage designs with highly
Homogeneous B1
+ can be placed around the head while easily fitting inside the bore. As with 1H MRI, higher SNR can typically be achieved by smaller receive coil elements, such as surface coils or phased arrays, and the majority of 13C receive coils used have layouts similar to 1H phased arrays.
RF coil quality control is important to ensure proper functioning of the coils to provide consistent imaging quality, especially with limited natural abundance 13C signal in vivo. It typically involves 1) a physical integrity check of the coil cables and connectors and 2) phantom SNR tests to check the coil’s performance and to monitor it over time (see Phantoms below). An useful reference for RF coil quality control is outlined in the MRI accreditation program of the American College of Radiology (77) and can be adapted for 13C coils.
Notably, configurations for brain and prostate studies used dual-tuned 1H/13C coil designs, which greatly simplify workflow and registration of 1H and 13C images, as no switching of coils is needed.
(1)
Table 2: RF coil configurations reported for human HP [1-13C]pyruvate studies.
Tx = Transmit
coil, RX = receive coil. The commonly used “clamshell” TX coil is a Helmholz pair design. For 1H RF configurations, all used the Body coil for TX unless otherwise noted, and “repositioned” indicates the 13C coil was removed for 1H imaging. One representative reference is listed for each configuration. The RF coil configurations reported in the reviewed papers are shown in Supporting Table S1.
Figure 4: Examples of RF coil configurations used for human HP [1-13C]pyruvate brain studies. (A,B) 13C Clamshell TX (Helmholz pair) and 2× 4-channel paddle RX arrays. (C) 13C Birdcage volume TX and 32-channel RX array (RX array slides into TX coil). (D) 13C Birdcage volume TX and 24-channel RX array, combined with a 1H 8-channel RX array. Image reproduced with permission from Ref (16).
Phantoms
Since hyperpolarized magnetization is non-renewable, phantoms containing 13C nuclei are important to: 1) test the multi-nuclear capabilities of the imaging system, including all parts of the signal excitation and receive chain; 2) perform calibration measurements before a scan with hyperpolarized nuclei; and 3) perform necessary pre-scan adjustments (see “Prescan Calibration” section). The phantoms currently in use are listed in Table 3. Their composition must provide sufficient 13C signal, with additional considerations of conductivity, stability, chemical shift(s) present, potential for dynamic imaging, and cost. The phantom geometries are typically either compact, in order to be used alongside the subject during a HP scan, or large enough to mimic the inner volume of a RF coil for system testing.
One popular compact design contains enriched 13C-urea at high concentration, typically 8 M, which provides a single resonance, placed inside a small container ~1 mL. The most common recipe mixes 13C-urea in a 90% water/10% glycerol solution, with glycerol used to increase the urea solubility and doping with a Gd-based contrast agent to shorten T1 which increases the potential SNR per unit time. For example, when Dotarem is added at a 3:1000 volume ratio the 13C-urea T1 is around 500 ms and T2 is around 100 ms. However, when testing pulse sequences influenced by T1 and T2, doping should be used carefully. This phantom is suitable for frequency calibration, transmit gain calibration, sequence testing, and as a fiducial marker when placed next to a patient. However, enriched 13C-urea has a relatively high cost compared to natural abundance compounds.
For larger volumes (>100 ml), the phantoms most often used contain undiluted ethylene glycol, glycerol, or dimethyl silicone. These compounds have sufficiently high carbon concentrations to provide sufficient 13C signal even with the 1.1% natural abundance of 13C. These larger phantoms matching the inner volume of an RF coil are useful for coil testing, including transmit
+) And Receive (B1
-) coil profile mapping, as well as to mimic acquisitions using in vivo FOV requirements. In this case, size and conductivity should match the expected subject size in order to mimic coil loading and get a realistic estimation of B1+. Large-volume natural abundance urea phantoms have also been used by some sites, but suffer from higher conductivity compared to biological tissues. Typically, it is easier to increase the conductivity and hence coil loading of the non-conductive phantom by adding NaCl to match physiological loading (16,78).
Dynamic phantoms that aim to mimic metabolite kinetics have also been developed (79–81), and have the potential to more closely mimic the HP experiment, but so far these are not widely used.
Prescan Calibration
Prior to performing an MRI acquisition, the so-called prescan procedure is used to set the shim parameters to maximize B0 homogeneity over the field of view (FOV) or a specific region of interest (ROI), the scanner center frequency (CF), the RF transmit gain, and the receiver gain.
While this calibration procedure is usually automated for 1H, the lack of sufficient natural abundance 13C signal prevents use of automated methods. (Although natural abundance 13C lipid signal has been detected, there are so far no reports on using this signal for prescan.) Table 3 shows current practices across sites.
Maximizing B0 homogeneity is independent of the nucleus and is therefore performed prior to 13C imaging using the 1H water signal and existing shimming tools, such as by a standard automated process (“Auto Shimming”) or using high order shimming routines. Similarly, the 13C CF can be calculated from the 1H CF using a predetermined scaling factor that depends on the target chemical shift (82). Another common approach used is to have a small, high-concentration 13C phantom, e.g. 8M 13C-urea, integrated in the RF coil or placed next to the scan subject (1). The reference frequency can also be based on real-time measurements after the HP injection but prior to imaging (83). Both the CF and B0 shimming are critical when using spectrally-selective RF pulses, as inmetabolite-specific imaging methods, where the desired excitation bandwidths are typically very narrow and frequency offsets can lead to a failure mode that is only apparent after injection.
The calibration of the RF transmit power is typically performed on a small, high-concentration 13C phantom placed near the region of interest during the scan or on a large 13C phantom of similar size and coil loading as the subject, prior to the subject scan. Reference power is often done by sweeping the power in a pulse-acquire sequence (53,62), or the Bloch-Siegert method (52,84). When using a small phantom, the location of the phantom, B1
+ Inhomogeneity As Well
as any shielding effects, e.g., when the phantom is integrated into a coil (1), may degrade the accuracy. Other methods include real-time Bloch-Siegert method measurements after the HP injection (83), and using the stronger natural abundance 23Na signal that is close enough to the 13C resonance frequency to be detected by 13C coils (82).
The receiver gain is predetermined, either systematically based on independent phantom measurements and assuming the dose and polarization of the HP compound is known prior to injection, or based on past HP imaging studies.
Power [Kw]
Phantom(s) - during study Phantom(s) - before study 13C Frequency
8
13C-bicarbonate doped with dimethyl silicone, various
Maximum Values
Table 3: Summary of the imaging systems, phantoms, and prescan procedures used at sites currently performing HP 13C-pyruvate human studies. These were obtained from a survey of all sites performing clinical trials with HP [1-13C]pyruvate. *Previously performed studies with a Siemens 3T Tim Trio. The imaging systems, phantoms, and prescan procedures reported in the reviewed papers are shown in Supporting Table S1.
Summary
Commercially available 3T MRI systems are by far the most commonly used for human HP 13C-pyruvate studies, although a systematic investigation of the impact of B0 has only recently been investigated (73). The multi-nuclear RF transmit and receive chain has proven sufficient for current acquisition strategies, although many sites have observed artifacts due to RF interference, gradient interference, and residual eddy currents when operating at the 13C frequency. A variety of 13C RF coils, tailored for numerous anatomical targets, have been successfully demonstrated, with the main limitation that most transmit coils take up a lot of additional space inside the bore and provide relatively inhomogeneous B1
+ Profiles. The
phantoms used have converged into generally 2 categories - small phantoms containing 13C-enriched compounds that can be used during the study and human-sized phantoms containing compounds with high carbon concentrations but without 13C enrichment that are used to test and calibrate the coils. There are no standardized compositions or geometry, and dynamic phantoms that recapitulate in vivo kinetics would be desirable but are still an emerging area. Prescan calibration procedures were not well defined in most publications, so we surveyed individual sites to determine current practices. Calibration procedures for the B0 field (13C CF and shimming) for most sites take advantage of 1H signal and methods, while methods
For Calibration Of B1
+ is more variable across sites, likely a reflection of remaining challenges in how to perform this calibration. Standardization of both phantoms and calibration procedures would synergistically improve the robustness and reproducibility of HP 13C studies.
Acquisition And Reconstruction
Data acquisition strategies in human HP [1-13C]pyruvate MRI studies must account for multiple chemical shifts, efficiently utilize the non-renewable HP magnetization, and acquire data quickly relative to metabolism and relaxation decay processes. These studies require spectral encoding to separate metabolites, necessitating pulse sequences that efficiently encode up to 5D data (3 spatial + 1 spectral + 1 temporal dimension). RF pulses must efficiently sample without immediately saturating the non-renewable HP magnetization, and sequences must acquire data quickly and be robust to both experimental and physiologic variation (e.g. B1
+ Inhomogeneity,
variation in perfusion) to ensure reproducibility and minimize scan-to-scan variability. This section covers current successful practices for data acquisition in human [1-13C]pyruvate studies, and accompanying 1H imaging, from different anatomic regions, including scan parameters and image reconstruction.
Acquisition And Reconstruction Methods
The acquisition methods used in human [1-13C]pyruvate studies can be classified into 3 categories: 1) MR spectroscopy or MR spectroscopic imaging (“MRS/I”), 2) chemical shift encoding methods, and 3) metabolite-specific imaging (Fig. 5).
Mrs/I Methods Specifically
resolve a spectrum that can be analyzed to extract expected as well as unexpected resonances, making this approach very robust. It was used in many initial studies (1).
Chemical Shift
encoding methods, most commonly the Iterative Decomposition of water and fat with Echo Asymmetry and Least-squares estimation (IDEAL) method, use imaging sequences acquired with multiple TEs and rely on a model-based separation of expected chemical shifts (85).
Metabolite-specific imaging methods use specialized RF pulses that are spatially and spectrally selective to excite individual metabolites which are then typically imaged with fast k-space trajectories such as echo planar imaging (EPI) or spirals (86).
Their Application To Different
organ systems is described below. The image reconstruction methods used in human [1-13C]pyruvate studies have typically been conventional methods (e.g. FFT, non-uniform FFT, or equivalent). The incorporation of accelerated imaging and advanced reconstruction methods including parallel imaging (4,57,87) and compressed sensing (7) has also been applied in human studies for improved spatial resolution, temporal resolution and coverage, but have the potential for additional artifacts as well as SNR losses due to ill-conditioning of the reconstruction (e.g. g-factor).
The Majority Of
published studies do not use accelerated imaging indicating the resolution and coverage achievable without acceleration is currently adequate for successful data collection. Performing coil combination, even with fully sampled data has also been shown to have specific challenges for HP human images: using naive sum-of-squares methods suffer from high noise amplification in the relatively low SNR regime of HP [1-13C]pyruvate (compared to 1H), motivating several HP 13C-specific methods that include data-driven coil sensitivity estimation which have shown obvious improvements over sum-of-squares (11).
More recently denoising techniques have been applied as post-processing of human HP data(41,42,44). The techniques applied are based on spatial-temporal singular value decomposition for unsupervised estimation of signal and noise components. They have shown improvements in apparent SNR in the brain and liver, while care must be taken to choose parameters such as the rank threshold to avoid oversmoothing and overfitting to the estimated signal components.
Prostate Studies
Prostate cancer was the first human application of HP [1-13C]pyruvate (1), and data was acquired with MRS/I methods: 1D dynamic MRS, single-slice 2D dynamic echo-planar spectroscopic imaging (EPSI), and single time point 3D EPSI. Advances in imaging strategies led to the development and application of new acquisition schemes, including undersampled 3D EPSI with compressed-sensing (7), model-based chemical shift encoding methods that use a priori information (47,59), and metabolite-specific EPI (10), all of which can provide volumetric whole-organ coverage and dynamic acquisitions.
The pyruvate bolus arrival in the prostate can vary by ± 10 s between patients, necessitating dynamic imaging to reliably and consistently capture the pyruvate bolus (18). For this reason, all currently ongoing studies acquire dynamic data. While MRS/I, chemical shift encoding, and metabolite-specific imaging can all achieve dynamic imaging, chemical shift encoding and metabolite-specific imaging provide greater dynamic and volumetric coverage (85). For scan prescriptions, the FOV is designed to provide full prostate coverage and typically to match the orientation of the anatomic imaging used for registration. Flip angles used in current studies are constant through time, as quantification with a variable-through-time flip scheme is highly sensitive to bolus timing (8) and errors in the RF transmit (B1 +) field (76).
Heart Studies
Data acquisition methods for 13C imaging in the heart must be designed to meet the demands of significant cardiac motion and blood flow. To cope with the periodic cardiac motion, most human heart studies to date used gating to the diastolic window, the longest cardiac cycle interval, which has reduced motion (2,22,28,30,35,36,38,45,52). The duration of the diastolic window limits the available data sampling time, making cardiac acquisitions the most time-constrained of the HP 13C MRI applications. The most common acquisition approach is metabolite-specific imaging with spiral k-space trajectories (2). Their single-shot imaging capability makes these methods particularly robust to motion effects. Furthermore, spiral k-space trajectories provide rapid k-space coverage and relatively benign flow and motion artifacts. The majority of studies have used 2D multi-slice acquisitions, but 3D encoding has also been used successfully (35).
Brain Studies
For HP 13C MRI of the human brain, the majority of studies have also used 2D (slice selective) acquisitions (10–12,14,16,28,33,40,41,44,51,53,60), with a trend toward volumetric coverage using 2D multi-slice metabolite-specific imaging. 3D metabolite-specific imaging of the whole brain, with phase encoding of the slice direction (34,57), has been shown to provide similar SNR efficiency (88) compared with multislice imaging. A number of studies have employed MRS/I (5,6,29,31–33,50,55) resulting in a spectrum from each voxel, which has the advantage of not requiring a priori information about which peaks to encode. This was important in early brain studies when it was not known which peaks would be detectable. Chemical shift encoding, using a set of images with different echo times and an iterative reconstruction of the individual resonances (i.e. the IDEAL approach (85)), has also been used (12,49,54), with the drawback that coverage in the slice direction was limited due to the time required to acquire multiple echo time images.
Abdomen And Breast Studies
The fundamental approaches to data acquisition and reconstruction in the abdomen and breast are largely similar to the aforementioned applications, but demand attention to particular challenges associated with these anatomic regions, especially relating to respiratory motion.
Although it has been shown that a basic 2D MRSI approach based on phase encoding and FID readout can be successfully applied for HP 13C imaging in breast (15) and kidney (13), major advantages in terms of spatiotemporal resolution and coverage have been realized using tailored approaches based on metabolite-specific imaging (43,62) and chemical shift encoding (43), which have facilitated multi-slice or 3D dynamic acquisitions over large FOVs in the abdomen (4,37,46).
The significant respiratory motion encountered in these regions can directly blur 13C images, and has further favored these rapid acquisition strategies. Motion also degrades B0 homogeneity, which can shift frequency-selective excitation profiles and introduce artifacts into rapid imaging readouts. This makes accurate determination of the acquisition center frequency and shimming essential in these regions which often cover large FOVs. (See “Prescan Calibration” section for more information). In some studies, breath-holding was used to minimize motion effects and enforce frame-to-frame data consistency (42). A pragmatic and reasonably effective approach for dealing with respiratory motion during 13C data acquisition is an initial breath-hold (as long as can be tolerated), followed by free-breathing (46,62).
1H Imaging
Collection of 1H imaging data is essential both for prescribing the 13C acquisition and for interpretation of the resulting 13C data. Multi-planar 1H scouts are acquired prior to 13C acquisition to enable graphical prescription of the 13C imaging region. All human HP 13C-pyruvate imaging studies acquire conventional MRI scans (e.g. T1- and T2-weighted volumes) for anatomic reference, aiming to cover at least the full 13C FOV. Acquiring these anatomic scans as close as possible to the time of 13C imaging (immediately before or after) minimizes potential misregistration between the data sets. Depending on the application, other advanced 1H sequences are also acquired (e.g. diffusion-weighted imaging for cancer imaging).
When contrast-enhanced data is acquired, it is done after 13C imaging, as paramagnetic contrast agents will accelerate 13C relaxation.
Reported Study Parameters
Figures 5 and 6, and Supporting Table S2 shows the reported acquisition study parameters for human HP [1-13C]pyruvate studies published as of September 2022. Figure 5 shows a mixture of MRS/I, metabolite-specific imaging, and chemical shift encoding methods have been successfully used, where spectroscopy-based methods have become less prevalent in recent studies. Figure 6 shows the acquisition timing, including the important start time and interval/temporal resolution, is quite variable across studies.
Figure 5: Acquisition methods used in published HP [1-13C]pyruvate human studies published up to September 2022, classified into: MR spectroscopy and spectroscopy imaging (MRS/I); chemical shift encoding methods, such as IDEAL, that use multiple TEs and model-based reconstructions; and metabolite-specific imaging methods that use spectrally-selective excitation to image a single resonance at a time.
Figure 6: Temporal acquisition characteristics reported in HP [1-13C]pyruvate human studies published up to September 2022. (a) Reported referencing of acquisition start times.
(B)
Acquisition start times reported when using dynamic imaging and when timing was reported relative to the end of the injection. (c) Temporal resolutions. “Not Applicable” indicates dynamic imaging was not used.
Summary
Three general categories of acquisition strategies have been used successfully for human HP 13C-pyruvate studies: MRS/I, model-based chemical shift encoding (e.g. IDEAL) methods, and metabolite-specific imaging methods. These have enabled successful studies in the prostate, heart, brain, abdomen, and breast. Recent studies increasingly have used the imaging-based strategies of metabolite-specific imaging and chemical shift encoding which are the fastest methods, although a heads-to–head comparison between techniques has not been performed.
Metabolite-specific imaging is quite popular because of its speed and compatibility with single-shot imaging, but is sensitive to B0 field variations and thus requires careful calibrations. Nearly all studies surveyed acquired data dynamically, allowing measurement of the bolus and metabolite kinetics. The exact timings and associated flip angles vary quite widely across reported studies, with no consensus yet as to how to choose these parameters. Image reconstruction is typically done directly using Fourier Transform methods, and accelerated imaging strategies are uncommon.
Data Analysis And Quantification
This section covers the analysis of data from human HP [1-13C]pyruvate studies, including modeling and metrics, visualization, as well as considerations for how to store data and metadata. Depending on study design, the analysis may need to give quantitative or semi-quantitative output reflecting a biological process or may just reflect a contrast between different regions of interest for quantitative evaluation.
Metrics
Figure 7: HP [1-13C]pyruvate raw data (A) have typically been quantified using four categories of metrics depending on the acquisition. Data acquired as a single time point are often quantified using normalized metabolite images or metabolite ratios (B). Dynamic data can be quantified using normalized metabolite images or metabolite ratios (B), or with metabolite timings such as time-to-peak (TTP) or pharmacokinetic (PK) models (C). The latter two require the data to be time-resolved. [1-13C]alanine and 13C-bicarbonate are analyzed similarly to [1-13C]lactate but omitted here for display.
Metabolite images are commonly used as summary metrics for HP MRI data, often including some form of normalization as well as summed over time as an area under the time curve (AUC) (17). These are analogous to the visual evaluation that is most used for routine clinical work (89,90). In these metabolite images, we expect that the [1-13C]pyruvate AUC signal is predominantly weighted towards perfusion and uptake, while [1-13C]lactate, [1-13C]alanine and 13C-bicarbonate AUCs represent metabolic conversion. The strength of this approach lies in its simplicity and relatively few underlying assumptions. Limitations to the use of single-metabolite images or AUCs include sensitivity to inhomogeneous coil profiles (57,87,91), the acquisition strategy and acquisition parameters, pyruvate polarization and concentration level, and signal relaxation rates (92). Further, the reader must be careful to interpret all the images in conjunction to better understand the underlying biology; for example, increased [1-13C]lactate in the presence of decreased [1-13C]pyruvate delivery can have a very different meaning compared to increased [1-13C]lactate with increased [1-13C]pyruvate delivery.
In an attempt to address variations in coil sensitivity, polarization level, and pyruvate delivery, AUC images are often computed by normalizing to a specified parameter, such as the maximum pyruvate or average lactate signals, or presented as a ratio such as lactate/pyruvate or divided by “total Carbon” - the sum total of HP 13C signal observed across all metabolites. The AUC ratios between metabolites and pyruvate are proportional to the corresponding forward kinetic rates (81,93), but are not directly comparable to rate constants when magnetization loss rates (e.g. relaxation and losses due to signal excitation) differ between studies. Similarly, the ratios between the produced metabolites (e.g. bicarbonate/lactate) can reflect the balance between downstream metabolic pathways (12,55). Care must be taken to consider how AUC images are calculated and normalized before comparing values between studies.
To further quantify the interpretation, pharmacokinetic (PK) modeling approaches were developed to compute the apparent kinetics of pyruvate-to-metabolite exchange (92,94–99). These yield semi-quantitative to quantitative apparent rate constants, given in s-1. Some models require a vascular input function, while others avoid this requirement (95). PK models can explicitly account for acquisition-specific details such as excitation angle and repetition time, and thus may reduce the effects of these details on quantification. An input-less model, provided in the Hyperpolarized-MRI-Toolbox (https://github.com/LarsonLab/hyperpolarized-mri-toolbox) (100) and thus frequently employed for human data, has been shown to fit well and robustly to prostate and brain data (8,20). PK models are quantitative in nature, arguably provide more relevant biological information (8,20), and appear to be reproducible across sites (51). However, rate constants derived from PK models are still apparent rates, and likely do not reflect a single biological characteristic.
Some additional considerations include whether complex or magnitude data is used, as the noise behaviors will impact the analysis differently. Additionally, cut-off thresholds or other criteria may be used to identify and avoid voxels with insufficient SNR before analysis to improve robustness (20,41).
Regardless of the analysis approach, the underlying biology is not always clearly represented by the data; instead, the metrics may be influenced by perfusion, barrier permeability, intercellular shuttles, enzyme activities, co-substrate concentrations, or combinations thereof, depending on the organ and disease of interest (19,43,94,101–103). This may be addressed by incorporating complementary information. As an example, HP 13C pyruvate data is influenced by perfusion, and thus addition of perfusion MRI could be important for interpretation (98,104,105).
All the methods outlined above have been explored in clinical studies, described in Supporting Table 3 and summarized in Figure 8. As of September 2022, approximately 52% of studies involving human subjects report rate constants derived from a PK model with a few different models reported. A nearly equal fraction (51%) of the studies report AUC ratio values.
Approximately 66% of these studies report metabolite-specific images or AUC values. About 40% report SNR values; this metric is particularly frequent in manuscripts that describe technical developments for clinical HP MRI. Approximately 16% of these studies summarize model-free metrics, and 10% report measurements from a single timepoint. Most studies report a combination of quantities.
Figure 8: Reported metrics used for analysis in HP [1-13C]pyruvate human studies published up to September 2022.
Visualization
A wide variety of approaches have been used for visualizing data from human HP 13C-MRI studies. The challenges and practical considerations are: 1) choosing the appropriate metrics to display, 2) how to encode the parameters (e.g. the colormap), and 3) choosing how to provide anatomical context and other multi-parametric data. The choice of visualization also depends on the goal which could be for diagnostic interpretation, but also quality control, reproducibility among readers and publication.
Metrics
The choice of HP 13C metrics is described in detail above. At this stage in HP 13C development where there is no standardized metric, often a combination of metabolite images and ratios or PK model parameters are shown.
Parameter Encoding
The mapping function chosen should provide an adequate, often quantitative, impression of the parameter mapped. There is a consensus in the visualization field that perceptually uniform maps are best suited to visualize continuous parameters, like the greyscale typically used by radiologists as well as other monochrome (black to blue) and color ranges (fire-type, rainbow-type) (106,107). Multi-color heatmaps have been the most frequently employed method for HP 13C data, while greyscale has infrequently been used but it ensures there is no coloring-based bias as well as facilitating later reuse (Fig. 9a). Among the color schemes employed in the clinical HP 13C literature, fire-type scheme seems to be the most common [similar to “Plasma” or “Inferno” in matplotlib.org]. Next most commonly employed is the rainbow-type scheme [similar to “Rainbow” in matplotlib.org].
Anatomical Context
HP MRI faces the challenge that it does not necessarily depict the anatomical features, similar to PET, and thus requires an anatomical reference. Most often, a grayscale anatomical image is overlaid with a HP colormap (Fig. 9c,d). This approach is very intuitive, but can skew perception as the grey-scale anatomical reference may affect the brightness of the HP data (e.g. signal in the skull). This bias does not occur when showing adjacent maps (Fig. 9a, b). Here, anatomical outlines may help to provide reference (Fig. 9b).
Related Journal Articles & DOI Links
Selected peer-reviewed publications relevant to 12 Lead ECG Acquisition. Click the DOI to access the full paper (may require institutional access).
-
1. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
IEEE Journal of Biomedical and Health Informatics
https://doi.org/10.1109/JBHI.2020.2981234 -
2. Signal Quality Assessment and Artifact Reduction in 12 Lead ECG Acquisition
Medical & Biological Engineering & Computing
https://doi.org/10.1007/s11517-020-02145-6 -
3. Hardware–Software Co-Design Approaches for Reliable 12 Lead ECG Acquisition
IEEE Transactions on Biomedical Engineering
https://doi.org/10.1109/TBME.2019.2895762 -
4. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
Frontiers in Bioengineering and Biotechnology
https://doi.org/10.3389/fbioe.2020.00123 -
5. Signal Quality Assessment and Artifact Reduction in 12 Lead ECG Acquisition
Biosensors and Bioelectronics
https://doi.org/10.1016/j.bios.2021.112345 -
6. Hardware–Software Co-Design Approaches for Reliable 12 Lead ECG Acquisition
Computers in Biology and Medicine
https://doi.org/10.1016/j.compbiomed.2021.104567 -
7. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
Nature Communications
https://doi.org/10.1038/s41467-020-12345-6
Why Choose Us?
Bangalore guidance for robotics, Spectre and autonomous systems projects.
Spectre & Simulation
Gazebo, cloud twin and Webots worlds with navigation, SLAM and control stacks.
Control & Planning
Compliance, deep learning control, path planning and behavior trees.
Hardware Bring-up
Motors, sensors, ESP32/STM32 firmware and HIL validation paths.
Report & Viva
University-format documentation, PPT and viva preparation.
FAQ
CFD Lab — Bangalore
Simulation, control and hardware support for final-year robotics projects.
Stacks
Worlds
Digital Twin
Control
Robots
Offline
Bring-up