Proceedings of Machine Learning Research LEAVE UNSET:1–20, 2022 Conference on Health, Inference, and Learning (CHIL) 2022
Seyun Kim†
The Cooper Union for the Advancement of Science and Art, USA
Donghwa Yang
National Health Insurance Service Ilsan Hospital, Republic of Korea
Be Fairly Compared Against Each Other As They
were tested in distinct experimental settings.
To Evaluate More Practical Aspects Of Seizure De-
tection models.
∗These Authors Contributed Equally
† This work was done while the authors were in AITRICS
The Data Used For Our Work Can Be Found From The
pus (TUSZ) dataset V1.5.2 (https://isip.piconepress. com/projects/tuh eeg/html/downloads.shtml).
Code Is Available At Https://Github.Com/Aitrics/
EEG real time seizure detection.
2. Introduction
Epilepsy is a neurologic disorder characterized by epileptic seizures (Fisher et al., 2014) and the precise frequency and type of seizures of the patient should be identified in order to diagnose epilepsy. This af- fects the decisions of pharmacological treatment, di- etary therapy, and surgical treatment (Scheffer et al., 2017). In this process, electroencephalogram (EEG) is an essential diagnostic tool for seizure detection.
Inpatient video-EEG recording is a routine diagnos- tic method for capturing seizure events for deciding proper future treatment. However, many of the event onsets are prone to be missed on-site as clinicians can- not always be present by the patient, and they can-
Not Rewind The Whole 24-Hour Video To Find Out The
© 2022 K. Lee, H. Jeong, S. Kim, D. Yang, H.-C. Kang & E. Choi.
Real-Time Seizure Detection Using Eeg
actual onset (Nordli Jr, 2006). Family members of a patient can press a button to denote the onset of the seizure event, but non-experts (i.e. family member) can make false positive or false negative decision.
In Order To Accurately Detect Seizures For Prompt
intervention, we need an on-site seizure detector that can be used while EEG is being recorded. This task can, in theory, be done by a well-trained neurologist where they routinely scan the recorded EEG signals to find out the characteristic signal for the potential
Diagnoses. This Manual Process, However, Can Take
up to several hours, making it labor-intensive as well as untimely. To improve the timeliness of the seizure detection and reduce the burden of clinicians, we need a machine that accurately detects the seizure signal in real-time to help physicians diagnose and prescribe.
Due To The Need Of An Accurate Seizure Detector,
several hospital-based research organizations released public benchmark datasets (Obeid and Picone, 2016; Shah et al., 2018; Shoeb, 2009; Goldberger et al., 2000; Andrzejak et al., 2001) for the seizure detec- tion task. There have been several attempts to de- tect seizure and abnormalities with these public EEG
Vand Et Al., 2020; Golmohammadi Et Al., 2017; Ak-
barian and Erfanian, 2020; Zabihi et al., 2015). More recent works have focused on multi-class seizure de-
Tection (Sriraam Et Al., 2019; Daoud And Bayoumi,
2019; Ahmedt-Aristizabal et al., 2020; Priyasad et al., 2021; Jia et al., 2022), and real-time seizure detec- tion (Shawki et al., 2020; Bomela et al., 2020; Thya-
Gachandran Et Al., 2020; Fan And Chou, 2018). Al-
though previous studies have explored multiple model architectures for seizure detection, we cannot fairly compare each of the model as they used distinct ex- perimental settings and evaluation metrics. Also, not all the studies adopted the real-time seizure detection tasks, limiting the practicality of the models.
In This Paper, For The First Time, We Present And
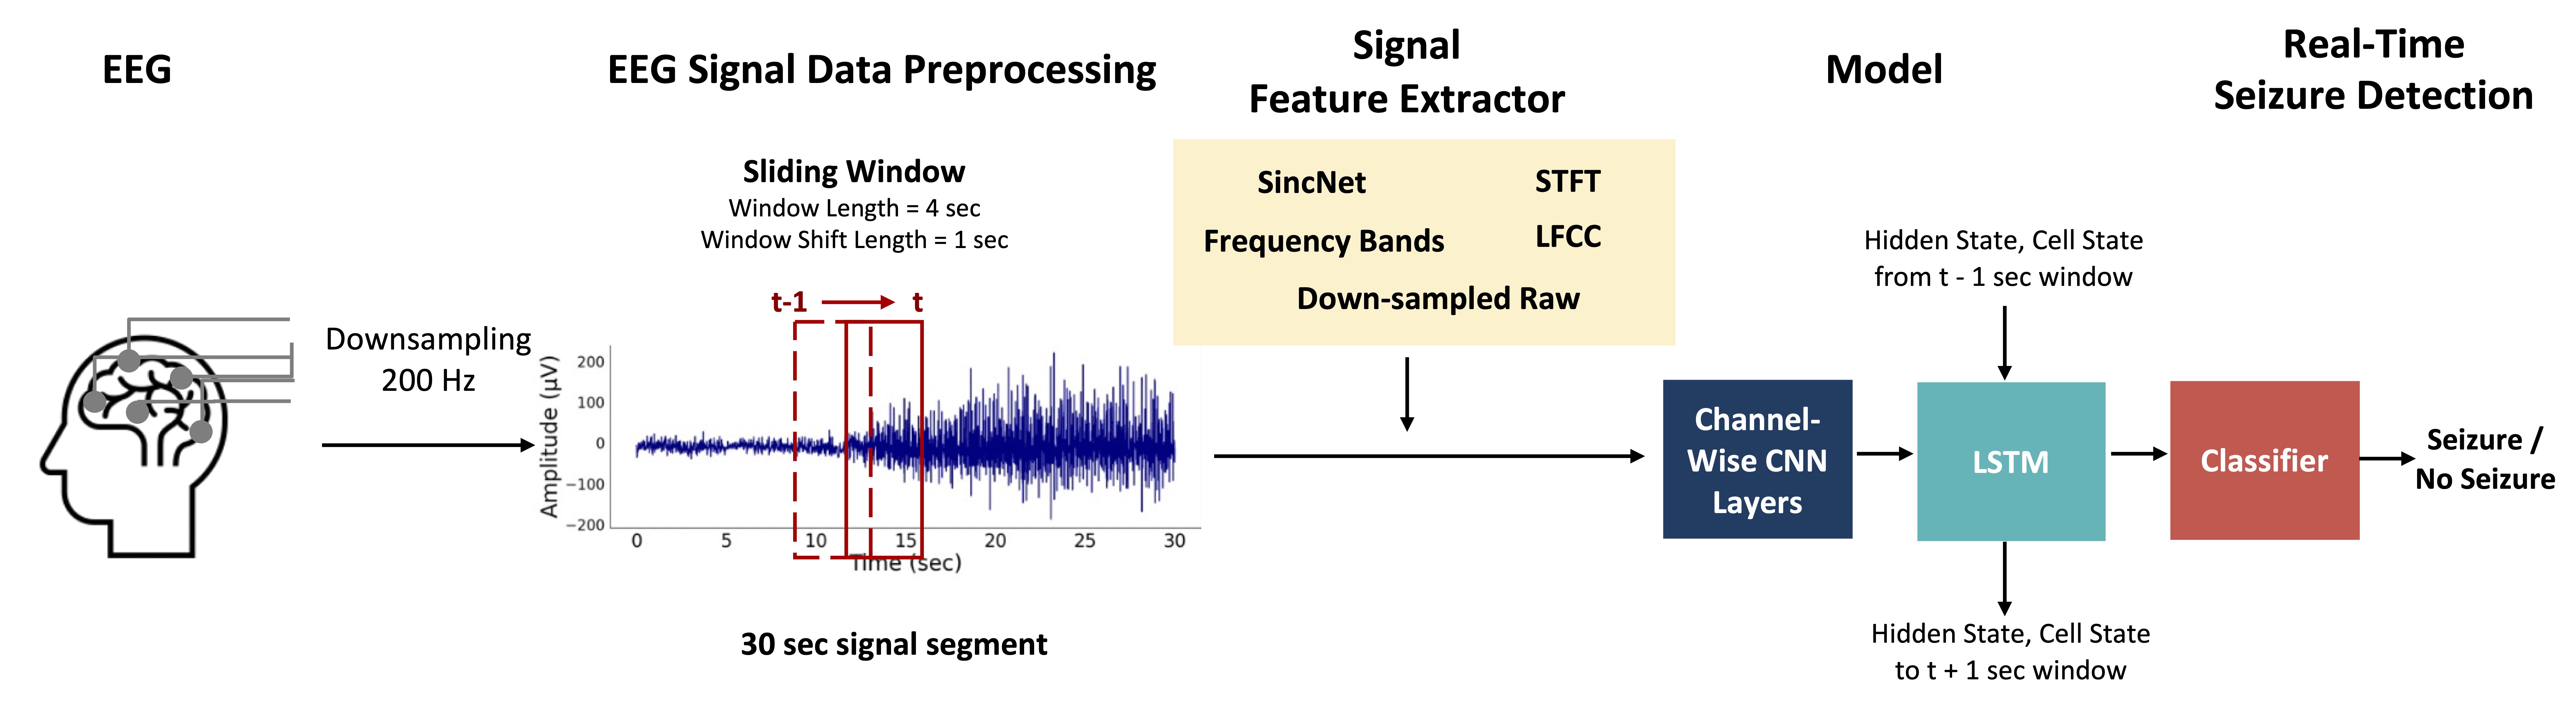
compare the performance of various state-of-the-art models and feature extraction strategies under the same experimental setting of real-time binary seizure detection (Figure 1). We performed the seizure (ictal) onset detection task, where the model receives EEG signal and detects whether the patient is currently in ictal phase or not, given that the entire process
From Feature Extraction To Detection Must Be Com-
pleted within the stride time of the sliding window in order to guarantee real-time process. We also pro-
Posed Margin-Based Evaluation Metric, Which Is An
evaluation metric providing more useful information to physicians by assessing whether a model detects seizure events within the margin from the seizure on- set and offset. Our work thus presents a comprehen-
Sive Summary Of Various Models’ Performance Under
a strictly practical and realistic setting, such that re- searchers and practitioners can directly refer to our study for deploying their own models in practice, or
Use Our Study As A Benchmark For Developing A New
seizure detection model in the future.
3.1. Signal Feature Extractor
Signal processing and frequency extraction are useful tools for extracting features from raw signal, which
Has Been Used For Preprocessing Speech Signal Or
biomedical signals (Electrocardiogram (ECG), Heart
Sound, Or Eeg Signal). One Of The Popular Feature
extractors for medical signals is Short Time Fourier Transform (STFT) (Sejdi´c et al., 2009; Springer et al., 2015; Sriraam et al., 2019), which applies a sequence of Fast Fourier transforms (FFT) to signals using a sliding window. Some of the previous works used spe- cific frequency bands out of extracted important fre- quency features (e.g., delta wave (0-4 Hz), theta wave (4-8 Hz), or alpha wave (8-12 Hz)) that are related to brain activity (Parvez and Paul, 2014; Liu et al., 2019). Other seizure detection models (Shawki et al.,
2020; Thyagachandran Et Al., 2020; Golmohammadi
et al., 2019) used linear scale filter bank on STFT output matrix, which is called Linear frequency cep-
Stral Coefficients (Lfcc). A Recent Work (Priyasad
et al., 2021) utilized SincNet (Ravanelli and Bengio, 2018) filters onto channel-wise one dimensional sigal input for seizure detection task.
Sincnet Extracts
signal features with Convolutional Neural Networks (CNN) Sinc function filters, without traditional fea- ture extracion methods. As recent deep learning ar- chitectures such as CNN provide flexible and power- ful feature extraction, recent works presented high
Performing Deep Learning Models Using Raw Signal
without feature extraction in various tasks includ- ing speech recognition (Wav2vec2.0 (Baevski et al., 2020)) and EEG seizure detection task (Roy et al., 2019b; Mohsenvand et al., 2020)). Mohsenvand et al.
(2020) downsampled the raw input signal to multiple frequencies to extract more diverse feature informa-
Tion. We Extracted Signal Features From Eeg Input
with these diverse signal feature extraction methods
Real-Time Seizure Detection Using Eeg
Figure 1: Real-Time Seizure Detection with CNN (+LSTM) models. We downsample the EEG signal and extract features (Figure 2). The models detect whether ictal/non-ictal signal appears within the 4-second sliding window input.
We present an example case with a Raw EEG signal but other signal feature extractors can also be applied to the pipeline. (Figure 2) that were frequently used for biomedical signal or speech processing.
3.2. Seizure Detection
Recent studies introduced deep neural network mod- els to binary and multi-class EEG seizure detection and classification. In this paper, we are focusing on binary seizure detection for simpler setting. A sim-
Ple Seizure Detector With Cnn Was Proposed To De-
tect seizure (Andrzejak et al., 2001; Acharya et al.,
Short Term Memory (Lstm) Hochreiter And Schmid-
huber (1997) based architectures to capture tempo-
Pared Gated Recurrent Unit (Gru) And Lstm For
real-time binary seizure detection. Another work en- coded the graph theoretic relationship between EEG leads into features to detect seizure onset time (Ak- barian and Erfanian, 2020; Zabihi et al., 2015) on
Chb-Mit Dataset (Shoeb, 2009; Goldberger Et Al.,
2000). Extending binary detection models, there has been recent attempts to classify multiple seizure types using CNN architecture (Asif et al., 2020; Sriraam
Et Al., 2019; Daoud And Bayoumi, 2019; Ahmedt-
Aristizabal et al., 2020; Priyasad et al., 2021; Jia et al., 2022), including AlexNet (Krizhevsky et al., 2012; Sriraam et al., 2019), ResNet (He et al., 2016),
Abnormal Signals In Input Eeg Signal (Roy Et Al.,
2019b; Mohsenvand et al., 2020). Rather than classi- fying the signal segment to single or multiple seizure
Types, Daoud And Bayoumi (2019) Predicted Seizure
events before it occurs. However, many of the pre- vious models cannot be applied for real-time seizure detection because they are trained to detect seizure events on the whole EEG signal.
More Recent Works Focused On Building Real-Time
seizure detectors, using various experimental settings.
Channel-Wise Lstm Was Used In Combination With
LFCC as feature extractor (Shawki et al., 2020), and
Using Lfcc (Thyagachandran Et Al., 2020) Was Ap-
(Obeid and Picone, 2016), one of the public bench- mark EEG dataset for seizure detection task. Some of the real-time seizure detectors are inappropriate for clinical use as they are slow detector. Shawki et al.
Per 1 Second Sliding Window With Cpu Processor,
which is too slow for real-time processing. Another work (Bomela et al., 2020) did not report the latency
Of A Detector. Also Some Used Small-Scale Chb-Mit
dataset that includes EEG signal of only 25 patients (Fan and Chou, 2018; Wang et al., 2018).
The Performance Of A Model On Eeg Seizure Detec-
tion can be measured by evaluating how well a model detected seizure events compared to the event label. Therefore, the evaluation metric should be valid for
Real-Time Seizure Detection Using Eeg
the seizure detection task (Ziyabari et al., 2017), dis- tinct from the accuracy measure used in time-series data or the word error rate used in the speech recog- nition task (Wang et al., 2003; Mostefa et al., 2006).
Scoring The Performance Of A Model Based On The
event is called term-based scoring, and metrics eval- uating per channel and per unit window is called the
Epoch-Based Method. Any-Overlap (Ovlp) (Wilson
et al., 2003; Gotman et al., 1997) is a term-based scoring method that measures True Positive (TP) by counting the overlapping seizure detection hypothe- sis and label. OVLP is thus more permissive, outputs high sensitivity as it only considers the event-based scoring, not considering the duration of the event.
Label And Model Prediction. These Two Methods As-
sess the model prediction within the whole signal, which is not suitable for real-time seizure detection
Task. Epoch-Based Sampling (Epoch) (Baldassano
et al., 2016) provides a more relevant metric for the real-time seizure detection, which measures the over- lap between label and prediction within a unit time window (that is a data point within an epoch), per EEG channel. In this work, we propose a new metric
Called Margin Which Evaluates The Detection Per-
formance of the seizure detection model within on- set/offset margin. Other than these four evaluation metric, we additionally measured average onset la- tency time and calculated the average onset latency time of seizure events. Summary of each metric is in Figure 4.
(V1.5.2) (Obeid And Picone, 2016) (Tuh V 1.5.2),
which contains the largest number of seizure types and patient instances. We provide better experimen- tal setting with the largest dataset as some of the
Prior Works Used Private Datasets (Daoud And Bay-
oumi, 2019) and small-scale public datasets (Akbar- ian and Erfanian, 2020; Fan and Chou, 2018; Zabihi et al., 2015) which makes it difficult to reproduce and generalize the results.
The Number Of Eeg Signal Types And Patient Num-
ber are summarized in Table 1 and Appendix Table 5. Among total 7,034 signal streaks from 642 patients, Table 1: Dataset Organization.
Ing The Whole Signal Segment Into 30 Second
signal segments.
3,671 / 964 / 456
there were total 304 patients with 3,047 signal streaks which each includes one or more seizure episode (Pa- tients group in Table 1). The dataset also included 338 patients in Normal Control group, which is the group without any seizure events. There were total 1,838 normal signals from Normal Control, and 2,149 normal signals from Patients group.
We Have 589
subjects in the training dataset and 51 subjects in the development dataset (640 subjects), which we divide into validation (25 subjects) and test set (26 subjects) according to patient instances. In order to prevent dataset shift, we randomly sample signal types within a batch so that each batch contains equal number of signal type (Table 1, Appendix Figure 5). Additional details of the dataset, including slight modification from the original TUH 1.5.2 open data, can be found in Appendix Section A.1.
Sampled With The Sampling Rate Of 200 Hz To Stan-
dardize the sampling rate of all signals (Section 4.3 6) for more detail). We sampled the EEG signals from the leads listed in Figure 6 for different types of EEG montage (Unipolar, Transverse Bipolar Montage).
We Simply Subtracted The Voltage Between Unipolar
leads to acquire Bipolar montage signal data, follow- ing Bipolar lead info from SeizureNet (Asif et al., 2020) (Appendix Figure 6, Table (a)).
4.2. Real-Time Seizure Detection
The real-time seizure detector explained in Figure 1 can be directly used for clinical setting, where the model receives signal input of 4 seconds window on- device every 1 second (i.e.
window shift length).
Thus, We Would Want A Model To Process Each Win-
dow within the shift length (1 second). We prepare
Real-Time Seizure Detection Using Eeg
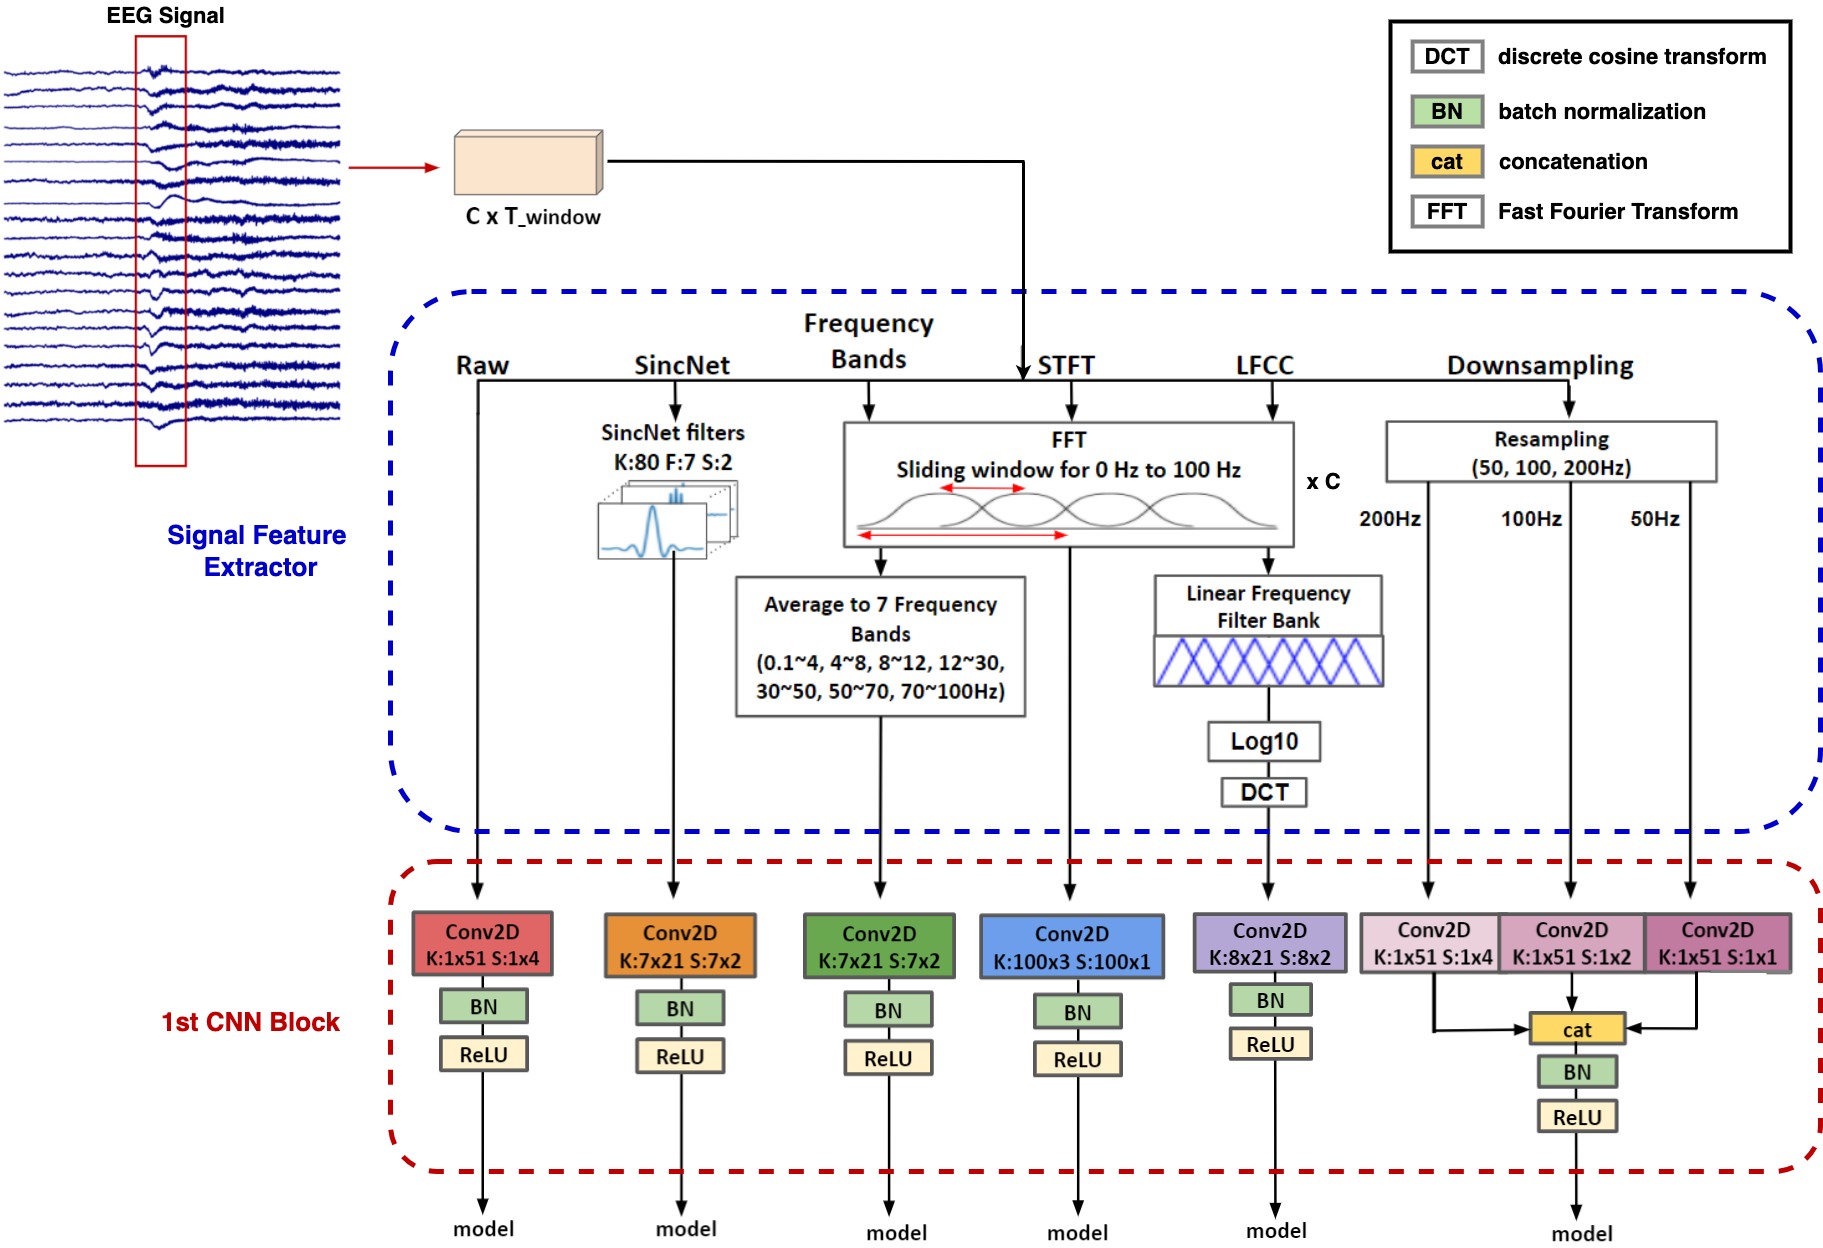
Figure 2: Signal Feature Extractors and input preprocessing. Upon downsampling EEG signal with 200Hz, the input undergoes one of the signal feature extractors and fed into the first CNN2D layer designed for each extractors. C: number of EEG signal channels, T window: length of one sliding window, K: Kernel size,
Second Window Shift Length. We Found The Optimal
window length by considering processing speed, and optimal shift length by considering the performance (Appendix Section B.2).
After Preparing Eeg Input, We Extracted Features
with signal feature extractors (Section 4.3, Table 3), and fed the extracted signal into each model (Section 4.4) to obtain the detected output. The models were
Gin As It Provides Per-Window Evaluation (Epoch)
and measures practicality of the model as real-time
Seizure Detector (Margin); We Also Explored Other
evaluation metrics on all 15 models (Appendix Table 13).
Lstm Combined Models (Figure 2). All Six Methods
affect the final performance of a model, and each has different processing speed and feature representation
(Table 3). Note That Different Types Of First Cnn2D
block was applied to the output of each feature ex- tractor, which is described in detail in each section below. For more detailed information on signal fea-
Ture Extractor (Section A.2), Cnn1D Input (Figure
7), experimental result with various models (Table 13), please see Appendix.
1) Raw: Downsampled Raw Eeg Signal (Without Fea-
ture extraction) passed to a CNN2D block with kernel shape 1 × 51 with stride 1 × 4.
Layer To Preserve More Information From The Input
signal frequency. We used 7 distinct SincNet bands with trainable frequency band range with the stride
Of 2. Cnn2D Block With Kernel Shape 7 × 21 With
stride of 7 × 2 was applied to channel-wise 2D input.
Fourier Transform (Fft) Was Applied With Sliding
window of frame length 0.125 seconds and frame shift length (hop length or overlapping size) across 50% of frame length, following the Hann window function (Oppenheim, 1999). The extracted feature represents
Information From Both Frequency And Temporal Do-
main. STFT can be also further processed with var- ious steps, such as Frequency Bands and LFCC.
4) Frequency Bands: Stft Was Applied To Ex-
tract frequency time features over 7 frequency bands: 1–4, 4–8, 8–12, 12–30, 30–50, 50–70, 70–100 Hz. Fea- tures on each band is then averaged over a signal.
We follow the parameters from Liu et al. (2019) and
Quency Ranges. We Applied The Same Cnn2D Block
from SincNet: kernel shape 7×21 with stride of 7×2.
(Lfcc): We Used 0.3 Seconds Window Length And
0.15 seconds window shift length to generate 8 ab- solute LFCC features out of the feature extractor, following setup from Shawki et al. (2020).
6) Downsampled Raw (50, 100, 200Hz) We Re-
sampled the original 200Hz raw signal data to 100Hz and 50Hz raw signals. The three differently sampled
Signals (50, 100, And 200 Hz) Are Then Fed To Cnn
block separately and concatenated for further train- ing.
Sampling Rates Of 50, 100, 200Hz Are Enough
to represent the features as it is more than twice the characteristic frequency range of seizure signals (0.5-25 Hz) (Shoeb, 2009). Furthermore, anti-aliased
And Downsampled Signal Does Not Improve The Per-
formance of our model (Table 18).
4.4. Models
We extensively searched over 15 architectures for real- time seizure onset detection on both Unipolar (Ap- pendix Table 11) and Bipolar (Table 2) montage. We also measured the model size (Appendix Table 7) and inference speed on CPU and GPU to analyze the fea- sibility of each model as the real time detector (Ap- pendix section A.4, Table 2). Details on the parame- ters and architectures of each model are summarized in Appendix Section A.3, B.1, and Figure 3.
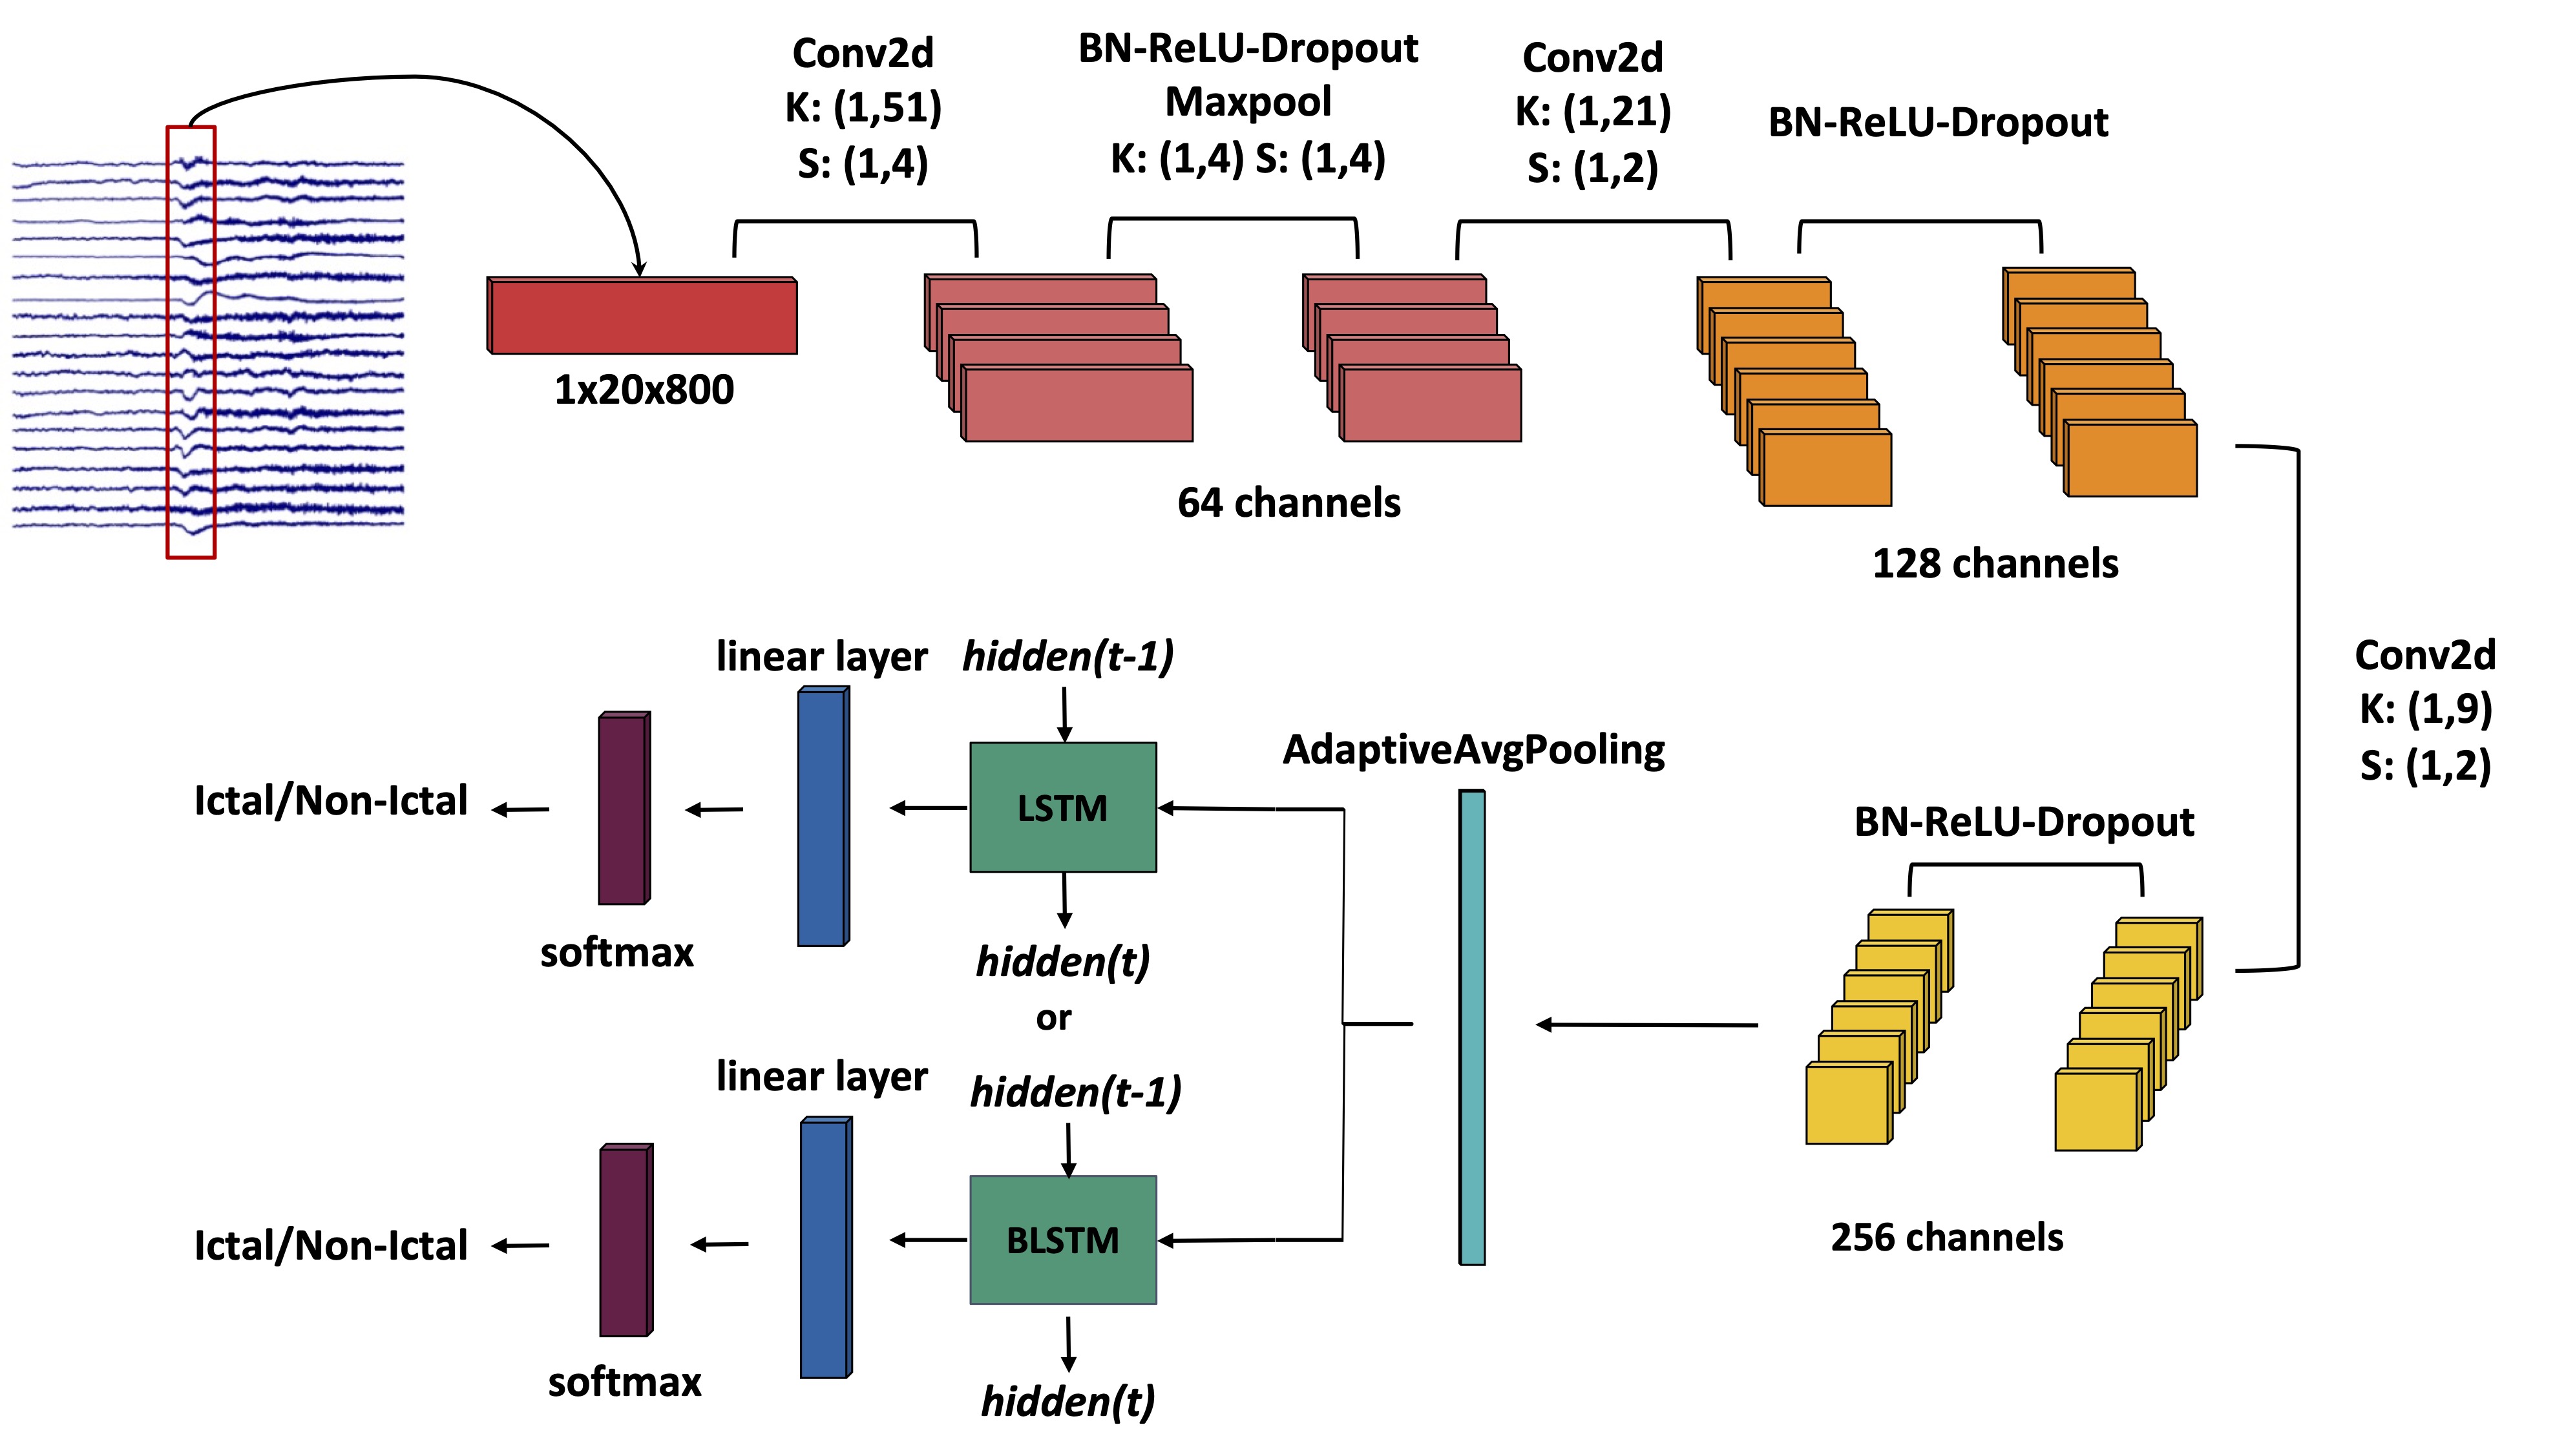
Cnn2D With Lstm Consists Of Three Parts: Cnn En-
coder for feature extraction, Recurrent Neural Net-
Work (Rnn) Module For Temporal Feature Represen-
tation, and classifier (Figure 1).
Ture Extraction, We Applied Cnn2D Layer With 1D
kernel (filters × number of channels × timestep) so that this shape filter is applied to each EEG channel separately, such that we can preserve channel-wise
Information Within Eeg Signal. This Also Brings A
model the faster feature extraction compared to the
Computation-Heavier Model With Multiple Channel-
wise 1D CNN kernels (Priyasad et al., 2021; Mohsen- vand et al., 2020). We tested the following five dif-
With Rnn Models, And Then Classifier Block (Figure
3).
Channel-Wise Signal Shape Feature And Temporal
feature for CNN2D+LSTM model.
Short-Term Memory (Blstm) In Rnn Module For
temporal feature representation.
3) Resnet-Short+Lstm: Cnn2D+Lstm Model
where CNN blocks are from ResNet model (He et al., 2016) helping a model learn both simple and rather
Complex Shape For Each Seizure Type With Flexible
gradient flow through skip connections.
Almost
same model architecture with 3) but three parallel Dilated Convolution (dilation of 1 × 1, 1 × 2, 1 × 4) was used in the first CNN2D block.
Then Concatenated And Forwarded To Cnn Blocks
from ResNet model as in 3).
Dilated Convolution Would Enable Cnn Block To
receive diverse range of signals, which is similar to
Down-Sampled Raw (Mohsenvand Et Al., 2020) But
with higher temporal resolution as the filter is shared across temporal axis. The more dilation the kernel has, the wider range of lower frequency signals the CNN model receives.
Real-Time Seizure Detection Using Eeg
Figure 3: Architecture of CNN2D + LSTM seizure detector with raw EEG input. K: Kernel size, S: Stride
To Perform On Par With Other Cnn Models But With
small size, available for the off-line portable device. In this model, MobileNetV3 CNN blocks are used for feature extraction and connected to LSTM layers.
Ture As Cnn2D + Lstm Models (Cnn, Rnn, Fol-
lowed by Classifier layer) but with CNN1D block. Unlike previous EEG seizure type classification mod- els (Priyasad et al., 2021; Mohsenvand et al., 2020)
Which Used Multiple Channel-Wise Cnn1D Modules,
our model does not have channel-wise CNN encoder.
Our Model Rather Has A Cnn1D Encoder With The Fil-
ter size following the number of channels × timestep in order to increase the speed for real-time seizure detection.
6) Cnn1D+Lstm: This Model Consists Of A Cnn
1D feature extraction block, followed by 1D adaptive average pooling module, LSTM layers, and classifier block (Figure 7).
7) Cnn1D+Blstm: Same Model Architecture
with 6) but with BLSTM instead of LSTM layer.
4.4.3. Benchmark Models
We adopted the original architecture of six different
Benchmark Models Frequently Used For Eeg Seizure
detection, abnormality detection, and seizure classi- fication (Jia et al., 2022; Ahmedt-Aristizabal et al., 2020; Roy et al., 2019a; Priyasad et al., 2021; Asif et al., 2020; Sriraam et al., 2019; Roy et al., 2019b; Thyagachandran et al., 2020).
8) Resnet18 (He Et Al., 2016): We Used Resnet18
among all ResNet variations for its small model size suitable for real time detection.
Cnn
model with squeeze-and-excite block after expansion layer, designed to perform well on mobile devices.
10) Alexnet (Krizhevsky Et Al., 2012): One Of The
early CNN architecture revolutionized CNN by using
Mentation Which Are Now Easily Found In Many Cnn
architectures.
That Connects Feature Map Of Every Layer With The
ones with following layers, and concatenate them.
12) Chrononet (Roy Et Al., 2019B): This Model
uses a CNN1D layer parallelized with various kernels, which is then connected to GRU.
Wise Eeg Signal Segment Across Timestep; Lstm
layer then combines the channel-wise contextual rep-
Real-Time Seizure Detection Using Eeg
identification (Kumar et al., 2019), voice activity de- tection, anomaly heart sound detection).
The Model Captures
similarity between signals via self-attention on the channel-wise CNN features (Appendix Figure 9). Un- like previous works using attention module (Priyasad et al., 2021; Yuan et al., 2018b,a) that calculate im-
Portance Of Each Eeg Channel, We Can Extract The
relationship between the channels from the measured channel-to-channel similiarity.
Considers The Neighboring Connection Between All
pairs of EEG leads by simply multiplying the chan-
Nel Adjacency Mask (Channel Relation Mask) To The
self attention map (Appendix Figure 9). Examples of
Adjacent Eeg Leads With C3 Are Summarized In Ap-
pendix Figure 6, where we denote neighboring leads
Used The Connection Between Leads In Bipolar Mon-
tage.
Dataset, Using Four Different Methods To Determine
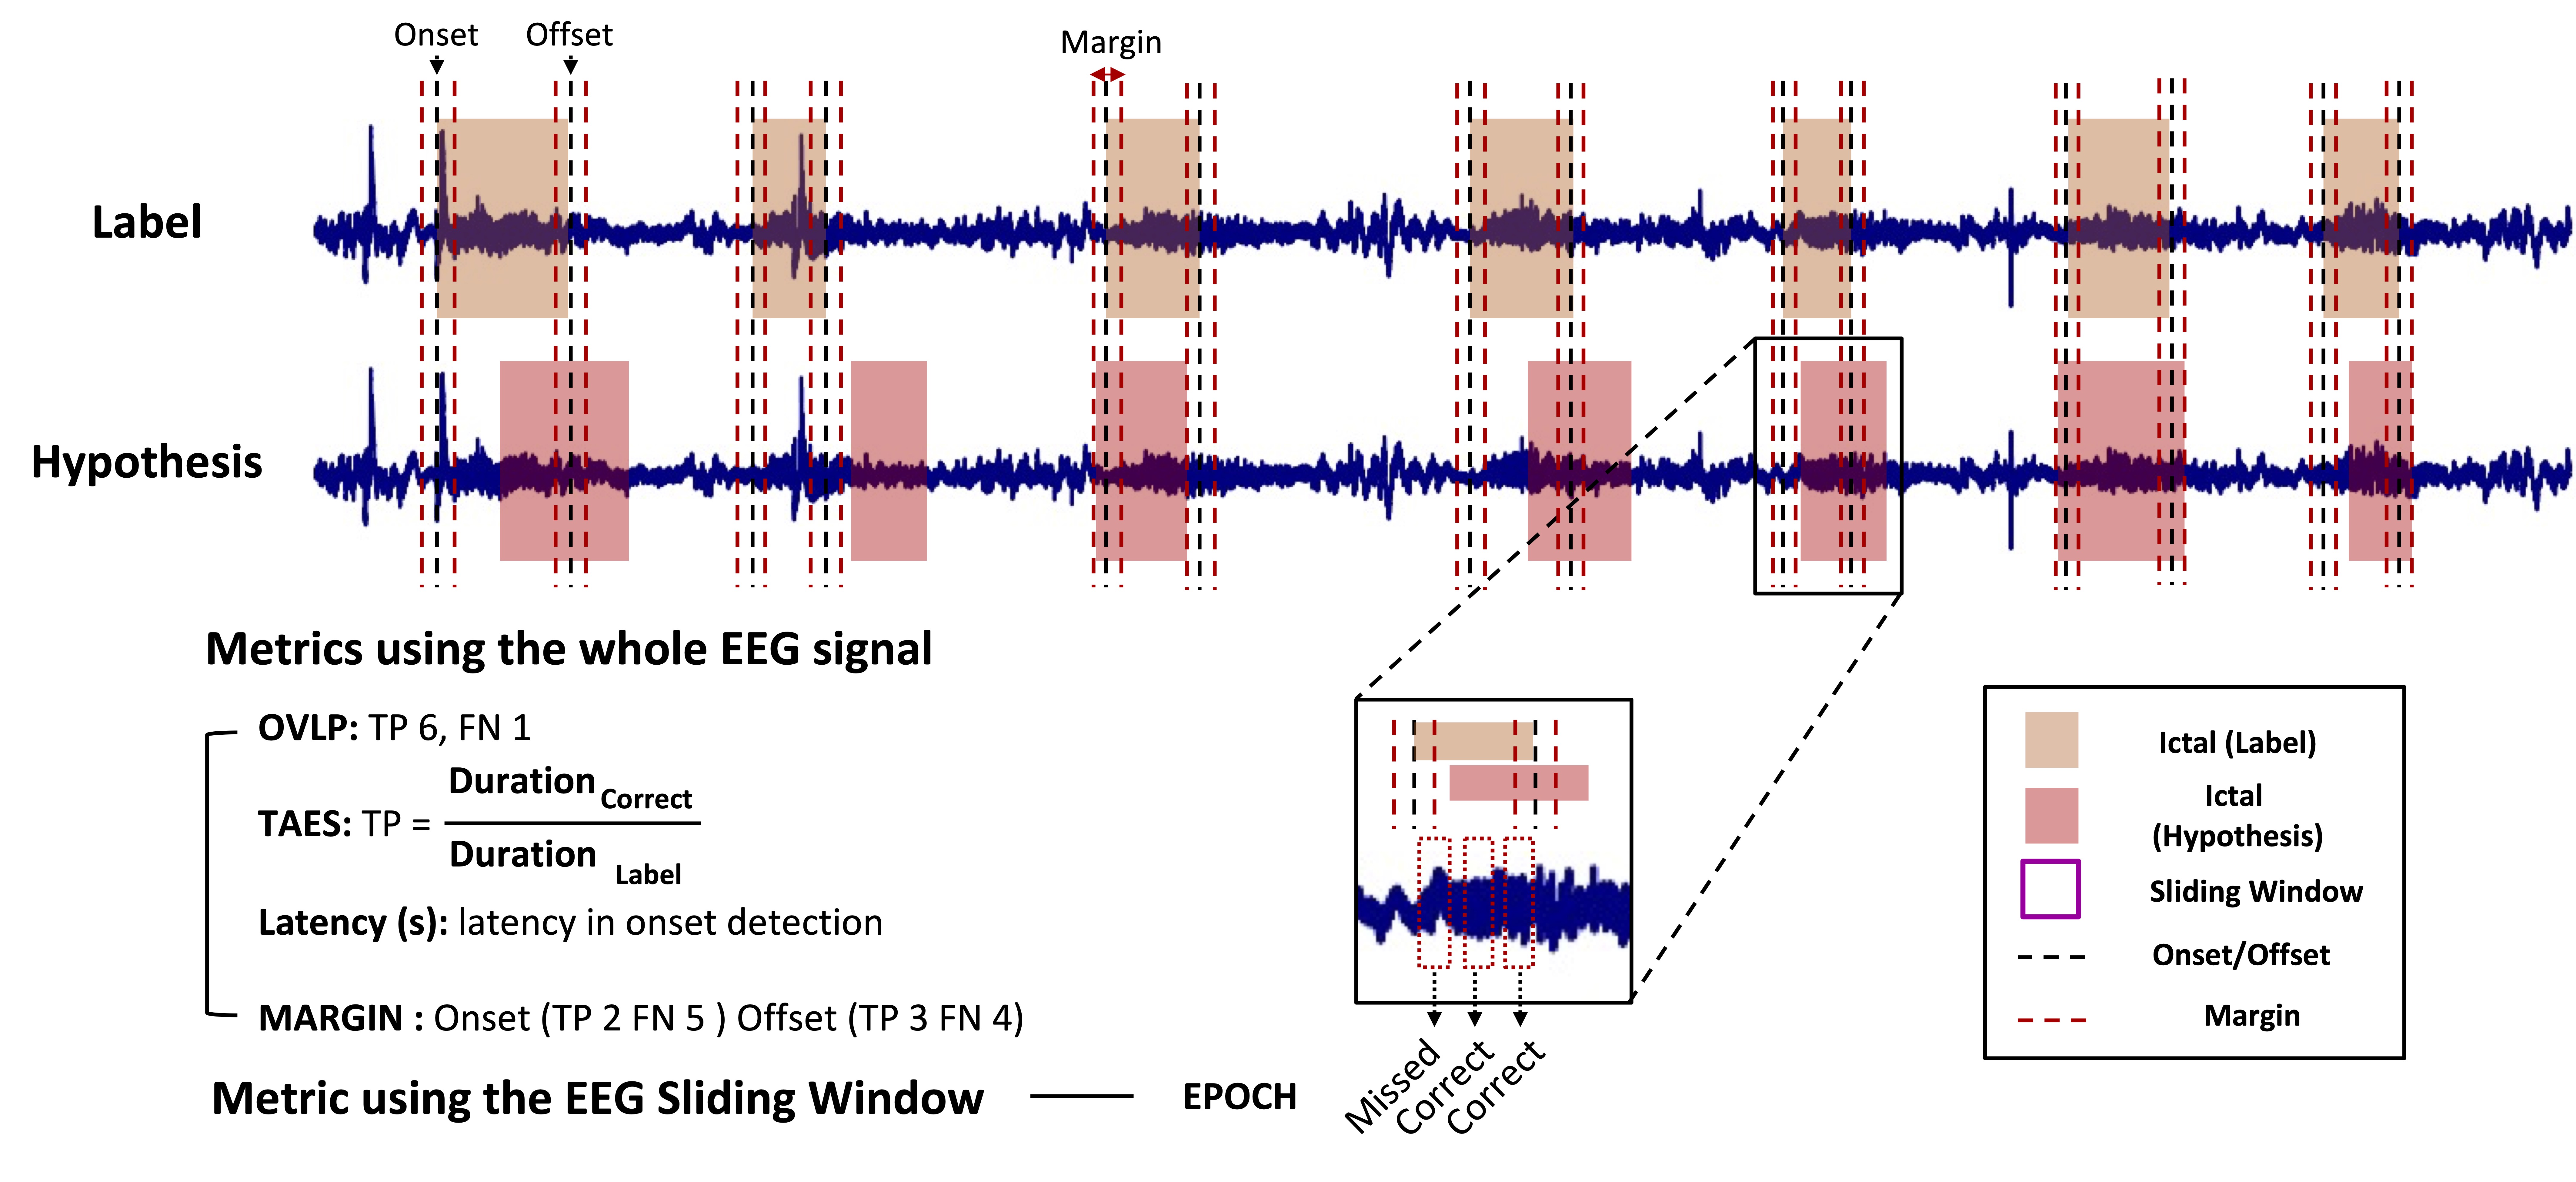
correct and incorrect classifications (Figure 4).
To
evaluate sensitivity (True Positive Rate, TPR) and
Data Of A Patient Where The Model Is Trained With
sliding window. In addition to four evaluation met- rics introduced below, we measured the onset latency, which is the average latency from the label onset to hypothesis onset.
1) Any-Overlap (Ovlp): Ovlp Provides Sensi-
tivity permissive metric which measures whether the prediction overlaps with the label.
2) Time-Aligned Event Scoring (Taes): Taes
measures the amount of overlap between seizure label and prediction, by calculating the portion of correctly predicted among total duration of seizure label.
Outputs A Summary Score Per Each Unit Window,
which evaluates the accuracy of prediction by com- paring with the ground truth label. Each epoch con-
Tains The Preprocessed Eeg Signals Within A Fixed
time window.
Whether A Model Has Detected The Seizure Within A
fixed margin (3 seconds, 5 seconds) before and after the onset / offset time of seizure. Thus, a model with
Also Compensates For The Inherent Measurement
error in scalp EEG signal, as the signal itself is an indirect measure of neural activity.
Because
of this uncertainty in the measured signal, actual seizure can often be initiated earlier than the onset
Diagnosed By Physicians. We Thus Give The Model A
safety margin to take into account situation where a model detects a seizure event before the onset.
5. Results
In this section, we report comparative experimental result on 15 model architectures (Table 2, Appendix Table 11), 6 signal feature extractors (Table 3), and 4 evaluation metrics (Table 4). We first evaluate the performance and speed of 15 models (Table 2) to find out the most favorable model for the real-time seizure detection task. We used the raw input feature as only the raw input showed the fastest processing speed on
Both Cpu And Gpu (Table 3), Among All The Other
signal feature extractors. As model evaluation only used raw signal, we explored other well-known sig- nal feature extractors so as to achieve a better per-
Formance Given The Cnn2D+Lstm Model. We Also
explored four different evaluation metrics previously used for EEG detection task, as Table 2 only reports
Among The 15 Models For Comparing Signal Feature
extractors and evaluation metrics as this model pro- vided accurate predictions as well as fast inference speed. We also provide the same set of experiments
With Resnet-Short+Lstm, Which Achieved The High-
est performance on raw EEG signals with acceptable real-time seizure detection inference speed (Table 2), for cross-reference (Table 15, 16, 17).
We Compare The Performance Of Real-Time Binary
seizure detectors on both bipolar (Table 2) and unipo- lar lead (Appendix Table 11) EEG signal datasets.
Real-Time Seizure Detection Using Eeg
Figure 4: Evaluation Methods on example raw EEG signal. OVLP, TAES, MARGIN evaluates the model on the whole raw signal. OVLP outputs whether the hypothesis overlaps with the label, and TAES outputs the duration of how much hypothesis overlaps with label. MARGIN evaluates whether the onset/offset of event hypothesis is within set margin window. EPOCH outputs evaluation on hypothesis based on each window. Then final TP is measured by counting the number of windows where the model hypothesis was correct, divided by the total number of windows within each batch. TP - True Positive; FN - False Negative.
Table 2: Result of real-time seizure detection on raw bipolar TUH EEG dataset trained with each archi- tecture, averaged over 5 runs. Please see Appendix section A.4 for CPU and GPU settings. We report TPR, TNR, and measured MARGIN when TNR is above 0.95.
0.1646 / 0.0072
length of 1 second after extensively searching for op- timal window and shift size (Appendix Section B.2).
Module Can Capture The Temporal Dependency Of The
input signal. However, the processing speed on CPU exceeds or similar to the shift length (1 second for the experiments in Table 2) indicating that larger models are relatively slow.
Compared To Cnn1D+Lstm, Cnn2D+Lstm
showed better performance as it considers indepen- dently extracted channel-wise feature information.
Chrononet (Roy Et Al., 2019B) Performed The Worst
probably because we used the raw signal and did not follow the feature extractor (LFCC) from the original paper for fair comparison. Also, the model was origi- nally designed for detecting abnormal signals (seizure or abnormal noisy signals) which is rather easier task compared to seizure detection. Feature Transformer
Also Showed Severely Poor Performance But Gained
significant performance increase after we applied the channel adjacency mask (i.e. Guided Feature Trans- former). Thus, channel relation mask helps the model factor in similarity between channels on top of at- tention scaling, so that model can capture a seizure signal spreading out to the neighborhood leads.
Dataset
showed similar trends as in the Bipolar dataset (Ap-
Decrease In Performance Compared To The Bipolar
dataset.
This Might Be Generally Because Bipo-
lar montage is effective in localizing and lateralizing seizure (Beniczky and Schomer, 2020).
Resnet18 Based Models, And Was Fast Enough To
meet the real-time constraint (i.e.
A Model Must
process each window within shift length) (Table 2).
Cnn2D+Lstm Model For Further Evaluation On
bipolar dataset with various evaluation methods (Ta- ble 4), window size (Appendix Table 8), shift size (Appendix Table 9), signal feature extractors (Ap- pendix Table 3), and seizure-type binary detection (Appendix Table 12).
Processing Methods
We compared the performance and speed of tradition- ally and frequently used signal processing methods
(Table 3). Frequency Bands And Stft Showed Bet-
ter performance compared to raw feature extraction,
Cnn2D+Lstm And Resnet-Short+Lstm Models
(Appendix Table 14, 17). We used raw data for data preparation as this provides original data without any information loss, and maintains fast processing speed suitable to be used in conjunction with EEG test in clinical setting.
5.3. Seizure Detection Evaluation Metrics
We then evaluated the binary seizure detection with
Cnn2D+Lstm And Resnet-Short+Lstm Using Var-
ious evaluation methods (Table 4, 14, 17). Sensitivity
(Tpr) Measured With Ovlp Was The Highest Among
all evaluation metric as it is more permissive in terms of sensitivity than other evaluation metrics (Ziyabari et al., 2017).
Method Margin (Seizure Boundary Detection) On
onset/offset considering margin from the onset/offset time. Our example patient signal streak shows that
Margin Provides Additional Assessment On The Re-
libility of a model whether the real-time detection output near the onset/offset of seizure is trustworthy or not (Figure 4).
And From The Result (Table 4), Ovlp Showed High
performance as it provides loose evaluation on the
And Prediction. On The Other Hand, Taes Provides
stricter result as it considers overlapping time be- tween label and hypothesis. Onset latency itself could not also be a favorable metric for real-time seizure event detection as we need to further consider the to- tal length of seizure events (Appendix Table 6) which is is not possible to be done real-time.
Epoch Presents Evaluation Result On Every Win-
dows, temporally detecting unreliable prediction of a
Model. We Used Epoch For Other Experiments As
it has been used in previous literature and provides
The Strict, Per Epoch Evaluation. Epoch Might Be
of concern if the dataset contains subjects presenting with long and short seizure events (Ziyabari et al., 2017), as it weigh long seizure events heavily.
We
thus provide additional metric more useful for seizure onset detection (MARGIN).
6. Conclusion
We provide a comprehensive analysis of the experi- mental settings on binary EEG seizure detection task for future benchmarking. While each existing models were successful in detecting seizures, the tasks can- not be compared against each other as the tasks were distinctly designed and tested.
We Set A Standard
real-time seizure detection task to fairly compare each
Real-Time Seizure Detection Using Eeg
Table 3: Real-time seizure detection on bipolar TUH EEG dataset trained with each different signal process feature extractor on CNN2D + LSTM, averaged over 5 runs. Please see Appendix section A.4 for CPU and GPU settings. Detailed results can be found in Appendix Table 14.
0.143 / 0.006
Table 4: Exploration on four evaluation methods on real-time seizure detection with CNN2D+LSTM, av- erage over 5 runs. We selected TPR, TNR and FAs/24hours that maximizes TPR + TNR, and selected MARGIN and Onset Latency when TNR is above 0.95.
10.55
models and experimental settings. We validate mod- els on real-time binary seizure detection tasks with
Raw Sampled Signal Under The Constraint That Each
window signal is processed within shift length. This work could be extended to multi-class seizure clas- sification tasks and localization of seizure onset with the help of attention modules. Our extensive research would help researchers initiate research in EEG based seizure detection tasks.
Our Work Does Not Require Institutional Review
Board approval as we did not collect patient dataset for our research.
Acknowledgments
This work was supported by Institute of Information
(Nrf-2020H1D3A2A03100945), Funded By The Ko-
rea government (MSIT).
Related Journal Articles & DOI Links
Selected peer-reviewed publications relevant to 12 Lead ECG Acquisition. Click the DOI to access the full paper (may require institutional access).
-
1. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
IEEE Journal of Biomedical and Health Informatics
https://doi.org/10.1109/JBHI.2020.2981234 -
2. Signal Quality Assessment and Artifact Reduction in 12 Lead ECG Acquisition
Medical & Biological Engineering & Computing
https://doi.org/10.1007/s11517-020-02145-6 -
3. Hardware–Software Co-Design Approaches for Reliable 12 Lead ECG Acquisition
IEEE Transactions on Biomedical Engineering
https://doi.org/10.1109/TBME.2019.2895762 -
4. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
Frontiers in Bioengineering and Biotechnology
https://doi.org/10.3389/fbioe.2020.00123 -
5. Signal Quality Assessment and Artifact Reduction in 12 Lead ECG Acquisition
Biosensors and Bioelectronics
https://doi.org/10.1016/j.bios.2021.112345 -
6. Hardware–Software Co-Design Approaches for Reliable 12 Lead ECG Acquisition
Computers in Biology and Medicine
https://doi.org/10.1016/j.compbiomed.2021.104567 -
7. Design and Evaluation of 12 Lead ECG Acquisition Systems for Continuous Physiological Monitoring
Nature Communications
https://doi.org/10.1038/s41467-020-12345-6
Why Choose Us?
Bangalore guidance for robotics, Spectre and autonomous systems projects.
Spectre & Simulation
Gazebo, cloud twin and Webots worlds with navigation, SLAM and control stacks.
Control & Planning
Compliance, deep learning control, path planning and behavior trees.
Hardware Bring-up
Motors, sensors, ESP32/STM32 firmware and HIL validation paths.
Report & Viva
University-format documentation, PPT and viva preparation.
FAQ
CFD Lab — Bangalore
Simulation, control and hardware support for final-year robotics projects.
Stacks
Worlds
Digital Twin
Control
Robots
Offline
Bring-up