Abstract — Ventilator Trigger Sensing
Creative Commons Attribution (CC BY) license ( https://creativecommons.org/licenses/by/4.0/ ). The choice of a ventilator model for a single patient is usually based on parameters such as size (portability), presence or absence of battery and ventilatory modes. However, there are many details within each ventilator model about triggering, pressurisation or autotitration algorithms that may go unnoticed, but may be important or may justify some drawbacks that may occur during their use in individual patients. This review is intended to emphasize these differences. Guidance is also provided on the operation of autotitration algorithms, in which the ventilator is able to take decisions based on a measured or estimated parameter. It is important to know how they work and their potential sources of error. Current evidence on their use is also provided.
Sensor Interfacing & Analog Front-End Conditioning
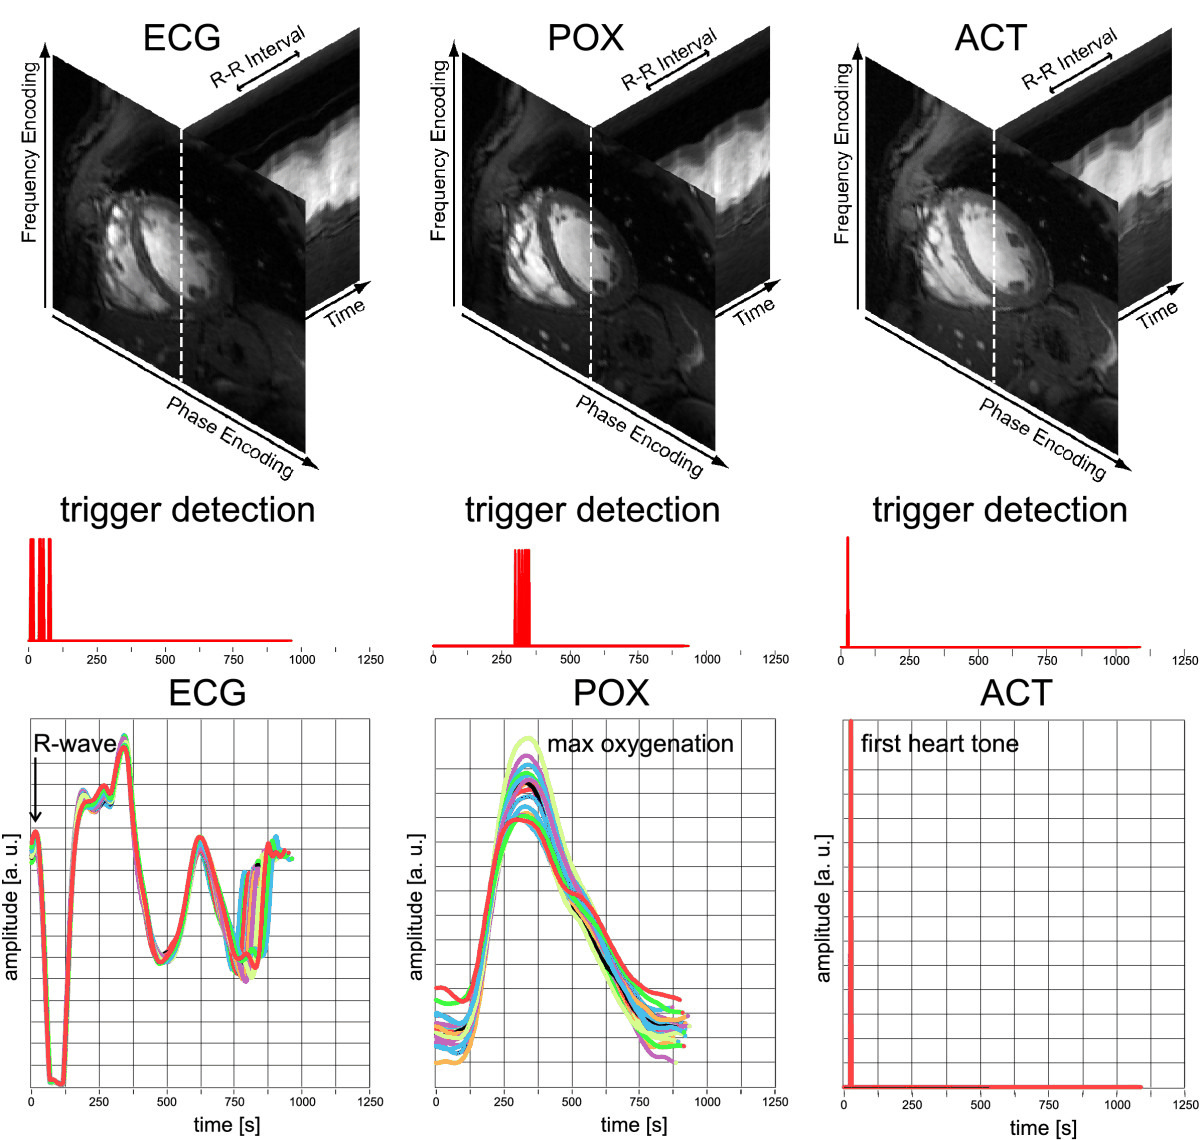
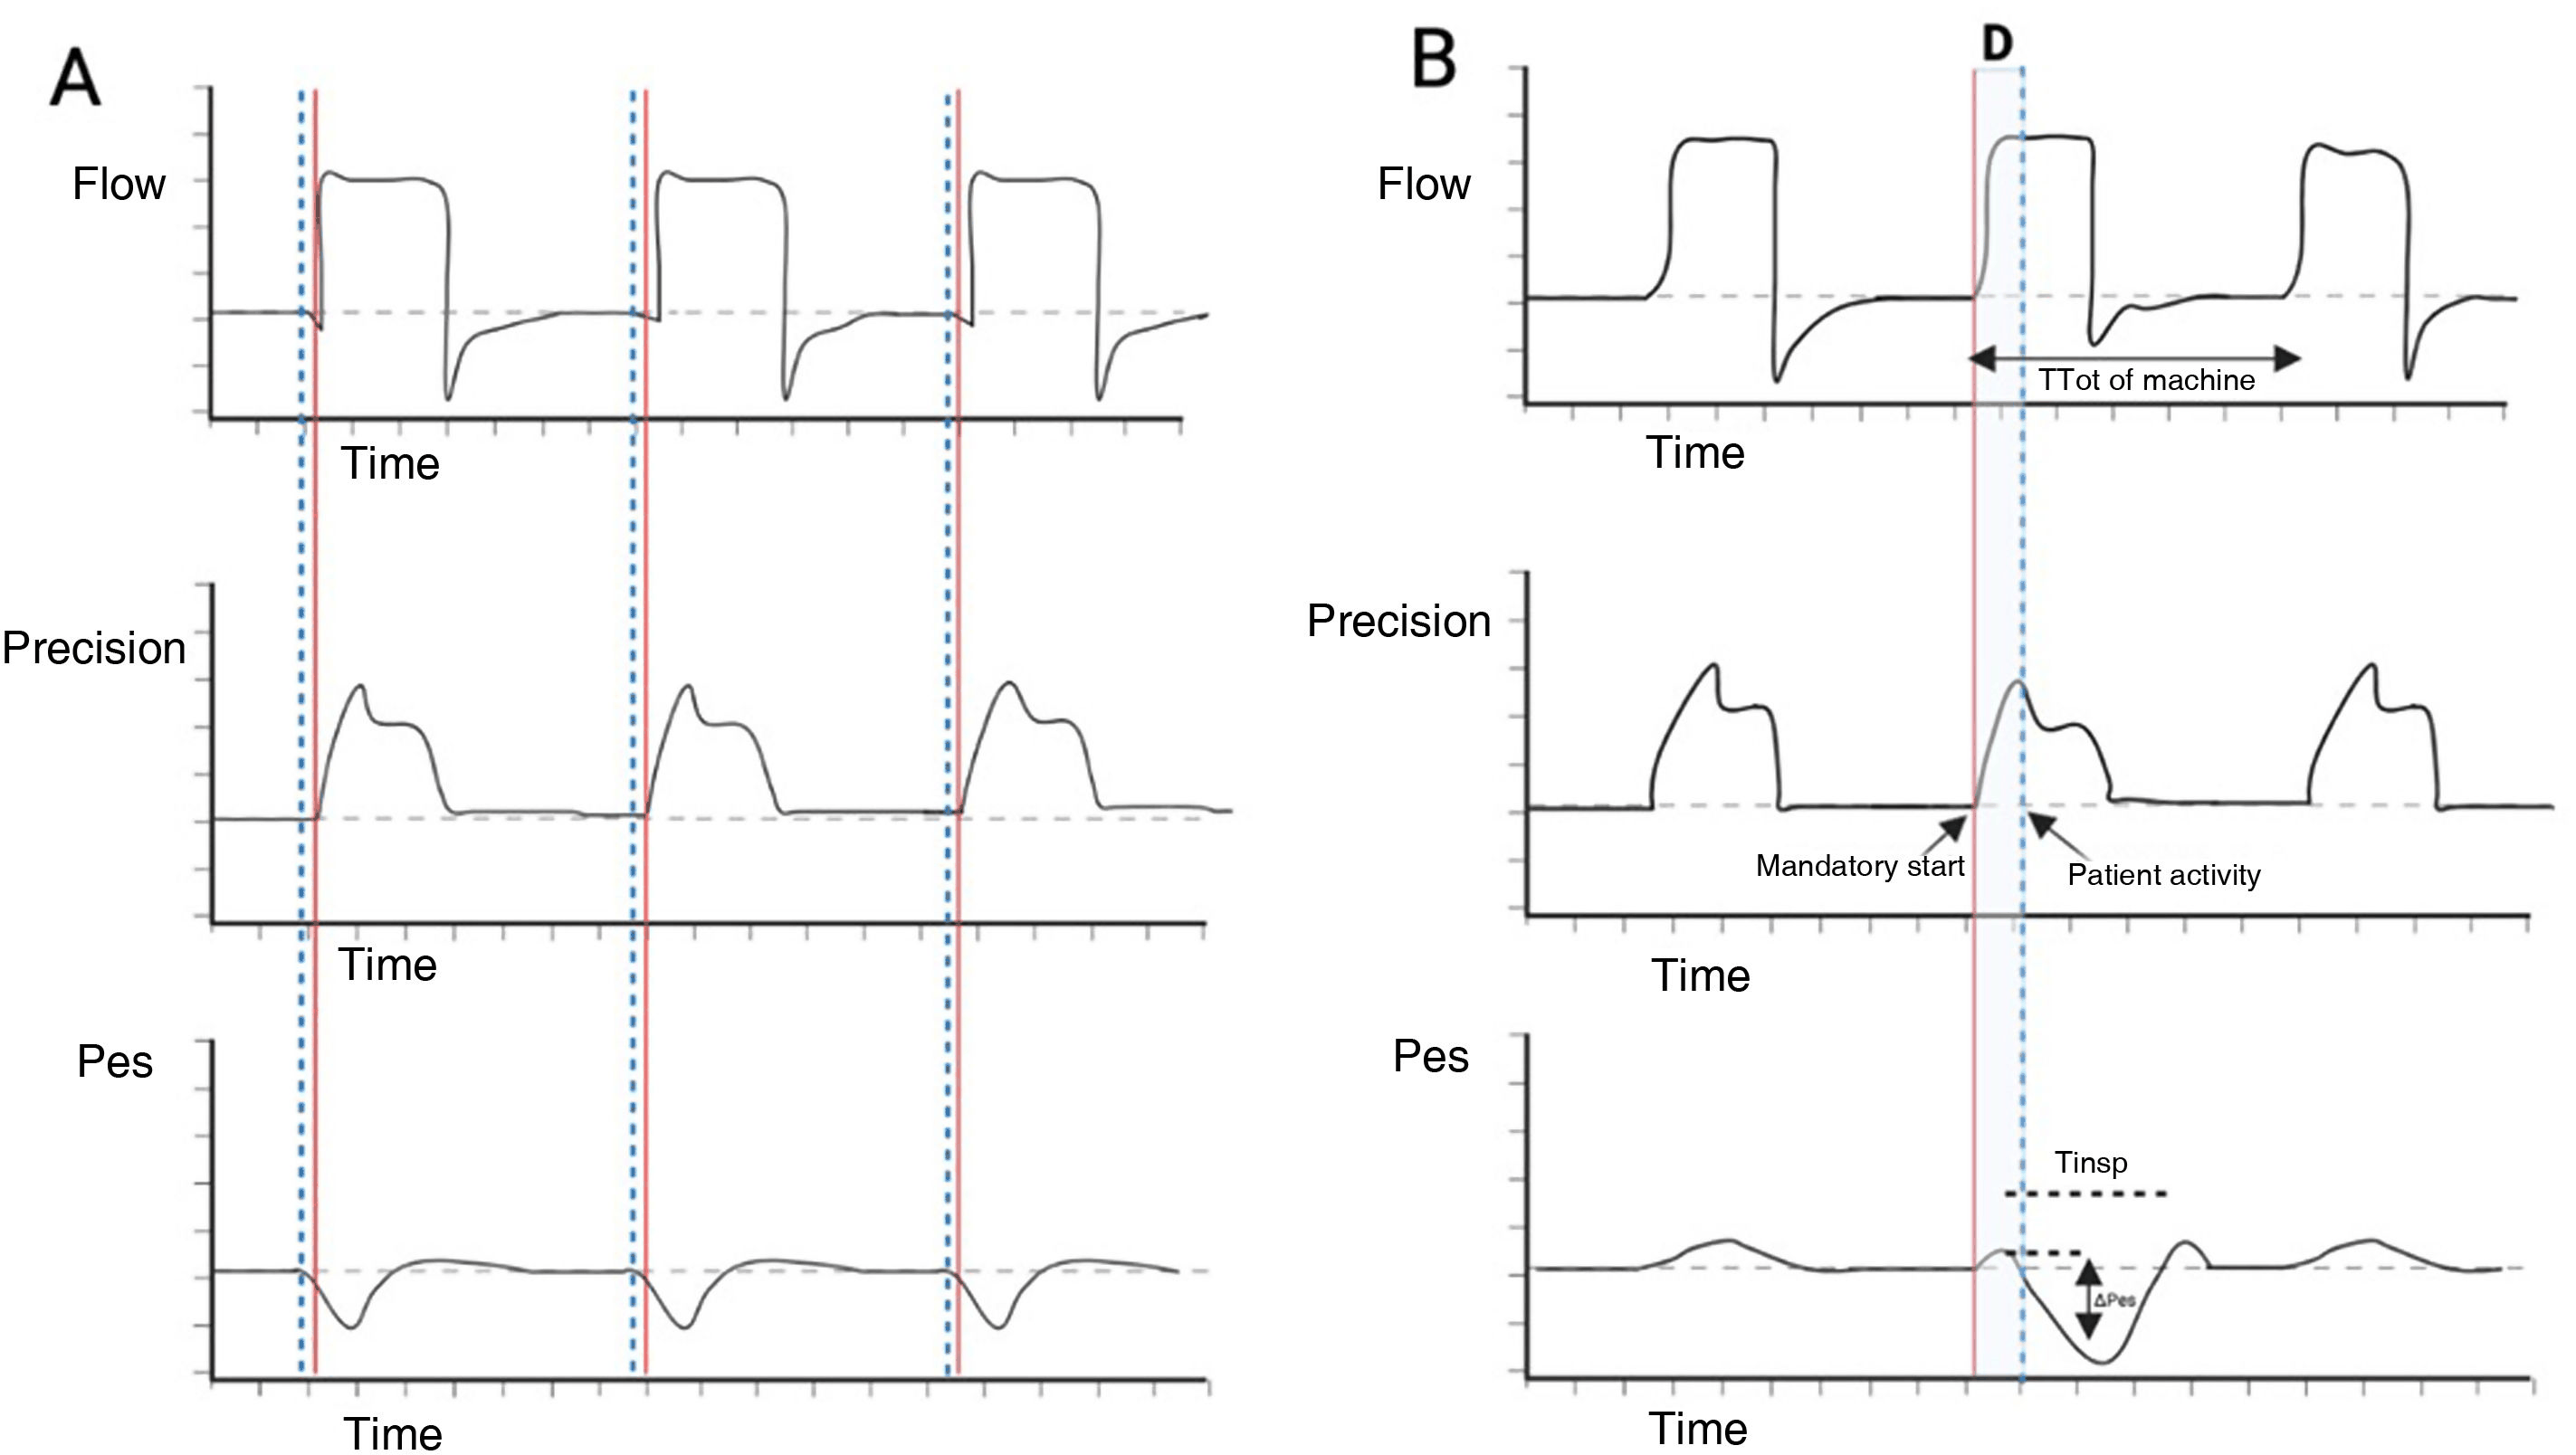
Keywords: trigger, pressurization, ventilatory modes, hybrid modes, upper airway obstruction, expiratory flow limitation Figure 2: Diagnostic Medical Waveform & Bio-Potential Clinical Trace for Ventilator Trigger Sensing The precursors of home NIV date back to the polio epidemics in the 1950s, which gave rise to the first devices, mainly ventilators, using negative extrathoracic pressure as a method of rib cage expansion (iron lung) . However, these early models presented some important problems, such as the difficulty of transport and the possibility of side effects during their use, such as upper airway obstructive events. Later, in 1984, intermittent positive pressure was introduced for patients with muscular dystrophies and, since then, it has become the treatment of choice for both acute and chronic respiratory failure secondary to various diseases [ 2 , 3 ].
Bio-Signal Waveform Analysis & Simulation Findings
Over the last two decades, the performance and improvements of NIV devices have progressively evolved in available ventilatory modes, range of set parameters and monitoring capabilities. Classically, older devices were able to work in a single ventilation mode (volumetric or barometric) and were not equipped with monitoring capabilities beyond a rudimentary counter to control compliance. All positive pressure devices can be classified according to different criteria, as each country has its own legislation, which classifies ventilators according to the situation in which they are indicated for NIV (life support, need for a battery, etc.) . From a more generic perspective, the most agreed classification classifies them as bi-level, intermediate respiratory care ventilators and ICU ventilators. Bi-level ventilators operate with a turbine system, single limb circuit and intentional leakage. They are usually transportable, have a good number of alarms and some have an internal battery. They are mainly used in chronic ventilation. ICU ventilators were primarily intended for invasive ventilation, although more modern ventilators have added “NIV modes”, which include a leak compensation system. They are usually operated with dual-limb systems and the operating mechanism can be either piston or compressor driven. They are equipped with a sophisticated alarm system and their use is restricted to critical care units. Finally, intermediate-care ventilators fall between the two categories mentioned above. They are usually equipped with an internal battery and are multifunctional, being used from the patient’s home to medical transport or emergency units [ 5 , 6 ].
Scope & Clinical Applications
- Real-time multi-parameter vital signs telemetry (ECG, Heart Rate, SpO2, Temperature, Respiration)
- Low-noise Analog Front-End (AFE) conditioning with active Driven Right Leg (DRL) 50 Hz cancellation
- Digital signal processing in MATLAB: Pan-Tompkins QRS detection, FIR/IIR notch, and Continuous Wavelet Transforms
- Finite element tissue bio-electromagnetics and orthopedic mechanical simulations in COMSOL & ANSYS
- Complete Arduino firmware .INO sketches, circuit schematics, and university dissertation reports
Bio-Potential Sensors
ECG, EEG, EMG & PPG optical probes
Low-Noise AFE
INA128 / AD8232 instrumentation amps
Arduino Firmware
Real-time ADC interrupt sampling & BLE
MATLAB Bio-DSP
Pan-Tompkins QRS & wavelet transforms
COMSOL Multiphysics
Tissue electro-thermal & SAR simulation
IEC 60601-1 Safety
Galvanic optical & magnetic isolation
Biomedical Sensors, Electronics & Simulation Suites
Engineered using clinical-grade bio-transducers, low-noise analog amplifiers, and multi-physics simulation platforms.
| Subsystem / Software | Diagnostic & Engineering Role | Instrumentation Tier |
|---|---|---|
| Arduino / ESP32 MCU | High-speed SPI/I2C sensor polling, 500 Hz timer interrupt ADC sampling, BLE telemetry streaming | Embedded Hardware |
| MATLAB R2024b | Pan-Tompkins QRS detection, 50 Hz Butterworth notch filtering, wavelet decomposition, SpO2 ratio | Signal Analytics |
| COMSOL Multiphysics | Electromagnetic tissue absorption (SAR), bio-heat thermal transfer, acoustic transducer wave propagation | Tissue Physics |
| ANSYS Mechanical | Orthopedic bone-implant contact mechanics, prosthetic socket stress distribution, dental load FEA | Biomechanics FEA |
| AD8232 / ADS1298 AFE | Medical-grade 3-lead ECG front-end with built-in instrumentation amp, DRL feedback, and high CMRR | Clinical AFE IC |
Biomedical Acquisition & Multi-Physics Simulation Workflow
Comprehensive signal flow from human bio-potential electrodes and optical sensor probes to embedded Arduino firmware, MATLAB DSP, and COMSOL tissue modeling.
(ECG/EEG/PPG/Temp)
(INA128 / DRL Loop)
500Hz ADC Sampling
& QRS Detection
Tissue FEA Models
& EHR Dashboard
Verified Medical Waveforms, Diagnostic Images & Sensor Circuits


Advantages of the Ventilator Trigger Sensing Project
Why this biomedical engineering project delivers superior academic grades and provides high technical evaluation standing.
Clinical Diagnostic Precision
Combines high-CMRR analog front-ends with precision digital filtering to extract microvolt bio-potentials with high SNR (> 35 dB).
Rigorous IEC 60601-1 Patient Safety
Incorporates dual galvanic isolation barriers (optical/magnetic) ensuring patient auxiliary leakage currents remain strictly under 10 μA.
Multi-Sensor Vital Signs Fusion
Simultaneously captures ECG, PPG, SpO2, Core Temperature, and Respiration for comprehensive physiological health monitoring.
Real-Time Arduino Embedded Firmware
Features optimized C++ interrupt-driven ADC sampling routines ready for immediate deployment on Arduino, ESP32, and STM32.
Validated Pan-Tompkins QRS Algorithm
Executes derivative, squaring, moving-window integration, and dual-threshold peak detection with > 99% R-peak accuracy.
COMSOL & ANSYS Multi-Physics Coupling
Models complex anatomical tissue structures, bio-electromagnetic Specific Absorption Rates (SAR), and prosthetic stress fields.
Driven Right Leg (DRL) Noise Suppression
Actively senses and neutralizes 50/60 Hz powerline hum and common-mode displacement currents without loading patient electrodes.
DICOM Medical Imaging Pipeline
Processes clinical MRI, CT, and Ultrasound scans using MATLAB contrast enhancement and morphological lesion boundary segmentation.
Direct Telehealth & Hospital IoT Readiness
Streams validated vital signs to mobile dashboards and electronic health records over encrypted BLE and MQTT protocols.
Complete Turnkey Project Package
Delivered with full Arduino .INO sketches, circuit schematics, MATLAB .m algorithms, university-format report, and viva defense slides.
Sample Arduino Firmware, ECG Waves & Sensor Telemetry
Representative excerpts illustrating the embedded sensor acquisition loop, live physiological waveform traces, and clinical parameter schedules.
[*] Initializing Analog Front-End (AFE) Signal Acquisition... [✓] Driven Right Leg (DRL) Active Feedback: 50 Hz Hum Attenuated by 42 dB ──────────────────────────────────────────────────────────────────────── [10:14:02.102] TRACE ECG Lead-II: ---__/\_/\_/\___ (Baseline: 0.02 mV | Normal ST Segment) [10:14:02.115] QRS R-Peak Registered (Fiducial Trigger: 1.24 mV | R-R Interval: 832 ms) [10:14:02.128] VITALS Heart Rate: 72.1 BPM | SpO2: 98.5% | PR Interval: 156 ms [10:14:02.140] TRACE ECG Lead-II: ---__/\_/\_/\___ (Baseline Stable | SNR = 36.8 dB) ──────────────────────────────────────────────────────────────────────── [✓] Diagnostic Evaluation: Sinus Rhythm Verified. Zero Ectopic Ventricular Beats.
[*] Synchronizing vital signs telemetry stream across bio-sensor channels...
| Physiological Parameter | Primary Transducer | Measured Amplitude | Sampling Bandwidth | Clinical Status |
|---|---|---|---|---|
| Cardiac Electrocardiogram (ECG) | Ag/AgCl + AD8232 AFE | 1.24 mV (R-Peak) | 0.05 Hz - 150 Hz | NORMAL SINUS |
| Pulse Oximetry (SpO₂) | MAX30102 Dual Red/IR | 98.5% Saturation | 100 Hz Optical | OPTIMAL |
| Heart Rate (HR) | R-R Peak Derivative | 72.1 BPM | 30 - 220 BPM range | EUKINETIC |
| Core Body Temperature | NTC Medical Thermistor | 36.8 °C | 0.1 Hz Thermal | AFEBRILE |
[✓] Diagnostic Evaluation: Patient physiological parameters within verified clinical tolerance band.
Frequently Asked Questions
Project Deliverables & Support
Everything needed from project inception to final viva defense — delivered with expert biomedical support.
.INO Sketches
Schematics
Algorithms
Report
Slides
Models
Datasets
Q&A
Support
Extension