Complete Technical Paper Content — Blockchain Based Access Control System For Healthcare
Overview & System Context
Blockchain Based Access Control System For Healthcare: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~8517 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background A decentralized identifier (DID) is a type of globally unique identifier that enables an entity to be identified in a manner that is verifiable, persistent (as long as the DID controller desires), and does not require the use of a centralized registry. DIDs enable a new model of decentralized digital identity that is often referred to as a self-sovereign identity (SSI). This emerging model of digital identity, based on DIDs and SSIs, puts users in full control of their identity data and addresses key limitations of centralized and federated identity providers, including security vulnerabilities, large-scale data breaches, limited privacy protections, and insufficient user control. The DIDs are an important component of decentralized web applications. A decentralized identity management system based on Decentralized Identifiers and Self-Sovereign Identity principles, usually starts from a reference architecture involving Issuers, Holders, and Verifiers, with digital wallets or agents acting on behalf of identity subjects, and a specific identity infrastructure that supports issuance, validation and revocation of credentials.
The name of the DID method (which must appear between the first and second colon, e.g., did:example:). The structure of the unique identifier that must follow the second colon. The technical specifications for how a DID resolver can apply the CRUD operations to create, read, update, and deactivate a DID document using that method. The W3C DID Working Group maintains a registry of DID methods.
Mutual authentication or two-way authentication is the simultaneous and reciprocal authentication of two parties. It is part of authentication protocols, default in some protocols (IKE, SSH) and optional in others (TLS). Mutual authentication is a desired characteristic in verification schemes that transmit sensitive data, in order to ensure data security. Mutual authentication can be accomplished with two types of credentials: usernames and passwords, and public key certificates. Mutual authentication is often employed in the Internet of Things (IoT). Writing effective security schemes in IoT systems is challenging, especially when schemes are desired to be lightweight and have low computational costs. Mutual authentication is a crucial security step that can defend against many adversarial attacks, which otherwise can have large consequences if IoT systems (such as e-Healthcare servers) are hacked. In scheme analyses done of past works, a lack of mutual authentication had been considered a weakness in data transmission schemes.
Alice sends a message encrypted with Bob's public key to Bob to show that Alice is a valid user. Bob verifies the message: Bob checks the format and timestamp. If either is incorrect or invalid, the session is aborted. The message is then decrypted with Bob's secret key, giving Alice's ID. Bob checks if the message matches a valid user. If not, the session is aborted. Bob sends Alice a message back, encrypted with Alice's public key, to show that Bob is a valid user. Alice verifies the message: Alice checks the format and timestamp. If either is incorrect or invalid, the session is aborted. The message is then decrypted with Alice's secret key, giving Bob's ID. Alice checks if the message matches a valid user. If not, the session is aborted. At this point, both parties are verified to be who they claim to be and safe for the other to communicate with. Lastly, Alice and Bob will create a shared secret key so that they can continue communicating in a secure manner. To verify that mutual authentication has occurred successfully, Burrows-Abadi-Needham logic (BAN logic) is a well regarded and widely accepted method to use, because it verifies that a message came from a trustworthy entity. BAN logic first assumes an entity is not to be trusted, and then will verify its legality.
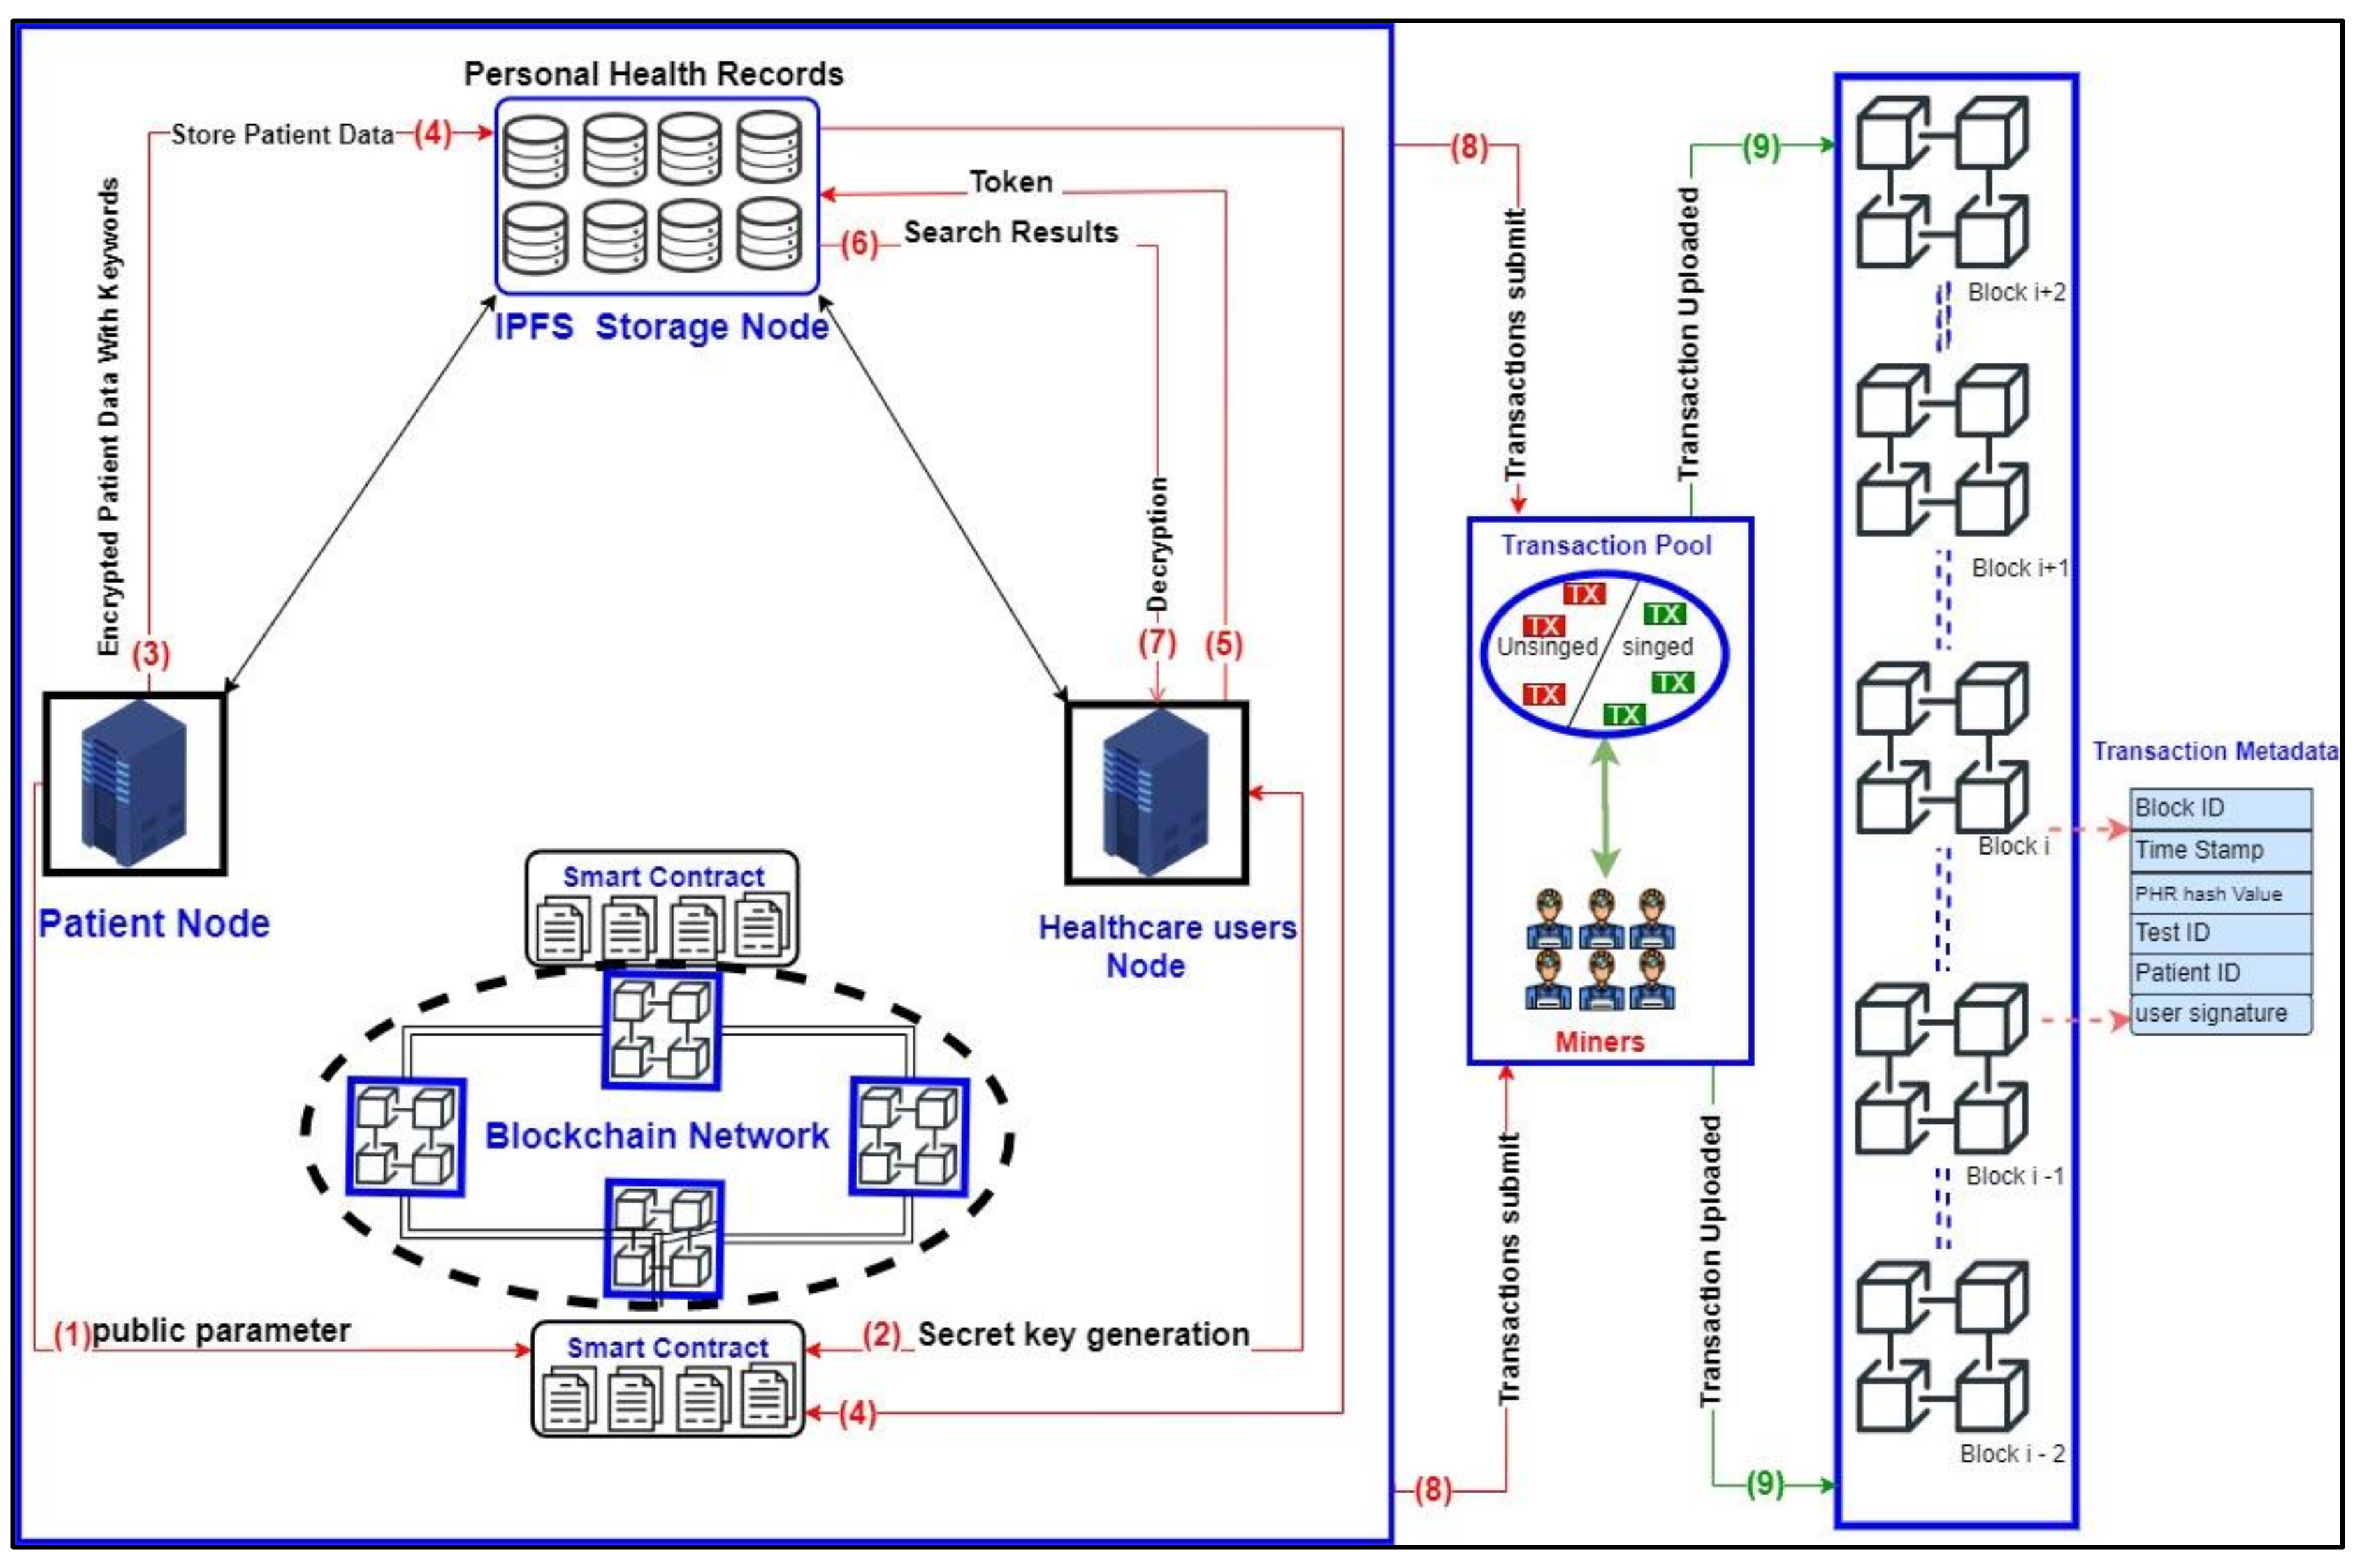
Figure 1: Blockchain-Based Access Control Scheme for Secure Shared Personal ... Man-in-the-middle (MITM) attacks are when a third party wishes to eavesdrop or intercept a message, and sometimes alter the intended message for the recipient. The two parties openly receive messages without verifying the sender, so they do not realize an adversary has inserted themselves into the communication line. Mutual authentication can prevent MITM attacks because both the sender and recipient verify each other before sending them their message keys, so if one of the parties is not verified to be who they claim they are, the session will end. Replay attack A replay attack is similar to a MITM attack in which older messages are replayed out of context to fool the server. However, this does not work against schemes using mutual authentication because timestamps are a verification factor that are used in the protocols. If the change in time is greater than the maximum allowed time delay, the session will be aborted. Similarly, messages can include a randomly generated number to keep track of when a message was sent. Spoofing attack Spoofing attacks rely on using false data to pose as another user in order to gain access to a server or be identified as someone else. Mutual authentication can prevent spoofing attacks because the server will authenticate the user as well, and verify that they have the correct session key before allowing any further communication and access. Impersonation attacks Impersonation attacks refer to malicious attacks where a user or individual pretends to be an authorized user to gain unauthorized access to a system while feigning permission. When each party authenticates the other, they send each other a certificate that only the other party knows how to unscramble, verifying themselves as a trusted source. In this way, adversaries cannot use impersonation attacks because they do not have the correct certificate to act as if they are the other party. Mutual authentication also ensures information integrity because if the parties are verified to be the correct source, then the information received is reliable as well.
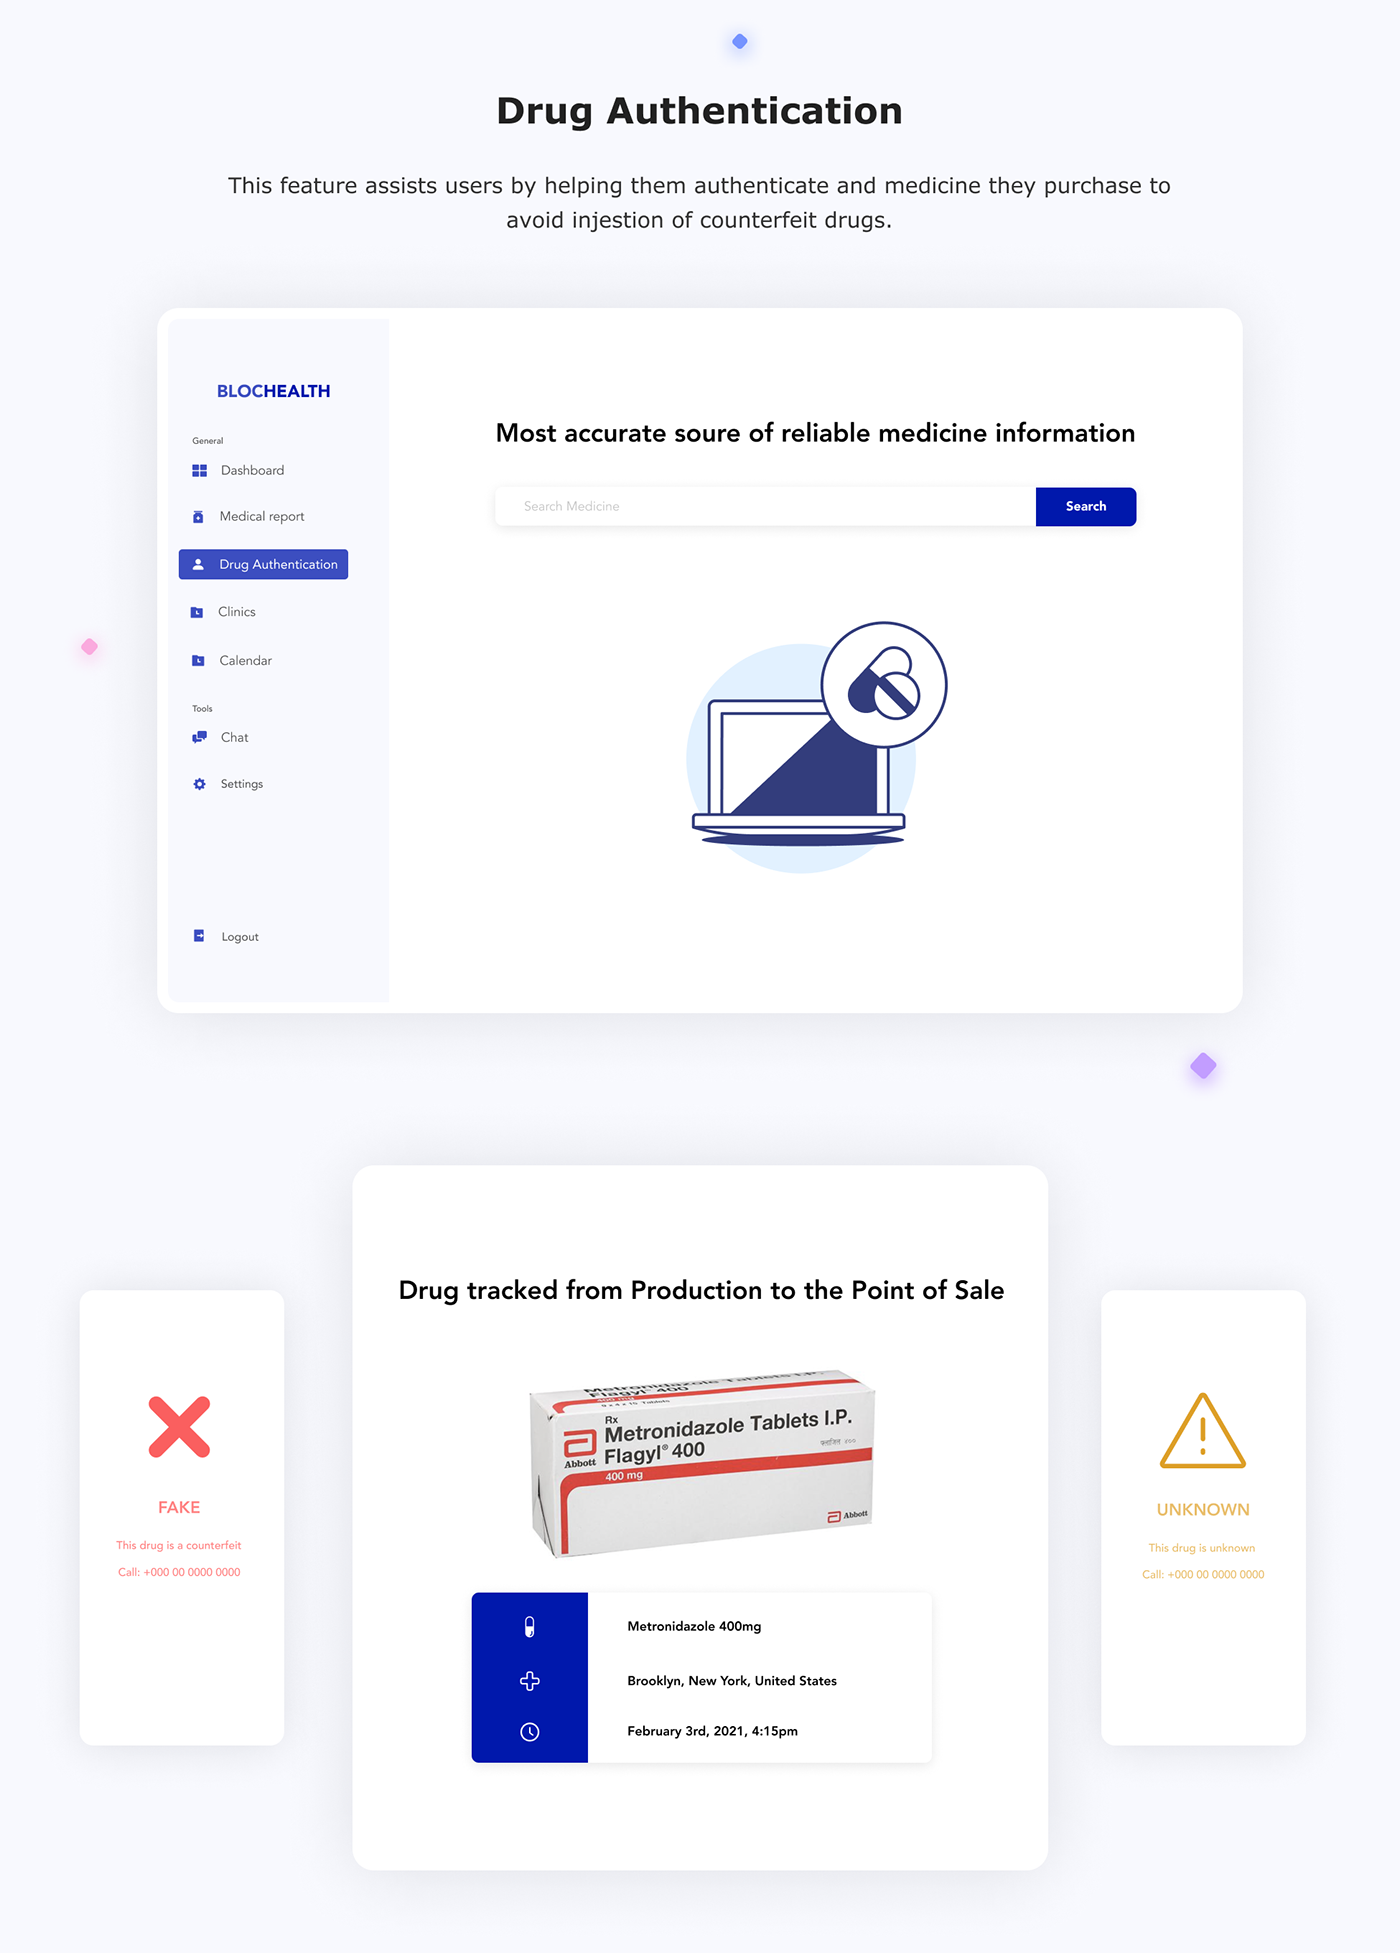
Figure 2: Blockchain in Healthcare - UI/UX Case Study :: Behance mHealth (also written as m-health or mhealth), an abbreviation for mobile health, is the practice of medicine and public health supported by mobile devices. The term is most commonly used in reference to using mobile communication devices, such as mobile phones, tablet computers and personal digital assistants (PDAs), and wearable devices such as smart watches, for health services, information and data collection. The mHealth field has emerged as a sub-segment of eHealth and digital health, the use of information and communication technology (ICT), such as computers, mobile phones, communications satellite, patient monitors, etc., for health services and information. mHealth applications include the use of mobile devices in collecting community and clinical health data, delivery/sharing of healthcare information for practitioners, researchers and patients, real-time monitoring of patient vital signs, the direct provision of care (via mobile telemedicine) as well as training and collaboration of health workers. In 2019, the global market for mHealth apps was estimated at US$17.92 billion, with a compound annual growth rate of 45% predicted from 2020 to 2027. While mHealth has application for industrialized nations, the field has emerged in recent years as largely an application for developing countries, stemming from the rapid rise of mobile phone penetration in low-income nations. The field, then, largely emerges as a means of providing greater access to larger segments of a population in developing countries, as well as improving the capacity of health systems in such countries to provide quality healthcare. Within the mHealth space, projects operate with a variety of objectives, including increased access to healthcare and health-related information (particularly for hard-to-reach populations); improved ability to diagnose and track diseases; timelier, more actionable public health information; and expanded access to ongoing medical education and training for health workers.
mHealth broadly encompasses the use of mobile telecommunication and multimedia technologies in health and medical care. The field broadly encompasses the use of mobile telecommunication and multimedia technologies in health care delivery. The term mHealth was coined by Robert Istepanian as use of "emerging mobile communications and network technologies for healthcare". A definition used at the 2010 mHealth Summit of the Foundation for the National Institutes of Health (FNIH) was "the delivery of healthcare services via mobile communication devices". The GSM Association representing the worldwide mobile communications industry published a report on mHealth in 2010 describing a new vision for healthcare and identified ways in which mobile technology might play a role in innovating healthcare delivery systems and healthcare system cost management. While there are some projects that are considered solely within the field of mHealth, the linkage between mHealth and eHealth is unquestionable. For example, an mHealth project that uses mobile phones to access data on HIV/AIDS rates would require an eHealth system in order to manage, store, and assess the data. Thus, eHealth projects many times operate as the backbone of mHealth projects. In a similar vein, while not clearly bifurcated by such a definition, eHealth can largely be viewed as technology that supports the functions and delivery of healthcare, while mHealth rests largely on providing healthcare access. Because mHealth is by definition based on mobile technology such as smartphones, healthcare, through information and delivery, can better reach areas, people, and/or healthcare practitioners with previously limited exposure to certain aspects of healthcare. The National Institute for Health and Care Research (NIHR) has published a review of research on how mHealth and digital health technologies can help manage health conditions.
Education and awareness Helpline Diagnostic and treatment support Communication and training for healthcare workers Disease and epidemic outbreak tracking Remote monitoring Remote data collection Middle income and especially low-income countries face a plethora of constraints in their healthcare systems. These countries face a severe lack of human and physical resources, as well as some of the largest burdens of disease, extreme poverty, and large population growth rates. Additionally, healthcare access to all reaches of society is generally low in these countries.
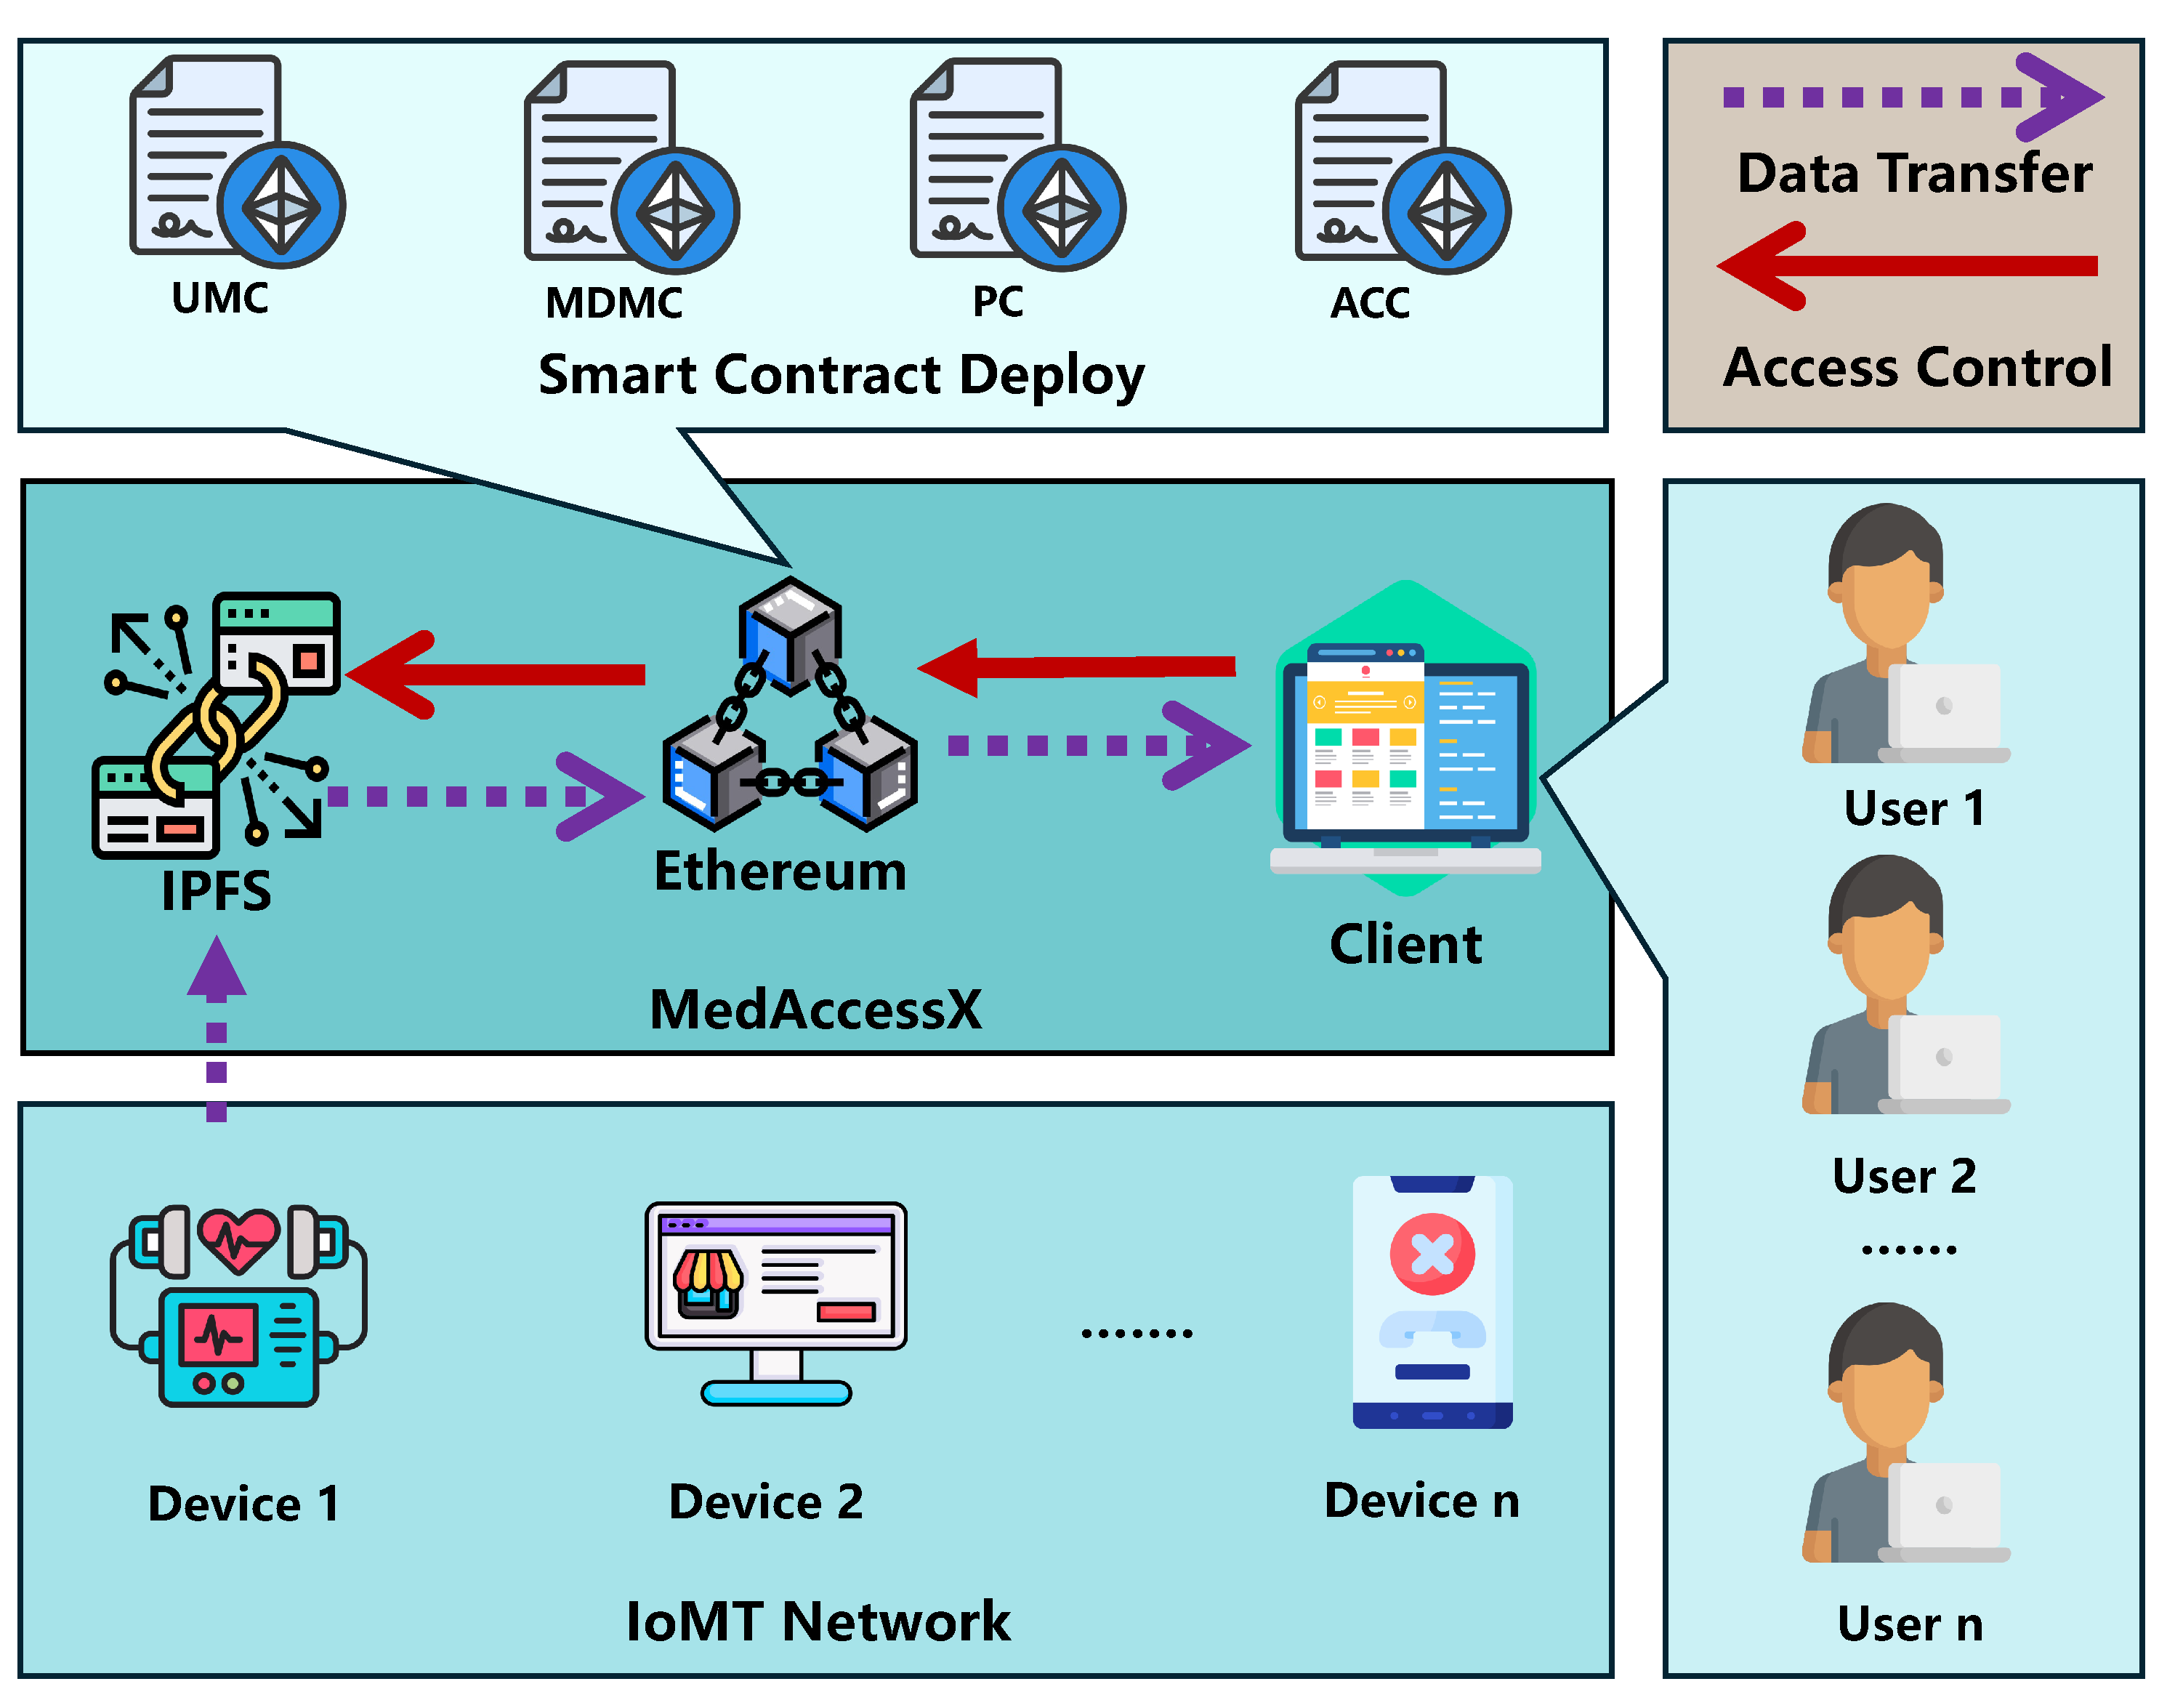
According to a World Health Organization (WHO) report from June 2011, higher-income countries show more mHealth activity than do lower-income countries (as consistent with eHealth trends in general). Countries in the European Region are currently the most active and those in the African Region the least active. The WHO report findings also included that mHealth is most easily incorporated into processes and services that historically use voice communication through conventional telephone networks. The report was the result of a mHealth survey module designed by researchers at the Earth Institute's Center for Global Health and Economic Development, Columbia University. The WHO notes an extreme deficit within the global healthcare workforce. The WHO notes critical healthcare workforce shortages in 57 countries—most of which are characterized as developing countries—and a global deficit of 2.4 million doctors, nurses, and midwives. The WHO, in a study of the healthcare workforce in 12 countries of Africa, finds an average density of physicians, nurses and midwives per 1000 population of 0.64. The density of the same metric is four times as high in the United States, at 2.6. The burden of disease is additionally much higher in low- and middle-income countries than high-income countries. The burden of disease, measured in disability-adjusted life year (DALY), which can be thought of as a measurement of the gap between current health status and an ideal situation where everyone lives into old age, free of disease and disability, is about five times higher in Africa than in high-income countries. In addition, low- and middle-income countries are forced to face the burdens of both extreme poverty and the growing incidence of chronic diseases, such as diabetes and heart disease, an effect of new-found (relative) affluence. Considering poor infrastructure and low human resources, the WHO notes that the healthcare workforce in sub-Saharan Africa would need to be scaled up by as much as 140% to attain international health development targets such as those in the Millennium Declaration. The WHO, in reference to the healthcare condition in sub-Saharan Africa, states: Figure 3: MedAccessX: A Blockchain-Enabled Dynamic Access Control Framework for ...
The problem is so serious that in many instances there is simply not enough human capacity even to absorb, deploy and efficiently use the substantial additional funds that are considered necessary to improve health in these countries. Mobile technology has made a recent and rapid appearance into low- and middle-income nations. While, in the mHealth field, mobile technology usually refers to mobile phone technology, the entrance of other technologies into these nations to facilitate healthcare are also discussed here.
With the global mobile phone penetration rate drastically increasing over the last decade, mobile phones have made a recent and rapid entrance into many parts of the low- and middle-income world. Improvements in telecommunications technology infrastructure, reduced costs of mobile handsets, and a general increase in non-food expenditure have influenced this trend. Low- and middle-income countries are utilizing mobile phones as "leapfrog technology" (see leapfrogging). That is, mobile phones have allowed many developing countries, even those with relatively poor infrastructure, to bypass 20th century fixed-line technology and jump to modern mobile technology. The number of global mobile phone subscribers in 2007 was estimated at 3.1 billion of an estimated global population of 6.6 billion (47%). These figures are expected to grow to 4.5 billion by 2012, or a 64.7% mobile penetration rate. The greatest growth is expected in Asia, the Middle East, and Africa. In many countries, the number of mobile phone subscribers has bypassed the number of fixed-line telephones; this is particularly true in developing countries. Globally, there were 4.1 billion mobile phones in use in December 2008. See List of countries by number of mobile phones in use. While mobile phone penetration rates are on the rise, globally, the growth within countries is not generally evenly distributed. In India, for example, while mobile penetration rates have increased markedly, by far the greatest growth rates are found in urban areas. Mobile penetration, in September 2008, was 66% in urban areas, while only 9.4% in rural areas. The all India average was 28.2% at the same time. So, while mobile phones may have the potential to provide greater healthcare access to a larger portion of a population, there are certainly within-country equity issues to consider. Mobile phones are spreading because the cost of mobile technology deployment is dropping and people are, on average, getting wealthier in low- and middle-income nations. Vendors, such as Nokia, are developing cheaper infrastructure technologies (CDMA) and cheaper phones (sub $50–100, such as Sun's Java phone). Non-food consumption expenditure is increasing in many parts of the developing world, as disposable income rises, causing a rapid increase in spending on new technology, such as mobile phones. In India, for example, consumers have become and continue to become wealthier.
Consumers are shifting their expenditure from necessity to discretionary. For example, on average, 56% of Indian consumers' consumption went towards food in 1995, compared to 42% in 2005. The number is expected to drop to 34% by 2015. That being said, although total share of consumption has declined, total consumption of food and beverages increased 82% from 1985 to 2005, while per-capita consumption of food and beverages increased 24%. Indian consumers are getting wealthier and they are spending more and more, with a greater ability to spend on new technologies.
Patient monitoring devices Mobile telemedicine/telecare devices Microcomputers Data collection software Mobile Operating System Technology Mobile applications (e.g., gamified/social wellness solutions) Chatterbots The first NIH mHealth Training Institute was held at UCLA to serve as an incubator for developing transdisciplinary scientists capable of co-creating mHealth solutions for complex healthcare problems. The week-long workshop is grounded in a team science model that emphasizes both information transaction and relationship development in the advancement of transdisciplinary mHealth teams capable of impactful healthcare solutions. 2011 – The mHealth Evidence Workshop A collaborative effort involving NSF, NIH, RWJF, and McKesson Foundation, explored mobile health technology evaluation to outline an approach to evidence generation in the field of mHealth that would ensure research is conducted on a rigorous empirical and theoretic foundation.
As a follow-up to the mHealth Evidence Workshop, NSF launched the Smart Health and Wellbeing program to address fundamental technical and scientific issues that would support the much-needed transformation of healthcare from reactive and hospital-centered to preventive, proactive, evidence-based, person-centered, and focused on wellbeing rather than disease. ASSIST Engineering Research Center (ERC) NSF and NIH initiated a joint research program specifically focusing on mHealth, following up on the insights gained from the mHealth Evidence Workshop. The Engineering Research Center ASSIST ERC at NC State University was established to further mHealth research by developing leading-edge systems for high-value applications such as healthcare and IoT by integrating fundamental advances in energy harvesting, low-power electronics, and sensors with a focus on usability and actionable data. 2013 – Wearable technology Around this time, Fitbit (originally Healthy Metrics Research, Inc.) also emerged, pioneering wearable health technology. 2014 – The Big Data To Knowledge (BD2K) Initiative The NIH BD2K Centers of Excellence program provided a significant boost to mHealth research, leading to 12 research centers, like the Mobile Data To Knowledge (MD2K) headquartered at the University of Memphis and Stanford's Center for Mobility Data Integration to Insight (Mobilize), to facilitate studies and innovation in the field. 2015 – Advancements in wearable technology Wearable devices, such as smartwatches and fitness trackers, have become more sophisticated, enabling continuous health monitoring, activity tracking, and integration with mobile health apps. All of Us mHealth gained prominence in the All of Us program, a precision medicine initiative aiming to collect health data from diverse populations. The launch of smartwatches, particularly the Apple Watch, further emphasized the integration of wearables and health tracking. 'mHealthHUB The mHealthHUB is launched as a virtual forum where technologists, researchers, and clinicians connect, learn, share, and innovate on mHealth tools to transform healthcare. Focused on creating an innovation ecosystem that fosters the collaborative team science essential for mHealth and data science innovations, the site becomes a collaboratory "watering hole" for the mHealth research community. 2017 – NSF Center for Underserved Populations The NSF established the Engineering Research Center for Precise Advanced Technologies and Health Systems for Underserved Populations, emphasizing the integration of engineering research and education with technological innovation to transform national prosperity, health, and security.
Emergency response systems (e.g., road traffic accidents, emergency obstetric care). Human resources coordination, management, and supervision. Mobile synchronous (voice) and asynchronous (SMS) telemedicine diagnostic and decision support to remote clinicians. Clinician-focused, evidence-based formulary, database and decision support information available at the point of care. Pharmaceutical supply chain integrity and patient safety systems (e.g. Sproxil and mPedigree).
Clinical care and remote patient monitoring Health extension services. Inpatient monitoring. Health services monitoring and reporting. Health-related mLearning for the general public. Public health services, for example, tobacco cessation Mental health promotion and illness prevention Training and continuing professional development for health care workers. Health promotion and community mobilization. Support of long-term conditions, for example medication reminders and diabetes self-management. Peer-to-peer personal health management for telemedicine. Patient participation and social mobilisation for infectious disease prevention (e.g. Participatient). Surgical follow-up, such as for major joint arthroplasty patients. Mobile social media for global health personnel; for example, the capacity to facilitate professional connectedness, and to empower health workforce. According to the Vodafone Group Foundation on February 13, 2008, a partnership for emergency communications was created between the group and United Nations Foundation. Such partnership will increase the effectiveness of the information and communications technology response to major emergencies and disasters around the world.
Health 2.0 Health informatics Healthcare workforce information systems Hospital-at-home Open source software packages for mHealth Telehealth Telemedicine service providers 2. System Architecture & Core Working Principles Official websites use .gov A .gov website belongs to an official government organization in the United States.
Secure .gov websites use HTTPS A lock ( ) or https:// means you've safely connected to the .gov website. Share sensitive information only on official, secure websites. sharing, adaptation, distribution and reproduction in any medium or format, as long as you give appropriate credit to the intended use is not permitted by statutory regulation or exceeds the permitted use, you will need to obtain permission directly from the copyright holder. To view a copy of this licence, visit http://creativecommons.org/licenses/by/4.0/ .
Ensuring privacy and confidentiality in healthcare data management remains a critical challenge. Traditional centralized access control mechanisms are susceptible to security breaches, including unauthorized access, data leakage, and single points of failure, as well as privacy violations such as patient record exposure and improper data sharing. To address these issues, this paper proposes ACHealthChain, a blockchain-based framework leveraging Hyperledger Fabric for decentralized and transparent access control. The framework integrates the InterPlanetary File System (IPFS) for decentralized storage and ensures privacy through Hyperledger Fabric channels. ACHealthChain features PolicyChain for fine-grained access control and revocation, structuring patient health data into separate subchains for EHRs and diagnoses with permissioned access.
Additionally, LogChain enhances auditing and accountability. A series of experiments evaluate ACHealthChain’s performance and scalability, considering metrics such as throughput, latency, and resource utilization. Results demonstrate that ACHealthChain improves throughput by 19.7% and reduces latency by 87%, outperforming existing frameworks built on the same platform. The scalability analysis further confirms the framework’s capability to handle increasing workloads within an expanding blockchain network. ACHealthChain presents a promising solution for secure and efficient healthcare data sharing with potential real-world applications.
The healthcare industry has rapidly embraced digital technologies, with Electronic Health Records (EHRs) becoming the standard for storing and managing patient information 1 . EHRs improve accessibility, streamline workflows, and facilitate data-driven research 2 , 3 . However, these advancements raise critical privacy and security concerns 4 . Unauthorized access or breaches can lead to identity theft, insurance fraud, and compromised healthcare decisions, making robust security measures essential. Traditional access control models, such as role-based access control (RBAC) 5 , regulate data access through predefined roles and privileges. While effective, these models struggle to meet the evolving needs of dynamic healthcare environments. Healthcare professionals require fine-grained access control, ensuring authorized individuals can access specific parts of a patient’s records. Additionally, auditing and compliance enforcement are challenging with conventional models.
Blockchain technology 6 , 7 has emerged as a promising solution for secure and privacy-preserving access control in healthcare. Originally developed for cryptocurrencies like Bitcoin 8 , blockchain is now widely applied across various domains due to its key properties. Its decentralized nature ensures data integrity and availability, eliminating reliance on a central authority. Consensus mechanisms validate transactions, while transparency 9 enables auditable records, enhancing accountability. Additionally, immutability 10 prevents unauthorized modifications, ensuring trust in patient records. Smart contracts automate fine-grained access control, ensuring only authorized individuals can access or modify healthcare data.
Storing complete patient EHRs directly on a blockchain is impractical due to scalability and privacy concerns. Instead, the InterPlanetary File System (IPFS) 11 provides a decentralized solution for managing large medical files, using cryptographic hashes to ensure data integrity and efficient retrieval. Integrating blockchain-based access control with IPFS allows secure storage and management of encrypted EHR data while maintaining transparency and scalability.
Popular blockchain platforms, such as Ethereum 12 and Hyperledger Fabric 13 , offer different advantages based on decentralization, privacy, and performance needs. This paper employs the Hyperledger Fabric as a permissioned blockchain framework for providing features like modular architecture, flexible consensus protocols, and privacy through channels. Hyperledger Fabric 13 is often used in various industries such as the healthcare industry, where privacy, scalability, and fine-grained access control are essential.
In this paper, we introduce ACHealthChain, a blockchain-based framework designed to enhance access control and privacy preservation in healthcare data management. Unlike traditional approaches that rely on multiple channels in Hyperledger Fabric, ACHealthChain leverages multiple chaincodes to reduce communication overhead and achieve modularity within the same blockchain network. This approach allows for separate development and control of smart contracts, ensuring flexibility, improved isolation, and tailored access control policies for different stakeholders, such as patients and healthcare providers.
By implementing distinct chaincodes, the framework enables fine-grained access control, ensuring that patients retain full authority to grant or revoke permissions over their EHRs, thereby enhancing privacy and security. The major contributions of this work are summarized as follows: Novel blockchain-based access control framework: We propose ACHealthChain, which introduces a dedicated PolicyChain to facilitate fine-grained access control and revocation mechanisms. The framework separates patient healthcare data into EHRs and diagnoses, distributing them across different permissioned subchains for improved data management and security.
Enhanced auditability and accountability: ACHealthChain integrates a LogChain mechanism to ensure transparent tracking of data access and usage, providing robust auditing capabilities crucial for regulatory compliance and security. Implementation and performance evaluation: The framework is implemented on Hyperledger Fabric, utilizing the Hyperledger Caliper tool for comprehensive evaluation. This combination allows for an accurate, realistic assessment of the framework’s performance and enables meaningful comparisons with other frameworks.
Scalability and performance superiority: Experimental results demonstrate that ACHealthChain achieves high efficiency with superior throughput and low latency compared to existing frameworks built on the same platform. The scalability analysis confirms its capability to handle increasing workloads in real-world healthcare settings. The rest of this paper is organized as follows: section “ Background and related work ” provides background information and discusses related work in the field of blockchain-based access control and privacy preservation in healthcare. Section “ ACHealthChain: proposed framework ” presents the proposed framework, providing a detailed description of its key components and functionalities. Section “ ACHealthChain: implementation and scenarios ” discusses the proposed framework implementation, including scenarios related to patient, healthcare provider manipulation, and healthcare data access. Section “ Security and privacy analysis ” discusses the security and privacy aspects of the proposed framework. Section “ Evaluation and experimental results ” presents the evaluation and experimental results obtained from the framework. Finally, Section “ Conclusion ” concludes the paper by summarizing the contributions, discussing limitations, and providing directions for future research.
This section effectively provides the necessary background information and presents the relevant work of blockchain based access control frameworks in the healthcare sector. It offers a brief overview of each framework, highlighting their key features and limitations. Blockchain technology 14 is a decentralized and distributed ledger technology that enables secure and transparent recording of transactions and data. Initially introduced as the underlying technology for cryptocurrencies like Bitcoin 8 , blockchain has since expanded its applications to various industries beyond finance. Platforms such as Ethereum 12 , Hyperledger Fabric 13 , and others have further developed blockchain technology, offering more flexible and customizable solutions for specific use cases. At its core, a blockchain is a growing chain of blocks, each containing a list of transactions or data. These blocks are linked using cryptographic hashes, forming an immutable and tamper-resistant record of all stored transactions or data.
Blockchain technology’s decentralized nature eliminates reliance on central authorities or intermediaries, operating instead on a network of nodes that collectively validate transactions. Consensus protocols, such as Proof of Work (PoW) 8 , Proof of Stake (PoS) 15 , and Practical Byzantine Fault Tolerance (PBFT) 16 , ensure transaction validity and maintain blockchain integrity by enabling nodes to agree on the blockchain’s state.
Transparency and immutability form the foundational aspects of blockchain technology 9 , 10 . Transparency ensures that all participants in the network can independently verify and validate recorded transactions or data entries, fostering trust and accountability. Immutability guarantees that once a transaction or data is added to the blockchain, it cannot be altered or deleted without detection. Each block contains a reference to the previous block, making tampering highly impractical as any changes to previous blocks would require re-computing the cryptographic hashes of subsequent blocks.
Blockchain technology offers enhanced security due to its decentralized nature, which makes it more resilient to attacks and data breaches. Additionally, its transparency and immutability enable easy auditability and traceability of assets or data. However, these features also pose challenges in terms of privacy protection, as sensitive information is exposed to all network participants. Various approaches, such as using permissioned or private blockchains, restrict access to a predefined set of participants, allowing for better control over data access and enhancing privacy.
Advancements in cryptography have led to the development of privacy-enhancing technologies for blockchain systems. Techniques like Secure Multiparty Computation (SMPC) 17 and homomorphic encryption 18 enable secure computation and verification without revealing sensitive data. For secure data storage, blockchain-based solutions have emerged that combine on-chain verification with off-chain storage 19 . This hybrid approach typically utilizes encrypted databases or decentralized file systems like IPFS 11 to store sensitive data separately from the public ledger while maintaining cryptographic links to the blockchain. Merkle trees 20 and other authenticated data structures provide integrity proofs for this off-chain data.
Furthermore, selective disclosure mechanisms, implemented through smart contracts and zero-knowledge techniques 21 , allow users to reveal only necessary information while preserving overall data privacy. In recent years, various proposals for blockchain-based access control frameworks have emerged to enhance healthcare privacy, as discussed in the following sub-section.
This section reviews relevant work, outlining key features and limitations of each framework. A summary is presented in Table 1 . A qualitative comparison of various blockchain-based frameworks for managing access control in healthcare environments. The qualitative metrics are classified as follows-Throughput (High: > 300 TPS, Medium: 100–300 TPS, Low: < 100 TPS), Latency (Low: < 100 ms, Medium: 100–500 ms, High: > 500 ms), and Storage Overhead (Low: < 500 MB, Medium: 500 MB-2 GB, High: > 2 GB)-based on common blockchain performance benchmarks and reported experimental results in the cited frameworks 3. Software Implementation, Frameworks & Protocols MedRec 22 introduces blockchain-based EHRs management, overcoming traditional storage limitations with smart contracts.
It employs three key contracts: Register Contract (RC) for privacy, Patient-Provider Relationship Contract (PPR) for data storage, and Summary Contract (SC) for record tracking. While ensuring secure data storage, MedRec lacks fine-grained access control enforcement. MeDShare 23 employs a permissioned blockchain approach to enable patients to manage and monitor their EHRs through smart contracts. It operates through three layers: a data layer for user classification, a data query layer for access management, and a structural layer for authentication and data verification. Requests are verified by an authenticator, and smart contracts enforce policy compliance. MeDShare distinguishes between high-sensitive and low-sensitive data, aiming to minimize breach reports for the latter. However, its performance evaluation focuses mainly on network latency, potentially limiting a holistic assessment.
24 is a permissioned blockchain framework built on Hyperledger 13 , aiming to provide data access control. Original EHRs reside in cloud storage, while their hashes are stored on the blockchain. allows data owners to create smart contracts for access control, known as Discretionary Access Control (DAC). The framework employs the PBFT consensus protocol 16 for blockchain integrity. However, lacks features for essential access control aspects like delegation and revocation.
Healthchain 25 is a hybrid blockchain framework addressing privacy and storage costs for large-scale EHRs. It utilizes IPFS 11 for efficient storage while preserving patient privacy on the public blockchain network. It supports fine-grained access control, enabling patients to revoke access dynamically by updating their keys on the blockchain. However, its access control is restricted to predefined roles, and it lacks flexible policy definition. Processing times are relatively high due to RSA cryptography, despite its robust security features.
SPChain 26 is a blockchain framework designed for secure medical data transfer and privacy preservation in e-health systems. It employs keyblock and microblock as blockchains for fast retrieval of patients’ EHRs. Keyblocks store register transactions, while microblocks link label and medical transactions to individual patients. SPChain ensures patient privacy using proxy re-encryption techniques and chameleon hash functions 31 to store medical history securely. The system employs three transaction types: register, label, and medical. It combines PoW 10 and Byzantine Fault Tolerance (BFT) 32 for consensus. While offering advantages like low storage overhead and robust security, SPChain should improve communication efficiency and throughput for enhanced performance.
BCHealth 27 is a blockchain-based architecture allowing data owners to set access permissions for EHRs. Patient data isn’t shared on the blockchain without patient consent. It comprises two chains: the data chain storing EHRs and the access control chain managing access rules. A clustering technique enhances scalability and capacity, enabling effective data and transaction management. BCHealth can promptly alert physicians about disease symptoms, enabling timely action. It employs the Proof-of-Authority (PoA) 33 consensus protocol for efficiency and security. While it offers efficient computation and processing, retrieving health information may experience slight delays, and storage overhead could be higher than centralized solutions. Optimizing node count and clustering arrangement is essential for improved performance and resource utilization in BCHealth.
The blockchain-assisted SABE framework 28 enhances e-health access control using Attribute-Based Encryption (ABE) 34 . It enables keyword-based searches and ensures fairness, security, and efficiency through blockchain integration. Each hospital has a private blockchain, while a consortium blockchain stores EHR keywords. Access records are audited on the blockchain, and encrypted EHRs are stored in the cloud for quick and lightweight decryption. This approach prioritizes attribute privacy and improves the efficiency of Cloud Service Provider (CSP) searches, offering cost-effective solutions. However, decentralization may be compromised depending on the CSP.
Díaz et al. 29 present a dual-channel blockchain framework utilizing Hyperledger Fabric for scalable EHR management in healthcare systems. This system is structured around a decentralized network of hospitals, labs, research centers, and insurance agencies, where each organization manages user access to sensitive health data via distinct roles. Employing the RAFT consensus mechanism, the model uses separate channels to optimize scalability and data privacy, allowing unique data access and permissions per channel. While the dual-channel model provides reduced latency and improved throughput, further refinement is needed for enhanced interoperability and storage efficiency.
Lax et al. 30 proposed a blockchain-based framework that decouples patient identities from their e-health records while restricting access to authorized entities. The system utilizes digital identities for access control and is built on the Ethereum blockchain. However, the requirement for patient authentication during every EHR operation may hinder usability in clinical settings. Additionally, using a public blockchain with the PoS consensus protocol 15 introduces inherent latency that could impact time-sensitive healthcare workflows. The authors note that the framework remains a theoretical proposal without full implementation.
Our proposed framework, ACHealthChain, addresses key limitations found in existing blockchain-based access control frameworks, as outlined in Table 1 . Specifically, these solutions face challenges such as the lack of fine-grained access control, high computational overhead, scalability constraints, and dependence on centralized components or external storage solutions. Notably, MedRec lacks fine-grained access control, while frameworks such as MediChain TM and Díaz et al. exhibit storage scalability limitations. Additionally, solutions built on public blockchains, such as SPChain and Lax et al., suffer from high computational overhead and latency due to consensus mechanisms like PoW and PoS. In contrast, ACHealthChain leverages Hyperledger Fabric with PBFT consensus to achieve high throughput and low latency while maintaining a decentralized, permissioned environment that supports structured data management. Furthermore, ACHealthChain minimizes storage overhead by integrating IPFS, enhancing data availability and privacy. This combination ensures that patient data remains secure and accessible only to authorized entities while enabling efficient policy-based access control with revocation capabilities.
We propose the ACHealthChain framework, which leverages blockchain technology to establish secure and decentralized access control management in the healthcare domain. The framework is implemented on Hyperledger Fabric, a permissioned blockchain platform 13 , and is structured into three layers: the storage layer, the control layer, and the access layer-each serving a distinct role in ensuring secure and decentralized access control, as depicted in Fig. 1 . The Storage Layer forms the foundation of the architecture, ensuring the secure and immutable storage of healthcare data.
Instead of utilizing Blockchain for healthcare data storage, the proposed framework utilizes the IPFS distributed storage system, which offers several benefits when used in conjunction with blockchain technology 11 : Decentralized storage: IPFS utilizes a distributed network of nodes for decentralized storage, increasing data availability and resistance to censorship or single points of failure.
Immutable content addressing: IPFS employs content-based addressing, where files are identified and retrieved based on their content, ensuring secure and immutable storage. This feature is especially valuable for maintaining data integrity in blockchain applications. Reduced redundancy: IPFS employs data deduplication, storing files with identical content only once. This reduces redundancy and optimizes storage space.
Faster data retrieval: IPFS uses a distributed hash table to locate and retrieve files. It accelerates data retrieval by automatically searching for the nearest nodes with the file, resulting in faster and more efficient data retrieval compared to centralized storage systems. Data integrity and authenticity: IPFS ensures data integrity by utilizing cryptographic hashing. The unique hash of each file identifies its content, preventing tampering or unauthorized modifications without detection.
For privacy protection, healthcare data is encrypted using the Advanced Encryption Standard (AES) 35 before being stored in IPFS storage. This choice of AES is preferred over other encryption schemes, such as ABE 34 , which is renowned for its complex fine-grained access control capabilities. AES is chosen due to its widespread adoption and superior performance compared to ABE in handling large volumes of data, making it particularly suitable for securing EHRs 36 . This decision is especially relevant given that our framework utilizes a custom blockchain called PolicyChain for fine-grained access control.
While the Storage Layer ensures secure and decentralized data storage, managing access control policies and enforcing security mechanisms requires a higher-level framework. This is where the Control Layer comes into play. It governs the operational logic of ACHealthChain by defining policies, enforcing data access rules, and ensuring transaction integrity through smart contracts and consensus mechanisms, which collectively regulate interactions between stakeholders while maintaining data security and privacy.
The control layer governs the ACHealthChain framework by enforcing access policies and ensuring proper data flow between network participants. It comprises smart contracts (chaincode), modular subchains, and a consensus protocol. In ACHealthChain, smart contracts-referred to as chaincode-encode the business logic governing transactions. Written in Java, chaincode executes on endorsing peers, validating transactions against predefined policies before appending them to the blockchain. Chaincode ensures automation, security, and compliance with access control rules.
In the proposed ACHealthChain framework, we aim to achieve modularity within the blockchain network by implementing different chaincodes rather than creating separate channels, which would result in increased computational and communication overhead. Each chaincode represents a unique set of rules and functions, encapsulating specific business logic. The isolation of chaincode logic facilitates easier maintenance and debugging, leading to improved overall network efficiency and minimizing the impact of changes to one part of the system on other parts, thereby enhancing system flexibility.
These chaincodes include EHRChain for secure sharing of EHRs between patients and healthcare providers, DiagnosisChain for sharing doctors’ diagnoses between patients and healthcare providers, PolicyChain for determining healthcare data access policies based on patient preferences, and LogChain for handling access logs data for both patients and healthcare providers, ensuring proper auditing and tracking of data access.
The transactions in EHRChain consist of the following tuples: EHRChainTx < Patient_ID, Timestamp, IPFS_EHR Address, Patient Signature, EHRChainTx ID> 4. Practical Deployment, Analysis & Case Studies EHRChainTx ID: the transaction’s identity is established by generating a hash of all its components, facilitating efficient retrieval and ensuring integrity.
Transactions within DiagnosisChain consist of the following components: DiagnosisChainTx < Healthcare Provider ID, Timestamp, patient_ID, IPFS_Diagnosis Address, healthcare provider Signature, DiagnosisChainTx ID> Healthcare Provider ID: the public key of the healthcare provider who initiates the transaction. Patient_ID: the patient’s public key, which is used to address them in the sub-chain of the EHRChain.
IPFS_Diagnosis Address: the hash address of the encrypted diagnosis is stored in IPFS storage. healthcare provider Signature: the encryption result is derived from the healthcare provider’s private key. DiagnosisChainTx ID: the transaction’s identity is established by generating a hash of all its components, facilitating efficient retrieval and ensuring integrity.
The transactions within PolicyChain consist of the following components: PolicyChainTx < Granter_ID, Grantee_ID, Timestamp, EHR_Type, IPFS_hash Address, enveloped symmetric_key, Start_Date, End_Date, isValidPolicy, Granter Signature, PolicyChainTx ID> . The granter or grantee can be a patient or healthcare provider. Grantee_ID: the public key of the grantee who is granted access to the healthcare data.
EHR_Type: the type of healthcare data that the authorized requester can access, e.g., ECG, EEG data. IPFS_hash Address: the hash address of the encrypted healthcare data is stored in IPFS storage. Enveloped_Symmetric_Key: the granter’s symmetric key is encrypted using the grantee’s ID (public key) in order to decrypt the returned healthcare data from the IPFS.
isValidPolicy: this is a boolean value that indicates the validity of the policy. It is set to TRUE for valid policies of accessing EHRs and FALSE for revoking access permission. PolicyChainTx ID: the transaction’s identity is established by generating a hash of all its components, facilitating efficient retrieval and ensuring integrity.
The transactions within LogChain consist of the following components: LogChainTX < Requester_ID, Timestamp, IPFS_EHR Address, Access_Logs, Requester Signature, LogChainTx ID> Access_Logs: The information includes a summary of the types of accessed EHRs, the individuals who accessed them, and other relevant details.
Requester Signature: the encryption result is derived from the Requester’s private key. LogChainTx ID: the transaction’s identity is established by generating a hash of all its components, facilitating efficient retrieval and ensuring integrity. The consensus protocol is a crucial mechanism in distributed systems, including blockchain networks, to establish agreement and consensus among multiple nodes regarding the validity and order of transactions or events. Its purpose is to ensure that all participants in the network reach a consistent state and agree on state changes. The ACHealthChain framework employs the PBFT consensus protocol 16 alongside the Raft ordering service 37 to ensure fault tolerance and consensus across nodes in the distributed network. The Raft enables leader election, log replication, and commit operations to ensure fault tolerance and consistency. Compared to Solo and Kafka ordering services, Raft offers advantages in terms of fault tolerance, log replication, and simplicity. Its robustness and reliability make it a suitable choice for achieving consensus in the ACHealthChain framework.
With a well-structured Control Layer governing transactions, policies, and security rules, it is essential to have a mechanism that ensures only authorized entities can interact with the system. The Access Layer serves this purpose by handling authentication, user registration, and identity management. This layer is responsible for verifying the credentials of participants, such as patients and healthcare providers, before they can interact with the blockchain network. By implementing robust authentication mechanisms and role-based access controls, the Access Layer reinforces the security and usability of the ACHealthChain framework.
The access layer in the ACHealthChain framework controls access permissions in the blockchain network, allowing only authenticated participants to interact with the system. It handles the registration and authentication processes for client nodes, prioritizing security and implementing effective authentication mechanisms. The registration module in the proposed framework handles identity registration and verification processes. It securely stores certificates and generates new certificates for verified participants. It validates participant identities using X.509 certificates 38 and utilizes a web service API for secure client access. In Hyperledger Fabric 13 , the Membership Service Provider (MSP) is responsible for managing participant identities and enforcing access control policies. The MSP issues digital certificates, maintains a Certificate Authority (CA), and ensures that only authorized participants can access the network.
In the proposed framework, the client nodes refer to the nodes that are used by patients and healthcare providers to interact with the healthcare blockchain network. These client nodes act as the endpoints for the users, allowing them to access and utilize the functionalities provided by the blockchain system. 5. Performance Evaluation & Extended Technical Observations Patients node: In this framework, each patient node has the responsibility of accessing and managing its EHRs, as well as setting privacy preferences to control who can access their healthcare data. Patient nodes employ Elliptic Curve asymmetric encryption, using their private key and the public key of the corresponding peer, to encrypt the data before sending it to the IPFS storage node. These nodes possess the capability to access and publish transactions, validate and commit new blocks of transactions received from consensus nodes to their local blockchain copy. Moreover, all patient nodes are capable of executing smart contracts.
Healthcare providers node: Healthcare provider nodes play a crucial role in the ACHealthChain framework by offering diagnoses based on healthcare data for specific patients and securely transmitting encrypted EHRs to the IPFS storage node. These EHRs may include diagnoses, medical laboratory reports, insurance documents, and other relevant information. Similar to patient nodes, healthcare provider nodes possess the same capabilities for blockchain operations, allowing them to access and publish transactions, validate and commit new blocks of transactions, and execute smart contracts.
With a solid understanding of the ACHealthChain framework in place, we now turn our attention to its implementation and explore various scenarios where it can be effectively applied. The use cases and scenarios where ACHealthChain demonstrates its potential to revolutionize access control in the healthcare industry. This section provides a detailed explanation of the implementation of the primary chaincodes utilized in the ACHealthChain framework. To facilitate interaction with the Blockchain network, we employ a web service API that grants secure access to clients. The ACHealthChain framework prioritizes security by incorporating authentication and verification processes through the MSP. MSP is an essential component of the Hyperledger Fabric framework 13 . The MSP acts as a trusted authority within the network and is responsible for issuing digital certificates to network participants. These certificates are used for identity authentication and are crucial for establishing trust within the network. The MSP maintains a public key infrastructure (PKI) that includes the CA to issue and sign certificates. By utilizing the MSP, the Hyperledger Fabric framework ensures that only authorized participants can access and interact with the network. The initial step involves enrolling the hospital’s administrator through the MSP and importing their identity into the wallet. This identity comprises essential components such as MSP ID, identity version, certificate type, private key, and a public certificate. Once enrolled, the administrator gains the ability to register and enroll new users. The system restricts user roles to patients or healthcare providers in accordance with the proposed framework.
The ACHealthChain framework is designed with four distinct subchains, each serving a specialized function to enhance security, privacy, and access control in managing EHRs: EHRChain: This subchain is responsible for securely storing and managing patients’ EHRs. It ensures that healthcare providers can access patients’ health records while restricting access to other providers’ diagnoses, thereby maintaining data separation and privacy.
DiagnosisChain: This subchain is dedicated to storing and organizing patient diagnoses separately from EHRs. By maintaining a distinction between health records and medical assessments, the framework upholds data modularity and prevents unauthorized inference attacks. PolicyChain: Serving as the core access control mechanism, the PolicyChain governs access permissions to both EHRs and diagnoses. It also facilitates the secure exchange of encrypted healthcare data stored on IPFS by providing the necessary enveloped symmetric key for decryption, ensuring that only authorized entities can access sensitive information.
LogChain: To enforce accountability and traceability, the LogChain records detailed logs of both authorized and unauthorized access attempts. This mechanism strengthens the framework’s security by enabling auditing and monitoring of all interactions within the system. To demonstrate the practical application of the ACHealthChain framework, we outline three key operational scenarios. These scenarios are accompanied by sequence diagrams and algorithms to provide a structured and clear illustration of system behavior: Patient scenario: In this scenario, patients store their EHRs in the EHRChain and define their privacy preferences. These preferences are transformed into access policies stored in the PolicyChain, ensuring that only authorized healthcare providers can access their health records.
Healthcare providers scenario: Healthcare providers add diagnoses to the DiagnosisChain based on the retrieved patients’ EHRs (via the Healthcare Data Access Scenario). Additionally, access control policies are updated to define which entities can view the diagnoses, ensuring secure and structured information management. Healthcare data access scenario: This scenario governs the retrieval of patient EHRs and diagnoses from the EHRChain and DiagnosisChain, respectively. Access control policies stored in the PolicyChain determine authorization for healthcare providers or patients to access specific records. Furthermore, all access attempts-both authorized and unauthorized-are logged in the LogChain for security and auditing purposes.
This structured approach ensures a logical and secure workflow. For instance, when a healthcare provider needs to add a diagnosis, they must first retrieve the relevant EHRs through the Healthcare Data Access Scenario. Once the necessary health records are obtained, they proceed with the Healthcare Providers Scenario to record their diagnosis. This modular and layered design enhances security, privacy, and efficiency in managing sensitive healthcare data. The following subsections provide an in-depth exploration of each scenario, detailing the sequence of operations and the interaction between different subchains in ACHealthChain.
Patients can interact with their EHRs and customize privacy preferences, selecting specific healthcare providers authorized to access and manage their records. This empowers patients by granting them control over who can view and handle their sensitive health information, as detailed in Algorithm 1. The patient scenario is illustrated in Fig. 2 and follows these steps: Upon successful identity validation, the patient is registered as a participant in the hospital network. A key pair (public key Pk and private key Sk) is generated and securely stored in the patient’s wallet.
The client app generates an AES symmetric key to encrypt the patient’s EHR, storing it securely in the patient’s wallet. The encrypted EHR is transmitted to an IPFS storage node, and its corresponding hash address is retrieved. The patient’s identity is verified via chaincode within the permissioned blockchain (EHRChain). Once verified, the hash address of the patient’s EHR is securely stored within EHRChain.
The patient sets privacy preferences, specifying authorized healthcare providers. These preferences are then sent to the blockchain network. The patient’s identity is verified using PolicyChain chaincode within the permissioned blockchain. Upon successful verification, the privacy preferences are securely stored in PolicyChain as transactions. These transactions contain details such as the patient’s public key, the authorized healthcare provider’s public key, timestamp, IPFS address of the EHR, EHR type, an encrypted symmetric key (enveloped with the provider’s public key), access duration, policy validation, and the patient’s signature.
If a patient decides to revoke a specific grantee’s permission to access the EHRs, he/she creates a policy transaction with “isValidPolicy = false” on the blockchain. When the requester attempts to access the EHRs, the PolicyChain’s chaincode first verifies the validation parameter “isValidPolicy” in the last policy transaction relevant to the patient and healthcare provider. If the validation is false, the healthcare provider will be denied access to the EHRs, as detailed in Algorithm 2.
Healthcare providers can access and manage their patients’ EHRs, contributing diagnoses as authorized entities. Their interactions are governed by access control policies, as detailed in Algorithm 3. The healthcare provider scenario is illustrated in Fig. 3 and follows these steps: Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/Decentralized%20identifier • https://en.wikipedia.org/wiki/Mutual%20authentication • https://en.wikipedia.org/wiki/MHealth • https://pmc.ncbi.nlm.nih.gov/articles/PMC12078686/
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.
Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Blockchain Based Access Control System For Healthcare.
[*] Metasploit Scan Running on Target Subnet for Blockchain Based Access Control System For Healthcare... [✓] SafeBreach / AttackIQ Continuous Exposure Agent Triggered ──────────────────────────────────────────────────────────────────────── [11:48:02.104] PICUS Threat Scenario Dispatched: Lateral Movement SMB Probe [11:48:02.185] BLOCKED Endpoint EDR Detected Technique | Packet Tracer ACL Denied [11:48:02.240] CYMULATE Prevention Rate = 96.8% | SIEM Latency = 38 ms [11:48:02.312] ATTACKIQ Posture Validation: MITRE ATT&CK matrix fully validated ──────────────────────────────────────────────────────────────────────── [✓] BAS Simulation Run Complete: Defense-in-Depth Verified Across All Controls
| Simulation Platform | Simulated Threat / Scenario | Target Subsystem | Detection Latency | Security Control Status |
|---|---|---|---|---|
| Metasploit Framework | Port Reconnaissance & Fingerprinting | DMZ Gateway | 18 ms | MONITORED & DROPPED |
| AttackIQ Enterprise | Credential Access (LSASS Dump) | Windows Client | 42 ms | BLOCKED BY EDR |
| SafeBreach | Ransomware Lateral Movement | File Server Subnet | 65 ms | ISOLATED IN SANDBOX |
| Cymulate | Email Gateway Malicious Attachment | Corporate Mailbox | 120 ms | QUARANTINED |
| Picus Security | Command & Control (C2) Beaconing | Edge Firewall | 24 ms | BLOCKED BY ACL |