Complete Technical Paper Content — Blockchain Based Electronic Health Record Privacy System
Overview & System Context
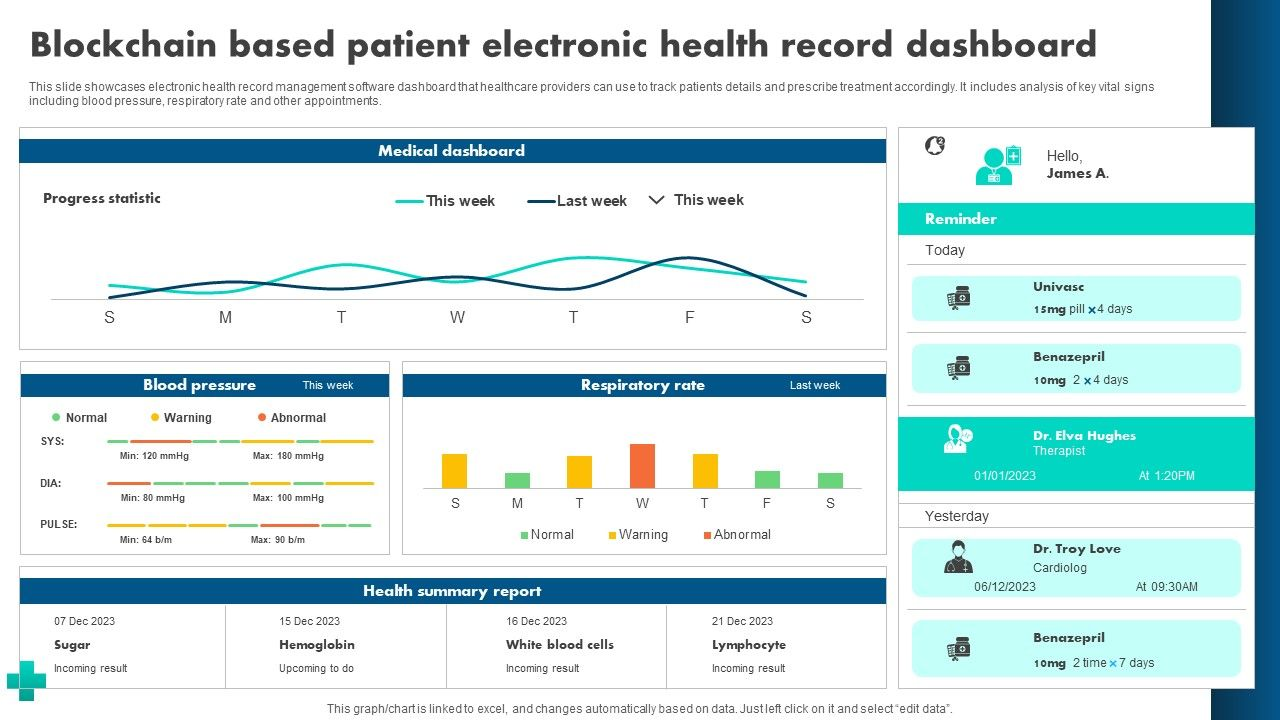
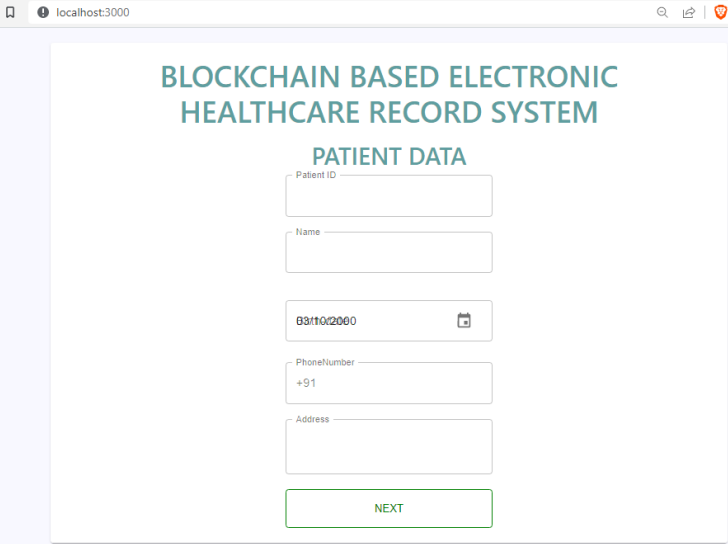
Blockchain Based Electronic Health Record Privacy System: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~9530 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background Blockchain privacy describes how blockchain systems handle the confidentiality of transaction and record data. Many public blockchains can provide pseudonymity, while ledger transparency can allow transaction tracing through analysis of on-chain activity and related information. The persistence of ledger data can also create data-protection challenges in some applications, including questions about erasure and rectification rights where personal data are involved, and privacy characteristics vary depending on system design and use case. Many blockchain systems represent participants using cryptographic addresses rather than real-world identities, which can provide pseudonymity. However, transaction histories associated with addresses are typically visible to participants, which can enable linkage and tracing of activity under some conditions.
The emergence of privacy-focused cryptocurrencies such as Zcash and Monero has raised challenges for blockchain auditing, and some cryptocurrency exchanges have delisted or restricted privacy coins citing compliance concerns and regulatory pressure related to anti-money-laundering rules. As privacy-enhancing designs can reduce the information available for oversight, researchers and policymakers often describe a trade-off between privacy and auditability in digital payment systems.
Protected health information (PHI) is information about the provision of health care or payment for health care that is created or collected by a covered entity, and can be linked to a specific individual. This includes any part of a patient's medical record or payment history. PHI is sought out in datasets for de-identification before researchers share the dataset publicly. Researchers remove individually and identifiable PHI from a dataset to preserve privacy for research participants. There are many forms of PHI, with the most common being physical storage in the form of paper-based personal health records. Other types of PHI include electronic health records, wearable technology, and mobile applications. In recent years, there has been a growing number of concerns regarding the safety and privacy of PHI.
Catherine Tucker (born May 16, 1977) is the Sloan Distinguished Professor of Management at MIT Sloan, where she is also chair of the PhD program. She is known for her research into the consequences of digital data for electronic privacy, algorithmic bias, digital health, social media and online advertising. She is also a research associate at the NBER, cofounder of the Cryptoeconomics lab at MIT with Christian Catalini and coeditor at Quantitative Marketing Economics.
Figure 1: A54 How Blockchain Is Reshaping Blockchain Based Patient Electronic ... Official websites use .gov A .gov website belongs to an official government organization in the United States. Secure .gov websites use HTTPS A lock ( ) or https:// means you've safely connected to the .gov website. Share sensitive information only on official, secure websites.
Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Compared with traditional paper-based medical records, electronic health records (EHRs) are widely used because of their efficiency, security, and reducing data redundancy. However, EHRs still manifest poor interoperability and privacy issues are unresolved. As a distributed ledger protocol composed of encrypted blocks of data organized in chains, blockchain represents a potential tool to solve the shortcomings of EHRs in terms of interoperability and privacy. In this paper, we define EHRs and blockchain technology and introduce several classic schemes based on blockchain technology to strengthen EHR interoperability and privacy protection. We then review ongoing challenges in the areas of data management efficiency, fairness of access, and trust in the systems. In this commentary, we suggest ongoing research needs for health informatics, data sciences, and ethics to establish EHRs based on blockchain technology. Blockchain-based EHR schemes must address the potential inequality of healthcare resources, the huge carbon footprint of computational needs, and potential distrust of health providers and patients that may ensue with wider use of blockchain technology.
Figure 2: Blockchain Based Electronic Healthcare Record System (EHRS) — An ... An electronic health record (EHR) is the digital version of the patient’s health record which includes highly sensitive private information on history, diagnosis, and treatment. Other stored EHR data typically include appointments, billing and accounts, and laboratory tests. Indiana University, the Mayo Clinic, and Vanderbilt University were among the early academic EHR pioneers. In the 1970s, the federal government developed the country’s largest EHR system, VistA, for Veterans Affairs Health Care. By 1992, hardware had become cheaper and more powerful, and advancing computer technologies advanced the popularity of HER [ 1 ]. In 2004, EHR was incorporated into the Health Information Technology for Economic and Clinical Health Act (HITECH), reflecting the perceived need to convert medical records to EHR. New incentives and resources were available from the American Recovery and Reinvestment Act (ARRA or “ObamaCare”) beginning in 2009. The proportion of American hospitals using EHR systems had reached 95% by 2017 [ 2 ].
EHR reduces the inefficiency, insecurity, disorganization, data redundancy, and duplicate records problems associated with traditional paper-based medical records [ 3 ]. EHR is now regarded as an important part of the healthcare industry, though interoperability and privacy issues remain. Interoperability may be defined as the degree to which computer software and/or systems share, interdigitate, and/or make use of data between programs and devices made by different manufacturers and/or engineers. For EHR, interoperability refers to the patients’ information sharing among different healthcare software systems. There are two factors leading to interoperability of EHR: (1) heterogeneities in hardware and software; (2) heterogeneities in the structure, purpose, and deployment of her software systems [ 4 ]. Efficient exchange of health information can be impeded with the use of differeherEHR systems using varying hardware and software systems, often with different data structures and purposes deployed in diverse healthcare institutions. Although interoperability standards are proposed by several organizations such as the European Committee for Standardization (ECS), International Organization for Standardization (IOS), Health Level Seven (HL7), Digital Imaging and Communications in Medicine (DICOM), and Integrating the Healthcare Enterprise (IHE), these standards have limitations. First, these standards are not established for wider healthcare and computing research communities; thus, understanding and applying these standards are difficult for non-specialists. Second, none of these standards cover aspects of EHR in a comprehensive fashion. For example, some standards are only on content and structure of EHR, while the others are only on EHR data access [ 4 ].
Privacy represents a second unresolved issue within EHR system deployment. Data privacy and security are increasingly important, given the ease with which digital data can be shared or stolen (i.e., “hacked”). Governments have collaborated to introduce laws and regulations to protect data security, such as the 73rd General Data Protection Regulation by the European Union and the California Consumer Privacy Act in the United States [ 5 ]. Nevertheless, data breaches of EHR are taking place at an unprecedented scale. An estimated 173 million medical records were breached between October 2009 and April 2017, affecting over half of the US population [ 6 ]. A study investigated the causes of EHR data breaches found that theft (47.5%) and loss (27.4%) were the major sources, indicating an urgent need for stricter control and limited access to patients’ sensitive information [ 7 ].
Figure 3: Blockchain EHR Solution: Softlabs & SUNY Korea Case Study How can the interoperability and privacy issues of EHR be resolved? Blockchain technology is a potential tool. Blockchain is database storage using encrypted blocks of data organized in chains for access as a distributed ledger protocol [ 8 ]. This means that all parties (nodes) participating in, contributing to, or accessing data in the blockchain decide together which blocks are validly accessed by different users through the use of consensus algorithms. Only a block of data that has been verified to be valid and relevant can be added into the data chain. In most systems, all nodes can have a copy of the complete blockchain so that they know when and what data were accessed and by whom.
Blockchain has advantages of decentralization, data transparency, and privacy and security [ 9 ]. Decentralization means that all data in blocks are distributed throughout the blockchain network, rather than stored in a central storage location. In addition, whether a block can be added to the chain is decided by all nodes together instead of by one central node. Figure 1 shows details of blockchain with a sequence of blocks. Due to the decentralization of data management, each node can have a complete copy of the blockchain such that all data access is completely transparent to every node in the blockchain, making it impossible to furtively tamper with data without knowledge of the other nodes. Privacy and security of blockchain means encrypting the data stored in the block with hash functions, such as the SHA-256 encryption algorithm. Cryptographic hashes are powerful one-way functions, and it is exceedingly difficult to reverse the plain text from the hash value, protecting blockchain from any third-party interference.
Blockchain is now well applied in the cryptocurrency economic sector. Its features of decentralization, transparency, and security also provide a potentially viable solution to the problem of poor interoperability and data leakage in EHR. A number of studies have proposed blockchain-based solutions, some of which we discuss here; we further seek to explain commonly used jargon in this field. We filter studies to be discussed in the paper based on the following strategy. It is important to note that this paper is not a systematic review, but rather a discussion of blockchain-based EHR solutions based on blockchain technology. Our aim in this paper is to discuss the popular blockchain-based EHR studies of the last few years, and these studies should focus on addressing the issues of interoperability or privacy. We included suitable publications based on the following search criteria: original research articles, conference proceedings; in English exclusively; and published between 2016 and 2021. We excluded duplicate articles; reviews, opinions, or surveys; articles without available full text; and articles without full text in English; and papers with too few citations (less than 500 citations).
To enable interoperability, the MedRec framework employs a complex series of “smart contracts” on an Ethereum blockchain between patients and visitors, including the registrar contract, the patient-provider relationship contract, and a summary contract to protect patient privacy and standardize the form of EHR [ 10 ]. In the MedRec, the exchange of data for the same patient in different medical jurisdictions is simplified by updating viewership permissions on the relevant data pointers of the Ethereum blockchain. Data pointers are cryptographic hash pointing to the data block that contain the data storage information and the cryptographic hash of the data. Such a uniform and simple operation enhances interoperability between different EHR systems. In addition, MedRec only stores data ownership and viewership permissions (cryptographic hash of the record) instead of raw medical records in blocks; thus, the security of user privacy data is also guaranteed.
The Ancile framework also deploys smart contracts in an Ethereum-based blockchain for heightened access control [ 11 ]. However, unlike MedRec, the Ancile blockchain sends the actual query link information in a private transaction over the Hypertext Transfer Protocol Secure (HTTPS). Using proxy re-encryption enables patients to remove access permissions and store keys and small encrypted records directly on the blockchain instead of storing the data locally. Ancile uses the QuorumChain open source consensus that achieves user agreement for what data are added and who can access which data by voting on new blocks by ”voter nodes”, in contrast to the “proof of work “ consensus that relies on network participants (“miners”) to calculate valid hashes.
OmniPHR is a distributed peer-to-peer (P2P) network to integrate EHRs, including a variety of technologies such as blockchain, routing overlay (a technology to decentralize data, locate nodes, and manage their location of P2P network), and Chord algorithm (a distributed lookup protocol, address how to efficiently locate the node of P2P network which stores a desired data item) [ 12 ]. OmniPHR allows patients to have a unified view of their health records and allows healthcare providers to access up-to-date data regarding their patients even if their data are stored at different healthcare institutions.
The Healthcare Blockchain System framework is designed for remote monitoring of patients and access to their health records. It uses a private blockchain based on the Ethereum protocol to protect patients’ privacy [ 13 ]. At the same time, it maintains a secure record of who has initiated activities on the blockchain and provides details about every data transaction. Notifications are delivered to all involved parties to address security vulnerabilities in remote patient monitoring. Combined with blockchain, MPC (Secure Multi-Party Computing), Indicator-Centric Schema (ICS), and Healthcare Data Gateway (HGD) frameworks all guarantee patients’ rights to own, control, and share their own data easily and securely [ 14 ]. MeDShare employs smart contracts and an access control to track the behaviors of patients’ privacy data and detect the possible invasion of patients’ privacy [ 15 ]. More specifically, MeDShare closely monitors all actions performed on the data through smart contracts and keys attached to the contracts, so that if a malicious user tries to steal data privacy or tamper with reports generated by the smart contract, their actions will be exposed and access will be restricted or even revoked. In addition to the above solutions, there are many more studies using blockchain technology to store, track, and manage medical records [ 16 , 17 ]. Researchers propose an IoMT-based platform for EHR based on the blockchain [ 17 ]. The method combines IoMT (Internet of Medical Things) and blockchain to encrypt and save the user’s health information. First, multiple smart sensors collect the user’s health recording, and then encrypted health data will be stored in the nodes of the Ethereum blockchain, thus protecting the privacy of users.
Blockchain shows promise to help EHR unify its standards, increase interoperability, and protect patient privacy. However, there are challenges to overcome with blockchain data access and sharing technology. 2. System Architecture & Core Working Principles The first challenge is in blockchain inefficiency . Blockchain-based EHR necessitates complex computational operations, such as consensus mechanisms and digital signatures. These high-complexity operations impose an enormous computational burden on wireless nodes. Using Bitcoin cybercurrency as an example, the blockchain transaction processing mechanism is between 3.3 and 7 transactions per second, with the smallest transactions being 200–250 bytes [ 18 ]. Each transaction has to wait for about 10 min to be confirmed [ 19 ]. This is quite slow compared with the centralized systems used by banks that can deal with tens of thousands of transactions per second [ 19 ].
Similar to circumstances with cybercurrency data management, if a large number of patients and healthcare providers are added to the blockchain, the congestion caused by the huge computational burden can lead to query inefficiencies. Researchers simulated a private blockchain network consisting of one hospital node and 300 patient nodes [ 20 ]. The minimum mean propagation time (the average time it takes for a new block to reach most nodes in the network) was 1494.2 s and the minimum mean transaction time in the blockchain was 128.7 s. The results of these experiments pose the question whether an EHR system based on blockchain technology could meet the need for efficient and timely clinical, billing, or information sharing queries.
A second challenge concerns potential injustice and inequity in access and high energy demands . The blockchain uses incentive models to reward participation. In these models, transactions require network currency, such as Bitcoin or Ether. Currency can be earned by mining rewards or transaction fees. Network currencies have real value and they can be used for subsequent activities on the blockchain. In the MedRec, the rewards in the blockchain, the cryptocurrency Ether, will be given to care providers as a reward to incentivize them to participate in mining. The Ether blockchain protocol can be used for in-chain activities such as accepting viewing permissions and posting and updating contracts. Such an incentive is likely to cause medical inequities for lower resourced systems.
In a mechanism such as the proof-of-work (POW) blockchain system to obtain network currency, nodes (miners) in the blockchain need to constantly guess a random number (nonce) to obtain the power to generate the next block. If the hash value corresponding to the string obtained by combining the random number and the existing data of the blockchain meets the difficulty value requirements of the blockchain, the node can broadcast its calculation results, obtain the proof of work and the reward (network currency) of the corresponding block. Therefore, POW requires the care provider to perform repetitive calculations using specialized computer hardware until one gets the correct nonce. This energy-intense calculation has very high requirements for computing hardware and energy power [ 21 ], even requiring specialized computer hardware known as application-specific integrated circuits (ASICs) for the mining [ 22 ].
The high energy requirements for mining require massive additional computing capacity. Take the example of the Ether to be mined in MedRec; it takes an average of 7 MJ to generate just one US$, which is higher than the energy consumption of conventional mining copper and gold for the same value [ 23 ]. Healthcare providers with better computer hardware and more energy resources are likely to have more ownership in blockchain-based EHR systems. Given the dominance of the use of fossil fuels to generate electricity, the very high computational energy burden of blockchain will contribute to global greenhouse gas emissions and climate change. This system will reflect, and even amplify, the real-world inequalities in access to and use of valuable healthcare resources.
MedRec has proposed an alternative option, using the patient’s private data as a reward instead of Ether. This mode of reward risks injustice to patients. Without the protection from technologies such as differential privacy which is a cryptographic mechanism that can ensure almost consistent query results on adjacent data sets, the private information of patients remains at risk of leakage, even if the information is anonymous, especially for patients with rare diseases. Such an incentive model would be accompanied by further controversies about whether patients have the right to be informed about their own anonymized data, and whether this anonymization reward requires the patient’s consent.
One survey suggests that rare disease patients are willing to share their data with specific privacy requirements [ 23 ]. Blockchains such as Ancile blockchain bypass the risk of “currency” of patients’ privacy based on the QuorumChain consensus. However, this solution, which is based on a majority voting method to achieve consensus, is not secure enough at present. Malicious block-maker nodes can easily create inconsistencies and this protocol cannot ensure consensus in any realistic sense [ 24 ]. In addition, the QuorumChain consensus mechanism has not resolved how to fairly assign the roles of voter, maker, and observer to individual nodes. Hence, blockchain technology-based EMR sharing is not now equally accessible and affordable to all. Without improvements, the blockchain system has the potential to further amplify the uneven distribution of real-world healthcare resources.
A final challenge concerns trust issues for patients and healthcare workers alike. Even though smart contracts allow healthcare providers to trace requests for data, the lack of a regulatory mechanism may continue to raise concerns about inappropriate access and use of patient privacy information among healthcare providers and patients. The decentralized and transparent nature of blockchain makes data sharing safer and more secure, but also makes data regulation urgent. The lack of real-world regulation and lack of understanding of blockchain technology may lead to a crisis of trust between doctors and patients, and between different healthcare providers.
In conclusion, blockchain technology brings a new potential solution to the interoperability and privacy problems faced by EHR. It enables patients with one-stop shopping access to their medical histories and takes the burden of lifetime medical data stewardship from healthcare providers. However, existing blockchain-based EHR must address issues of efficiency, fairness, and trust. The integration of blockchain technology and EHR is not merely a technical issue that needs the attention of data scientists. For blockchain to reach its full potential towards EHR and other public health applications, data science, public health, medical, and nursing communities must address, through research and development, the inefficiencies and healthcare inequities potentially being exacerbated by blockchain-based EHRs, the carbon footprint on the environment due to high energy consumption created by blockchain-based EHRs, and the distrust of blockchain technology by healthcare providers and patients.
Conceptualization: Y.H.; writing—original draft: Y.H.; writing—review and editing: Y.Z. and S.H.V. All authors have read and agreed to the published version of the manuscript. This work was supported by the National Institutes of Health (grant numbers #UL1TR001863). Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations.
This section collects any data citations, data availability statements, or supplementary materials included in this article. Official websites use .gov A .gov website belongs to an official government organization in the United States. Secure .gov websites use HTTPS A lock ( ) or https:// means you've safely connected to the .gov website. Share sensitive information only on official, secure websites.
Reviewed by: Weizheng Wang, City University of Hong Kong, Hong Kong SAR, China; Saurabh Singh, Dongguk University Seoul, South Korea This article was submitted to Digital Public Health, a section of the journal Frontiers in Public Health distribution or reproduction in other forums is permitted, provided the original author(s) and the copyright owner(s) are credited and that the original publication in this journal is cited, in accordance with accepted academic practice. No use, distribution or reproduction is permitted which does not comply with these terms.
Healthcare information is essential for both service providers and patients. Further secure sharing and maintenance of Electronic Healthcare Records (EHR) are imperative. EHR systems in healthcare have traditionally relied on a centralized system (e.g., cloud) to exchange health data across healthcare stakeholders, which may expose private and sensitive patient information. EHR has struggled to meet the demands of several stakeholders and systems in terms of safety, isolation, and other regulatory constraints. Blockchain is a distributed, decentralized ledger technology that can provide secured, validated, and immutable data sharing facilities. Blockchain creates a distributed ledger system using techniques of cryptography (hashes) that are consistent and permit actions to be carried out in a distributed manner without needing a centralized authority. Data exploitation is difficult and evident in a blockchain network due to its immutability. We propose an architecture based on blockchain technology that authenticates the user identity using a Proof of Stake (POS) cryptography consensus mechanism and Secure Hash Algorithm (SHA256) to secure EHR sharing among different electronic healthcare systems. An Elliptic Curve Digital Signature Algorithm (ECDSA) is used to verify EHR sensors to assemble and transmit data to cloud infrastructure. Results indicate that the proposed solution performs exceptionally well when compared with existing solutions, which include Proof-Of-Work (POW), Secure Hash Algorithm (SHA-1), and Message Digest (MD5) in terms of power consumption, authenticity, and security of healthcare records.
Keywords: blockchain, cloud computing, electronic healthcare records, decentralized, Internet of Things Healthcare records require security and privacy protection during storage and sharing ( 1 – 7 ). Traditionally data sharing systems use centralized systems, which can present a major point of failure ( 8 ). Several blockchain variations have been presented since the launch of bitcoin about a decade ago ( 9 ). One of the sectors that are gaining traction with blockchain is the health industry ( 2 ). Figure 1 illustrates various applications of blockchain in the healthcare domain.
3. Software Implementation, Frameworks & Protocols Technological advancements such as the Internet of Things (IoT), Industrial IoT, and big data have aided the expansion and innovation of healthcare worldwide and the development of smart healthcare systems ( 10 , 11 ). Smart healthcare often incorporates EHR and cloud data that combine these EHR with mobile IoT by using IoT and communication devices for the development of medical and health services and the improvement of administrative services ( 12 – 14 ). Although the smart healthcare business has made rapid progress, there are still security issues ( 15 , 16 ).
Blockchain technology provides features such as decentralization, Peer-to-Peer (P2P) networking architecture, secrecy, tamper-evidence, and auditability, which can be effective for data sharing, transactions, and supply-chain management. The blend of blockchain and E-health can solve several challenges traditional healthcare solutions face like information sharing, data security, and privacy protection and improve user-centered smart healthcare solutions, as shown in Figure 2 .
Blockchain has gained the interest of entire business corporations because data saved on the blockchain is highly trustworthy and easily accessible through duplication. However, the research on the use of blockchain in the healthcare sector is insufficient ( 17 ). Most of the existing studies on the blockchain are related to the preservation of information system security, sustainable supply chain platforms in smart healthcare, blockchain-based healthcare monitoring systems, and tracking of operational environment on medical products via blockchain ( 18 ). The implications of blockchain in digital healthcare are difficult to explain as it encompasses all aspects of the sector. Blockchain is being promoted as a valuable tool for maintaining critical confidential data, especially in the healthcare, clinical science, health sciences, and insurance industries. Secrecy and security breaches in the healthcare profession are rising every year. When the data is available on distributed systems, lack of privacy and data hacking are the main threats to the security of healthcare records. Blockchain technology provides several measures to secure healthcare system records using cryptography tools and techniques. Blockchain helps secure sensitive medical information like drug prescriptions, pregnancy reports, and supply-chain data from cyber-attacks ( 19 ).
Based on previous research, security is the major problem to be solved. The development of advanced hardware and the rise of new technologies such as cloud computing, 5G, blockchain, and Artificial Intelligence (AI) create new values and improve the quality of life based on the existing services. Despite that, when technology advanced, then the threats and limitations also took place ( 20 ). AI technologies help to centralize power inside the hands of a small number of companies that can acquire and process enormous volumes of data, while blockchain can be used for secure transfer of EHR of each individual and encourage interoperability of data ( 21 ). As most of the data is handled by giant corporations, a private blockchain is not transparent enough, and its use is restricted. This study governs the conformation of healthcare records using blockchain technology. The framework used in this work is a blockchain-based smart healthcare system that uses the alliance chain method for transaction-level tasks to deliver data records to users or stakeholders for lowering communication cost, lowering computation cost, lowering risks, and increasing trust in blockchain technology ( 22 – 24 ).
We propose a framework that provides the benefits of blockchain for secure and efficient sharing and management of electronic health records using smart contracts. The intelligent contract, which is dependent on medical record management and is limited by the system, is a specific blockchain application in smart healthcare. We implement the framework using the SHA256 algorithm. We choose blockchain for interoperable EHR sharing, and storage ( 25 ).
Healthcare systems tend to be plagued by problems that frequently result in increased costs or declining health results (disease and death). Based on previous studies, the critical challenge to be solved is security. Blockchain technology has been promoted as a beneficial tool for managing data confidentiality, secrecy, and security, particularly in healthcare. Blockchain provides security to healthcare records using cryptography techniques and protects them from data breaching.
Therefore, this research is based on the secure, reliable, and authenticated sharing of EHR among different sources. We propose a blockchain-based framework to secure and authenticate the health sector records sharing system. The main objective of our work is to protect the EHR and secure the sharing and storage of EHR on the cloud using blockchain.
We use the POS consensus technique with the SHA256 algorithm to generate hash values to authenticate data integrity and the ECDSA technique for records verification. We use the sensor to collect the data and then store the sensor data on cloud computing-based storage to make data modifications impenetrable. We present a better healthcare security model for the user and the administration with its practical implementation using JavaScript class by enabling “nmp module,” which provides secure and authenticated records sharing capabilities.
The evaluation results show that the proposed framework provides high security while sharing and storing the EHR. The rest of the part is formed in an accompanying way. We discuss the literature review in Section 2. Then, we discuss the proposed methodology in Section 3. The practical implementation of proposed approaches, the detailed results, and the discussion are presented in Section 4. Finally, the paper is concluded in Section 5 with the future work.
The use of the blockchain for secure sharing of EHR and its other applications in healthcare systems has been illustrated in many previous studies. Several hospitals are involved in various proposed blockchain-based works ( 26 ). Secinaro et al. ( 27 ) described the usage and benefits of blockchain in the fields of auditing, accounting, and business management. Siyal et al. ( 28 ) introduced a Healthcare Data Gateway (HDG) framework, which is one of the famous examples of personal clinical data monitoring using a private blockchain. Li et al. ( 29 ) proposed cross enterprises and distributed ecosystem using edge computing and blockchain for secure sharing of knowledge and services for manufacturers. Pandey and Litoriya ( 25 ) presented the blockchain-based DASH application developed using the Decentralized applications of blockchain for secure and safe healthcare records sharing. Griggs et al. ( 30 ) developed a blockchain application based on Ethereum for safe monitoring of patients living far away using sensors. Siyal et al. ( 28 ) proposed the solution, Personal health record (PHR) for patients based on a public blockchain to easily access and share their health records as represented in Figure 3 .
Similarly, Chen et al. ( 31 ) proposed a blockchain-based cloud application to store and share the healthcare data of patients. In this framework, patients have access to share and manage their health records without the interference of any intermediary. Wang et al. ( 32 ) proposed a blockchain-based artificial intelligence system that helps the patients decide on treatment and doctors to examine the overall process of treatment. Shen et al. ( 33 ) proposed a framework of MedChain for secure sharing of healthcare data in sessions based on the techniques of digest blockchain and cryptography.
Jiang et al. ( 34 ) proposed BloCHIE based on an off-chain mechanism to maintain validity and privacy during sharing of electronic medical records and personal healthcare data. Pandey and Litoriya ( 25 ) proposed a framework based on attribute-based signature and MA-ABS to maintain privacy and security during the Electronic healthcare information exchange of patients. Shubbar et al. ( 35 ) proposed the DermoNet framework to assist and check the patients of dermatology. Abid et al. ( 36 ) proposed a blockchain-based distributed framework to provide secure patient examining facilities by storing patients' histories and prescriptions on the cloud. Zhang et al. ( 37 ) proposed a secure and efficient data storage and sharing scheme for blockchain-based mobile-edge computing using signature private key sharing technique to realize data and backups for cloud data storage.
Authors in ( 38 ) proposed an efficient, large-scale batch verification method using ECDSA. Authors in ( 39 ) proposed an authentication protocol for Wireless Sensor Medical Networks (WMSN) using blockchain and physically unclonable functions to protect the network from security and vulnerability attacks. Authors in ( 39 ) proposed a novel pairing-free certificateless scheme based on blockchain technology for the maintenance of data privacy and security of IIOT devices. Zhang et al. ( 40 ) provided a detailed survey on blockchain applications in various fields used for the security and protection of data.
Research on blockchain for healthcare management is increasing and still needs more attention and research. Blockchain applications have also been implemented in oncology, biomedical research to store DNA, insurance fraud detection of healthcare departments, anti-counterfeiting drug details to store medicines records, and pharmaceutical supply-chain management of healthcare medicines. From the related work, it is identified that blockchain has exceptional capabilities in the medical field. However, the difficulties must be applied to healthcare administration that can be beneficial to link different systems and improve the accuracy and safety of EHR ( 25 ). We analyze from the literature review that most of the research papers presented theoretical frameworks or models regarding EHR management using blockchain. However, technical details are missing, and existing proposed frameworks have limitations against data security, bandwidth, immaturity, and privacy of blockchain technology in healthcare because the algorithms used previously, such as POW, MD5, and SHA-1 is less efficient, costly, and consumes more computation power and communication cost.
We propose a secure peer-to-peer and decentralized framework for all healthcare providers and patients to maintain and manage demanding healthcare data. The proposed framework is based on a cryptographic POS consensus mechanism. The main reason to use blockchain is because of its property of immutability. Hyperledger builds confidential smart contracts among two parties using a POS consensus algorithm to exchange healthcare data, which improves data privacy by isolating transactions and consumes less energy and computation power. The design of the proposed framework is represented in Figure 4 . The framework provides secured sharing and storage of EHR among individuals and stakeholders.
The framework is decentralized, consisting of multiple nodes that can participate in the network to perform secure healthcare data sharing. The proposed framework is essentially safe from failure and data loss. The nodes in the proposed framework establish a ledger of the previous transaction using the blockchain technique of hashing, SHA256 cryptographic hash function, compute hash, and nodes need enough disk space to store hashes of all previous and next transactions. The secure hashing algorithm is implemented for decentralized blockchain ( 41 ).
For the computation of hash values as represented in Figure 5 , modular exponential technique were used ( 41 , 42 ). This approach calculates the exponent (e) of power nth, which is divided by the modulus of a non-negative integer (n), and the remainder of an integer base value (b). 4. Practical Deployment, Analysis & Case Studies The hash value is also generated by using the concept of Trapdoor One-way functions as described in Equation (1), which are defined between two sets like X and Y ( 43 ).
Where f is a trapdoor function hiding some secret information inside it, and the function of hashing is described in Equation (2). The Algorithm 1 converts the message into binary codes by using American Standard Code for Information Interchange (ASCII). Padding of zeros in the code gives the correct size of the block (512 bits), then the block is divided into 16 groups starting from M 0 – M 15 , h shows hash values, and w represents the words in each group of the block.
In the blockchain, the mining Algorithm 2 is used to merge new transactions B with previous transaction blocks P using block hash(H). This method helps to maintain a record of previous transactions, which is helpful for the validation and computation process of the transaction. Cloud mining is used to store the EHR data in the cloud. For verification of hashes, the elliptic curve technique is used, which is based on the Weierstrass Equation (3).
Block-chain uses ECDSA for the verification of ledger data entered by the users or participants. ECDSA is a cryptographic algorithm that ensures that data is shared among authorized nodes only because it depends on hash value. To add the previous block's hash with the upcoming block's hash, the following Equation (4) has been used. The terms used in the equations show hash blocks containing secret information.
There are five separate nodes participating in consensus in the network, including visitors, coordinators, agents, administrators, and the contributor nodes. The visitor nodes request the required services from the network. Agent nodes manage client node requests and provide them authentication services before approval. Coordinator nodes confirm the approval and acknowledge or refuse the request for further processing. Administrator nodes obtain authenticated requests from several coordinator nodes, manage transactions into frames, and transmit the freshly produced frames to neighbor coordinators and contributors, who circulate them further throughout the network. Using this approach, the updated state is initiated among the entire network.
The block or frame comprises a block header and a transaction. The timestamp, current block hash, preceding block hash, and Merkle root are included in the block header. Merkle root calculates the current and previous blocks' hash value because it is more efficient and secure and takes less space. Hence this process form chain of blocks. Every contributing network device must give a regional, updated blockchain version according to a framework.The transactions are tamper-resistant as a result of this setup. When an attacker manipulates a transaction in his favor, the Merkle root, which represents all of the candidate transaction's hash, is altered, and the hash for that block is altered as well. As the targeted chunk is likewise connected to its next chain using a hash, there will be a point of conflict, and the system will not accept this alteration. As a result, the entire network contributes to assuring the confidentiality and reliability of the transactions. An Authentication and Authorization Agency (AAA) identifies every individual connected to the network. AAA guarantees that only certified entities carry out their responsibilities by the allowed access ( 25 ). The following section outlines a plan for the safe and secure storage of EHR.
We presume that the healthcare specifics include a variety of hospitals, surgeons, and other personnel records. Special recognition keys are used to identify healthcare specifics, including hospitals, doctors, personnel, and patients. Medications, diagnostic reports, bills, insurance policies, and birth and death records are examples of healthcare transactions made and shared regularly. A block is 30 KB in size, with a maximum of 15 transactions. There is also a 6-min time limit, and this means that even if a building block only includes one transaction, it will be completed in the blockchain after that period. Transactions might no longer wait for an unknown time to complete. Those who are permitted can initiate or investigate transactions on the network, which is closed. Patients' data can be kept private by eliminating personal details, such as names and contact information, or by employing an internal investigation procedure to ensure that the rationale for utilizing patient data is valid and authentic ( 44 ). A hash of the patient ID issued by AAA is used to incorporate privacy into the network. Only this hash is used to record and recognize every content on the network. As a result of hashing's one-way nature, the patient's details cannot be tracked by glancing at E-documents. This information must be stored in the distributed ledger once a document is constructed or transferred. A visitor notifies the agents of such operations, and each agent node validates the transaction's source and rights. Steps 1 through 4 describe the reliability, authenticity, and validation of transactions by ensuring that the message has not been changed during passing from one block to another.
Step 1: Assume that an ECG operator is doing an ECG of a patient having ID 0001. Before submitting this transaction to the agent nodes, the visitor node (ECG operator) would sign it with his private key. The agent nodes verify the visitor's validity and authorizations before approving or rejecting the proposal with an “A” or “R” indicator. Agent nodes submit suggestions to coordinators for approval or rejection.
Step 2: The coordinators make sure that the new visitor's proposal gets the necessary approvals and permissions in accordance with the acceptance or sanctioning policy. If a visitor proposal violates the policy, coordinators do not forward transactions to administrators. The coordinators also do the additional task of using smart contracts to validate the transactions. A smart contract, for instance, would examine if this transaction is valid “ECG film made for patient Id 1bcd9cefbc5ef8afn5ad4d4f f74b3ade at /hospital/report-store/ECG/1bcd9cefbc5ef8afn5ad4d4ff 74b3ade-05-04-2021-1600.ecg” is confirmed by looking it up in the ECG database: look it up (“/hospital/report-store/ECG /1bcd9cefbc5ef8afn5ad4d4ff74b3ade-05-04-2021-1600.ecg”). The action is confirmed if the search results in a declaration.
Patients and healthcare providers can also sign smart contracts with jointly agreed-upon clauses and conditions. Step 3: The administrator then receives the transactions from coordinators, orders them according to their logs, and uses the consensus mechanism to produce a new block of transactions. Rather than owning the distributed ledger, administrators regularly hold a backup of the last block hash.
Step 4: Administrators then transmit the freshly devised frame or block of the transaction to each of the coordinating and contributing nodes, which authenticate the transactions within the block once more before executing and updating their ledgers. This secondary validation ensures that a transaction has not been invalidated in the interim. The suggested framework architecture incorporates several unique characteristics that make it robust, durable, business-oriented, accessible, and private: Only the contributing nodes are responsible for maintaining the public ledger in the proposed structure, while coordinators may also preserve ledger copies. Administrators only keep a copy of the most recent block hash, not the entire ledger. This allows for the use of a basic organizing service to serve many organizations or intermediary organizing services to serve numerous organizations without compromising the confidentiality and privacy of previous data.
The agent nodes perform the duties of a custodian by determining whether a transaction is approved and originated from a reliable source—this aids in the early application of business logic by preventing incorrect transactions from progressing through the system. The use of hash values for collecting and processing health information enables privacy while also allowing the system to be transparent. For example, transactions are public to everyone who has a copy of the ledger, but nobody can determine the patient by glancing at the transaction.
In the proposed approach, a contributor node may be a member of another hierarchical organizational system and transmit the new blocks to other neighbors. As a result, the system is robust and fair from the start. High reliability is provided through distributed consensus for administrators. For instance, a one-node reliable system can be developed using four nodes.
Early identification of finite-state anomalies by implementing smart contracts overall coordinating nodes prevents non-deterministic transactions from propagating farther into the organizing service. Writing regulations that restrict the number of agents and coordinators who can approve and validate transactions could help to speed up the process. Concurrently, a more significant number of requests can be accepted from visitors and forwarded to the administration panel. Conventional systems store patient demographics, allergies, medications, and large documents such as MRIs, X-rays, and endoscopic results off the chain. Authorized individuals can access them via secure links.
The proposed solution is tested on 12 Windows Ten (10) 64-bit Desktops having 4 Gb Of ram and a Hp 2.4-GHz CPU. A crypto module in node.js computes the 256-bit SHA-2 hash code. 64-bit hexadecimal digits are used to generate the 256-bits hash value. Here, the block is created with an introductory JavaScript class consisting of 12 nodes divided into two groups of three nodes identified as coordinating and authoritative nodes correspondingly. One node within the coordinating set keeps a local copy of the master ledger. The responsibility of ordering services has been given to five of the remaining nodes for managing the public ledger, and two nodes operate as contributors and one as a visitor. JavaScript has been used on some ports to test the validation and authentication, e.g., authoritative node listening to some messages on port 7777, and node.js implementation is represented as shown in Algorithm 3 .
5. Performance Evaluation & Extended Technical Observations We use transaction throughput and computation time as evaluation metric to evaluate the performance of proposed framework.The throughput is the rate at which valid transactions are committed by the network in specified period of time. We performed analysis by performing transactions using proposed methodology on various nodes. We analyzed the throughput time spending on communication and completing a transaction using the proposed framework.
The Algorithms 3 , 4 show the source code used for the implementation process of transaction commitment and its status of approval or refusal during the information exchange between several nodes. To analyze the performance, we perform an analysis based on the throughput of various participating nodes' transactions for the proposed blockchain framework. Then we analyzed the implementation of network throughput on different configuration nodes, which results are explained in Table 1 .
In Table 1 , the same values show the results of constant parameter for every configuration node means secure sharing without any alteration in data, and different values show the results of changed configuration parameter values which indicates that if data has been altered during the interim process, then it gives the changed output every time. The amount of transactions every 6 min is used to determine the throughput.
The Graphs in Figures 6 , 7 show the results of configuration nodes, whose implementation details are given in Table 1 . Most ordering sites significantly impact system throughput, whereas authoritative contributors and coordinators have a minor impact due to network latency. We also discovered that up to 17 operations could be completed with the lowest load. We also compare the performance of the proposed framework with existing approaches and found better performance in terms of throughput, computation cost, communication cost and secure storage and sharing.
We proposed a translucent, secure, and distributed framework for secure healthcare data exchange using blockchain technology. Blockchain provides robust, traceable, and unchangeable data sharing and storage facilities relative to traditional healthcare systems. We proposed a blockchain-based framework to store patients' confidential details using patients' hash IDs in distributed hyperledger using POS consensus with crypto SHA256. For the verification of records and secure transactions, ECDSA has been used. We used the nmp module of the JavaScript class to implement the proposed framework.
Only recognized users can perform transactions and get stored data through this framework. Due to the storage issues on the blockchain, we stored the data on the conventional server using sensors and transmitted the sensor data into a cloud computing framework. As the transaction backups are stored on various nodes in the network, if any node is found malicious, it will not harm the network's data. We compared the results of the proposed solution with existing frameworks and found that the proposed solution performs better. We can conclude that the SHA256 and ECDSA can provide security, integrity, and authenticity in various medical data sharing and storing mechanisms. The framework has some limitations related to the storage capacity. In the future, this technique can be made more robust with the integration of federated learning to achieve extensive protection ( 45 , 46 ). This work can also be adapted for a trustable courier system and monitoring corruption intolerance.
The original contributions presented in the study are included in the article/supplementary material, further inquiries can be directed to the corresponding author/s. AAm and MR: conceptualization. YZ: data curation. AAm: formal analysis, investigation, and methodology. SK: funding acquisition. SK and MR: project administration. AAm and AAl: resources. CM and MR: software, validation, and writing—review and editing. AAm and SK: supervision. YZ and AAl: visualization. All authors contributed to the article and approved the submitted version.
This research was supported in part by Basic Science Research Program through the National Research Foundation of Korea (NRF) funded by the Ministry of Education (NRF-2021R1A6A1A03039493) and in part by the NRF grant funded by the Korea Government (MSIT) (NRF-2022R1A2C1004401). The authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
All claims expressed in this article are solely those of the authors and do not necessarily represent those of their affiliated organizations, or those of the publisher, the editors and the reviewers. Any product that may be evaluated in this article, or claim that may be made by its manufacturer, is not guaranteed or endorsed by the publisher. This section collects any data citations, data availability statements, or supplementary materials included in this article.
The original contributions presented in the study are included in the article/supplementary material, further inquiries can be directed to the corresponding author/s. Thank you for visiting nature.com. You are using a browser version with limited support for CSS. To obtain the best experience, we recommend you use a more up to date browser (or turn off compatibility mode in Internet Explorer). In the meantime, to ensure continued support, we are displaying the site without styles and JavaScript.
Current Electronic Health Record (EHR) systems exhibit several critical drawbacks, including significant vulnerabilities in security, privacy, and scalability. Traditional centralized databases are highly susceptible to cyber attacks, data breaches, and unauthorized access, posing severe risks to the confidentiality and integrity of sensitive patient information. In addition, these systems often face interoperability issues, which hinder seamless information sharing and access among healthcare providers. The absence of a unified and secure framework exacerbates these problems, leading to operational inefficiencies and increased administrative costs in the management of health records. This study introduces an innovative framework designed to overcome these challenges by integrating blockchain technology with the InterPlanetary File System (IPFS). The proposed EHRChain solution leverages attribute-based encryption to provide fine-grained access control, ensuring that only authorized users can retrieve and decrypt medical records. The IPFS framework eliminates single points of failure by storing encrypted data in a decentralized fashion, thus increasing the resilience of the system to cyber attacks. Incorporating blockchain technology ensures the immutability and traceability of medical data, significantly reducing the risks of data tampering. Performance evaluations using real data set simulation demonstrate the efficiency and feasibility of our framework, highlighting its potential to revolutionize the handling of electronic medical records. This study not only underscores the advantages of integrating blockchain with EHR systems but also presents a scalable and secure solution tailored to meet the demands of modern healthcare infrastructures. Our approach promises to improve data security, improve interoperability, and reduce operational inefficiencies, leading to a new standard in electronic health records.
A privacy preserving medical data management framework using blockchain enabled encrypted role based access control Secure electronic health record access control via blockchain, dual-attribute encryption, and large language model-based attribute extraction Efficient design of blockchain-based electronic health record systems with federated learning, off-chain storage, and zk-rollup parallelism for minimizing transaction costs With the emergence of Internet of Medical Things (IoMT) 1 , the volume of medical data generated daily has increased dramatically. As the healthcare sector transitions from traditional paper-based charts to Electronic Health Record (EHR), various solutions have been implemented to manage these records efficiently, aiming to enhance patient safety by preventing errors and increasing information accessibility. EHR 2 , not only serve as legal evidence and tools for predicting and preventing infectious diseases but also enable physicians to reflect on and share treatment experiences with patients in real-time. By 2025 3 , it is projected that electronic storage will encompass at least 15% of patient medical records, marking a 110% increase from 2018 levels.
Typically, medical institutions rely on third-party servers, like cloud servers, to manage encrypted data, which helps reduce computational costs and save space while facilitating efficient data retrieval 4 . However, the sharing of electronic medical data among medical facilities, though beneficial for providing immediate feedback on patient responses to treatment, raises serious privacy concerns. Once shared, this data is susceptible to illegal misuse, which could compromise patient privacy.
Ensuring proper control over access to patient medical records is of paramount importance, with attribute-based encryption (ABE) emerging as a key technique for enforcing access control 5 . According to reports from the Health Insurance Portability and Accountability Act (HIPAA) 6 and the Journal of Healthcare Security 7 , approximately 81% of healthcare records of Americans have been compromised between 2009 and 2023. In 2023 alone, data breach costs for healthcare organizations reached a record $7, 13 million, a 10% increase over the previous year. These security and privacy breaches present substantial barriers to the effective management and sharing of health records. Thus, there is an urgent need for innovative solutions that ensure the secure and controlled sharing of sensitive medical information among different participants without risking data disclosure or manipulation. An efficient data access mechanism is essential to ensure data security and restrict access to authorized users only. Patients should have the autonomy to decide who can access their medical information 8 .
In recent years, a variety of healthcare applications have been developed that leverage blockchain technology. Azaria et al. introduced MedRec, the first functional shared Electronic Health Record (EHR) system that utilizes blockchain, although it raises concerns related to confidentiality and privacy 9 . FHIRChain, a system similar to MedRec, uses cryptographic techniques to encrypt and securely share data among clinicians 10 . Another framework proposed by Dubovitskaya et al.
shares similarities with MedRec, allowing patients to share their health records but lacking a mechanism for consent revocation management 11 . The Centralized Electronic Health Record systems exhibit significant architectural limitations, as demonstrated in Fig. 1 . The dependence on opaque third-party storage solutions creates inherent vulnerabilities in data governance, with users lacking visibility into data location and access patterns. These security concerns, visualized in Fig. 1 , include risks of false data injection and system compromises that undermine healthcare data integrity.
Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/Blockchain%20privacy • https://en.wikipedia.org/wiki/Protected%20health%20information • https://en.wikipedia.org/wiki/Catherine%20Tucker • https://pmc.ncbi.nlm.nih.gov/articles/PMC9739765/ • https://pmc.ncbi.nlm.nih.gov/articles/PMC9343689/ • https://www.nature.com/articles/s41598-025-17875-5
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.

Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Blockchain Based Electronic Health Record Privacy System.
[*] Metasploit Scan Running on Target Subnet for Blockchain Based Electronic Health Record Privacy System... [✓] SafeBreach / AttackIQ Continuous Exposure Agent Triggered ──────────────────────────────────────────────────────────────────────── [11:48:02.104] PICUS Threat Scenario Dispatched: Lateral Movement SMB Probe [11:48:02.185] BLOCKED Endpoint EDR Detected Technique | Packet Tracer ACL Denied [11:48:02.240] CYMULATE Prevention Rate = 96.8% | SIEM Latency = 38 ms [11:48:02.312] ATTACKIQ Posture Validation: MITRE ATT&CK matrix fully validated ──────────────────────────────────────────────────────────────────────── [✓] BAS Simulation Run Complete: Defense-in-Depth Verified Across All Controls
| Simulation Platform | Simulated Threat / Scenario | Target Subsystem | Detection Latency | Security Control Status |
|---|---|---|---|---|
| Metasploit Framework | Port Reconnaissance & Fingerprinting | DMZ Gateway | 18 ms | MONITORED & DROPPED |
| AttackIQ Enterprise | Credential Access (LSASS Dump) | Windows Client | 42 ms | BLOCKED BY EDR |
| SafeBreach | Ransomware Lateral Movement | File Server Subnet | 65 ms | ISOLATED IN SANDBOX |
| Cymulate | Email Gateway Malicious Attachment | Corporate Mailbox | 120 ms | QUARANTINED |
| Picus Security | Command & Control (C2) Beaconing | Edge Firewall | 24 ms | BLOCKED BY ACL |