Complete Technical Paper Content — Hipaa Data Privacy Auditing Tool
Overview & System Context
Hipaa Data Privacy Auditing Tool: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~9508 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background Information privacy, also known as data privacy or data protection, is the relationship between the collection and dissemination of data, technology, the public expectation of privacy, contextual information norms, and the legal and political issues surrounding them. Various types of personal information often come under privacy concerns. Privacy concerns exist wherever personally identifiable information or other sensitive information is collected, stored, used, and finally destroyed or deleted – in digital form or otherwise. Improper or non-existent disclosure control can be the root cause for privacy issues.
Informed consent mechanisms including privacy policies and dynamic consent are important in communicating to data subjects the different uses of their personally identifiable information. Healthcare records Criminal justice investigations and proceedings Financial institutions and transactions Biological traits, such as genetic material Residence and geographic records Privacy breach Location-based service and geolocation Web surfing behavior or user preferences using persistent cookies Academic research Information about a person's financial transactions, including the amount of assets, positions held in stocks or funds, outstanding debts, and purchases can be sensitive. If criminals gain access to information such as a person's accounts or credit card numbers, that person could become the victim of fraud or identity theft. Information about a person's purchases can reveal a great deal about that person's history, such as places they have visited, whom they have contact with, products they have used, their activities and habits, or medications they have used. In some cases, corporations may use this information to target individuals with marketing customized towards those individual's personal preferences, which that person may or may not approve.
The ability to control the information one reveals about oneself over the internet and who can access that information has become a growing concern. These concerns include whether email can be stored or read by third parties without consent or whether third parties can continue to track the websites that someone visited. Another concern is whether websites one visits can collect, store, and possibly share personally identifiable information about users. The advent of various search engines and the use of data mining created a capability for data about individuals to be collected and combined from a wide variety of sources very easily. AI facilitated creating inferential information about individuals and groups based on such enormous amounts of collected data, transforming the information economy. The FTC has provided a set of guidelines that represent widely accepted concepts concerning fair information practices in an electronic marketplace, called the Fair Information Practice Principles. But these have been critiqued for their insufficiency in the context of AI-enabled inferential information.
Figure 1: Compliance Software to Prepare for HIPAA Audits | Carbide On the internet many users give away a lot of information about themselves: unencrypted emails can be read by the administrators of an e-mail server if the connection is not encrypted (no TLS), and also the internet service provider and other parties sniffing the network traffic of that connection are able to know the contents. The same applies to any kind of traffic generated on the Internet, including web browsing, instant messaging, and others. In order not to give away too much personal information, emails can be encrypted and browsing of webpages as well as other online activities can be done anonymously via anonymizers, or by open source distributed anonymizers, so-called mix networks. Nym and I2P are examples of well-known mix nets. With social media and e-commerce sites being used more frequently, there are more potential openings for stealing consumer's data. Companies can see which types of products consumers like to purchase and can use targeted ads to try to make people purchase more items thinking that this is what they will want to purchase.
However, sometimes this type of data is used without explicit consent. Users are unaware of all of the personal information that is collected about them. Cookies track browsing data and location settings show where a person is based out of, and can show shops or products that are physically located near someone. These combined that be a big safety and privacy issue for users if their data is not being stored safely. With laws like the California Consumer Privacy Act (CCPA), people's data can be protected and they asked for explicit consent before using said data. Globally, many nations are trying to implement similar clauses to protect consumers. Email is not the only internet content with privacy concerns. In an age where increasing amounts of information are online, social networking sites pose additional privacy challenges. People may be tagged in photos or have valuable information exposed about themselves either by choice or unexpectedly by others, referred to as participatory surveillance. Data about location can also be accidentally published, for example, when someone posts a picture with a store as a background. Caution should be exercised when posting information online. Social networks vary in what they allow users to make private and what remains publicly accessible. Without strong security settings in place and careful attention to what remains public, a person can be profiled by searching for and collecting disparate pieces of information, leading to cases of cyberstalking or reputation damage. Cookies are used on websites so that users may allow the website to retrieve some information from the user's internet, but they usually do not mention what the data being retrieved is. In 2018, the General Data Protection Regulation (GDPR) passed a regulation that forces websites to visibly disclose to consumers their information privacy practices, referred to as cookie notices. This was issued to give consumers the choice of what information about their behavior they consent to letting websites track; however, its effectiveness is controversial. Some websites may engage in deceptive practices such as placing cookie notices in places on the page that are not visible or only giving consumers notice that their information is being tracked but not allowing them to change their privacy settings. Apps like Instagram and Facebook collect user data for a personalized app experience; however, they track user activity on other apps, which jeopardizes users' privacy and data. By controlling how visible these cookie notices are, companies can discreetly collect data, giving them more power over consumers.
People may not wish for their medical records to be revealed to others due to the confidentiality and sensitivity of what the information could reveal about their health. For example, they might be concerned that it might affect their insurance coverage or employment. Or, it may be because they would not wish for others to know about any medical or psychological conditions or treatments that would bring embarrassment upon themselves. Revealing medical data could also reveal other details about one's personal life. There are three major categories of medical privacy: informational (the degree of control over personal information), physical (the degree of physical inaccessibility to others), and psychological (the extent to which the doctor respects patients' cultural beliefs, inner thoughts, values, feelings, and religious practices and allows them to make personal decisions). Physicians and psychiatrists in many cultures and countries have standards for doctor–patient relationships, which include maintaining confidentiality. In some cases, the physician–patient privilege is legally protected. These practices are in place to protect the dignity of patients, and to ensure that patients feel free to reveal complete and accurate information required for them to receive the correct treatment. To view the United States' laws on governing privacy of private health information, see HIPAA and the HITECH Act. The Australian law is the Privacy Act 1988 Australia as well as state-based health records legislation.
Political privacy has been a concern since voting systems emerged in ancient times. The secret ballot is the simplest and most widespread measure to ensure that political views are not known to anyone other than the voters themselves—it is nearly universal in modern democracy and considered to be a basic right of citizenship. In fact, even where other rights of privacy do not exist, this type of privacy very often does. There are several forms of voting fraud or privacy violations possible with the use of digital voting machines.
The legal protection of the right to privacy in general – and of data privacy in particular – varies greatly around the world. Laws and regulations related to Privacy and Data Protection are constantly changing; it is seen as important to keep abreast of any changes in the law and to continually reassess compliance with data privacy and security regulations. Figure 2: 17 HIPAA Compliance Software Solutions to Know in 2026 Data protection laws across the globe aim to secure personal information and safeguard individual privacy in a digital era. The European Union's General Data Protection Regulation (GDPR) sets a high benchmark, emphasizing consent, transparency, and robust accountability by imposing strict penalties. Many countries adopt similar principles, mandating that organizations implement effective security measures, respect user rights, and notify breaches. In regions such as North America, Asia, and Oceania, data protection frameworks vary from sector-specific regulations to comprehensive legislation. Globally, these laws balance innovation with privacy, ensuring that personal data is appropriately accessible, managed ethically while mitigating misuse and cyber threats.
The United States Department of Commerce created the International Safe Harbor Privacy Principles certification program in response to the 1995 Directive on Data Protection (Directive 95/46/EC) of the European Commission. Both the United States and the European Union officially state that they are committed to upholding information privacy of individuals, but the former has caused friction between the two by failing to meet the standards of the EU's stricter laws on personal data. The negotiation of the Safe Harbor program was, in part, to address this long-running issue. Directive 95/46/EC declares in Chapter IV Article 25 that personal data may only be transferred from the countries in the European Economic Area to countries which provide adequate privacy protection. Historically, establishing adequacy required the creation of national laws broadly equivalent to those implemented by Directive 95/46/EU. Although there are exceptions to this blanket prohibition – for example where the disclosure to a country outside the EEA is made with the consent of the relevant individual (Article 26(1)(a)) – they are limited in practical scope. As a result, Article 25 created a legal risk to organizations which transfer personal data from Europe to the United States. The program regulates the exchange of passenger name record information between the EU and the US. According to the EU directive, personal data may only be transferred to third countries if that country provides an adequate level of protection. Some exceptions to this rule are provided, for instance when the controller themself can guarantee that the recipient will comply with the data protection rules. The European Commission has set up the "Working party on the Protection of Individuals with regard to the Processing of Personal Data," commonly known as the "Article 29 Working Party". The Working Party gives advice about the level of protection in the European Union and third countries. The Working Party negotiated with U.S. representatives about the protection of personal data, the Safe Harbor Principles were the result. Notwithstanding that approval, the self-assessment approach of the Safe Harbor remains controversial with a number of European privacy regulators and commentators. The Safe Harbor program addresses this issue in the following way: rather than a blanket law imposed on all organizations in the United States, a voluntary program is enforced by the Federal Trade Commission. U.S. organizations which register with this program, having self-assessed their compliance with a number of standards, are "deemed adequate" for the purposes of Article 25. Personal information can be sent to such organizations from the EEA without the sender being in breach of Article 25 or its EU national equivalents. The Safe Harbor was approved as providing adequate protection for personal data, for the purposes of Article 25(6), by the European Commission on 26 July 2000. Under the Safe Harbor, adoptee organizations need to carefully consider their compliance with the onward transfer obligations, where personal data originating in the EU is transferred to the US Safe Harbor, and then onward to a third country. The alternative compliance approach of "binding corporate rules", recommended by many EU privacy regulators, resolves this issue. In addition, any dispute arising in relation to the transfer of HR data to the US Safe Harbor must be heard by a panel of EU privacy regulators. In July 2007, a new, controversial, Passenger Name Record agreement between the US and the EU was made. A short time afterwards, the Bush administration gave exemption for the Department of Homeland Security, for the Arrival and Departure Information System (ADIS) and for the Automated Target System from the 1974 Privacy Act. In February 2008, Jonathan Faull, the head of the EU's Commission of Home Affairs, complained about the US bilateral policy concerning PNR. The US had signed in February 2008 a memorandum of understanding (MOU) with the Czech Republic in exchange of a visa waiver scheme, without concerting before with Brussels.
The tensions between Washington and Brussels are mainly caused by a lesser level of data protection in the US, especially since foreigners do not benefit from the US Privacy Act of 1974. Other countries approached for bilateral MOU included the United Kingdom, Estonia, Germany and Greece. There are techniques to improve privacy, privacy-enhancing technologies, and privacy software tools. People building and updating systems can use privacy by design and privacy engineering strategies and techniques. For example, by converting data into a non-readable format, encryption prevents unauthorized access.
Koopman, Colin (2019). How We Became Our Data: A Genealogy of the Informational Person. Chicago: University of Chicago Figure 3: HIPAA-Compliant Observability and Security for Health Information ... A privacy policy is a statement or legal document (in privacy law) that discloses some or all of the ways a party gathers, uses, discloses, and manages a customer or client's data, while a privacy notice tells clients or data subjects what data is held by an organisation and how that data will be handled. Personal information can be anything that can be used to identify an individual, not limited to the person's name, address, date of birth, marital status, contact information, ID issue, and expiry date, financial records, credit information, medical history, where one travels, and intentions to acquire goods and services. In the case of a business, it is often a statement that declares a party's policy on how it collects, stores, and releases personal information it collects. It informs the client what specific information is collected, and whether it is kept confidential, shared with partners, or sold to other firms or enterprises. Privacy policies typically represent a broader, more generalized treatment, as opposed to data use statements, which tend to be more detailed and specific. The exact contents of a privacy policy will depend upon the applicable law and may need to address requirements across geographical boundaries and legal jurisdictions. Most countries have their own legislation and guidelines of who is covered, what information can be collected, and what it can be used for. In general, data protection laws in Europe cover the private sector as well as the public sector.
Their privacy laws apply not only to government operations but also to private enterprises and commercial transactions. There are significant differences between the EU data protection and US data privacy laws. These standards must be met not only by businesses operating in the EU but also by any organization that transfers personal information collected concerning citizens of the EU. In 2001 the United States Department of Commerce worked to ensure legal compliance for US organizations under an opt-in Safe Harbor Program. The FTC has approved eTRUST to certify streamlined compliance with the US-EU Safe Harbor.
While no generally applicable law exists, some federal laws govern privacy policies in specific circumstances, such as: The Children's Online Privacy Protection Act (COPPA) affects websites that knowingly collect information about or targeted at children under the age of 13. Any such websites must post a privacy policy and adhere to enumerated information-sharing restrictions COPPA includes a "safe harbor" provision to promote Industry self-regulation. The Gramm-Leach-Bliley Act requires institutions "significantly engaged" in financial activities give "clear, conspicuous, and accurate statements" of their information-sharing practices. The Act also restricts use and sharing of financial information. The Health Insurance Portability and Accountability Act (HIPAA) privacy rules requires notice in writing of the privacy practices of health care services, and this requirement also applies if the health service is electronic. The California Consumer Privacy Act (CCPA) gives consumers more control over the personal information that businesses collect about them and the CCPA regulations provide guidance on how to implement the law. The California Privacy Rights Act of 2020 (CPRA) expands the privacy and information security obligations of most employers doing business in California. Some states have implemented more stringent regulations for privacy policies. The California Online Privacy Protection Act of 2003 – Business and Professions Code sections 22575-22579 requires "any commercial websites or online services that collect personal information on California residents through a web site to conspicuously post a privacy policy on the site". Both Nebraska and Pennsylvania have laws treating misleading statements in privacy policies published on websites as deceptive or fraudulent business practices.
The right to privacy is a highly developed area of law in Europe. All the member states of the European Union (EU) are also signatories of the European Convention on Human Rights (ECHR). Article 8 of the ECHR provides a right to respect for one's "private and family life, his home and his correspondence", subject to certain restrictions. The European Court of Human Rights has given this article a very broad interpretation in its jurisprudence. In 1980, in an effort to create a comprehensive data protection system throughout Europe, the Organization for Economic Co-operation and Development (OECD) issued its "Recommendations of the Council Concerning Guidelines Governing the Protection of Privacy and Trans-Border Flows of Personal Data". The seven principles governing the OECD’s recommendations for protection of personal data were: Notice—data subjects should be given notice when their data is being collected; Purpose—data should only be used for the purpose stated and not for any other purposes; Consent—data should not be disclosed without the data subject's consent; Security—collected data should be kept secure from any potential abuses; Disclosure—data subjects should be informed as to who is collecting their data; Access—data subjects should be allowed to access their data and make corrections to any inaccurate data; and Accountability—data subjects should have a method available to them to hold data collectors accountable for not following the above principles. The OECD guidelines, however, were nonbinding, and data privacy laws still varied widely across Europe. The US, while endorsing the OECD’s recommendations, did nothing to implement them within the United States. However, all seven principles were incorporated into the EU Directive. In 1995, the EU adopted the Data Protection Directive, which regulates the processing of personal data within the EU. There were significant differences between the EU data protection and equivalent U.S. data privacy laws. These standards must be met not only by businesses operating in the EU but also by any organization that transfers personal information collected concerning a citizen of the EU.
In 2001 the United States Department of Commerce worked to ensure legal compliance for US organizations under an opt-in Safe Harbor Program. The FTC has approved a number of US providers to certify compliance with the US-EU Safe Harbor. Since 2010 Safe Harbor is criticised, especially by German publicly appointed privacy protectors, because the FTC's will to assert the defined rules had not been implemented in a proper manner even after revealing disharmonies. From 25 May 2018, the Data Protection Directive was superseded by the General Data Protection Regulation (GDPR), which harmonizes privacy rules across all EU member states. GDPR imposes more stringent rules on the collection of personal information belonging to EU data subjects, including a requirement for privacy policies to be more concise, clearly-worded, and transparent in their disclosure of any collection, processing, storage, or transfer of personally identifiable information. Data controllers must also provide the opportunity for their data to be made portable in a common format, and for it to be erased under certain circumstances.
The Privacy Act 1988 provides the legal framework for privacy in Australia. It includes a number of national privacy principles. There are thirteen privacy principles under the Privacy Act. It oversees and regulates the collection, use and disclosure of people's private information, makes sure who is responsible if there is a violation, and the rights of individuals to access their information.
Clear and easily accessible statements of its practices and policies; Type of personal or sensitive personal data or information collected; Purpose of collection and usage of such information; Disclosure of information including sensitive personal data or information; Reasonable security practices and procedures. The privacy policy should be published on the website of the body corporate, and be made available for view by providers of information who have provided personal information under lawful contract.
Many critics have attacked the efficacy and legitimacy of privacy policies found on the Internet. Concerns exist about the effectiveness of industry-regulated privacy policies. For example, a 2000 FTC report Privacy Online: Fair Information Practices in the Electronic Marketplace found that while the vast majority of websites surveyed had some manner of privacy disclosure, most did not meet the standard set in the FTC Principles. In addition, many organizations reserve the express right to unilaterally change the terms of their policies. In June 2009 the EFF website TOSback began tracking such changes on 56 popular internet services, including monitoring the privacy policies of Amazon, Google and Facebook. There are also questions about whether consumers understand privacy policies and whether they help consumers make more informed decisions. A 2002 report from the Stanford Persuasive Technology Lab contended that a website's visual designs had more influence than the website's privacy policy when consumers assessed the website's credibility. A 2007 study by Carnegie Mellon University claimed "when not presented with prominent privacy information..." consumers were "…likely to make purchases from the vendor with the lowest price, regardless of that site's privacy policies". However, the same study also showed that when information about privacy practices is clearly presented, consumers prefer retailers who better protect their privacy and some are willing to "pay a premium to purchase from more privacy protective websites". Furthermore, a 2007 study at the University of California, Berkeley found that "75% of consumers think as long as a site has a privacy policy it means it won't share data with third parties," confusing the existence of a privacy policy with extensive privacy protection.
Based on the common nature of this misunderstanding, researcher Joseph Turow argued to the U.S. Federal Trade Commission that the term "privacy policy" thus constitutes a deceptive trade practice and that alternative phrasing like "how we use your information" should be used instead. Privacy policies suffer generally from a lack of precision, especially when compared with the emerging form of the Data Use Statement. Where privacy statements provide a more general overview of data collection and use, data use statements represent a much more specific treatment. As a result, privacy policies may not meet the increased demand for transparency that data use statements provide. Critics also question if consumers even read privacy policies or can understand what they read. A 2001 study by the Privacy Leadership Initiative claimed only 3% of consumers read privacy policies carefully, and 64% briefly glanced at, or never read privacy policies. The average website user once having read a privacy statement may have more uncertainty about the trustworthiness of the website than before.
One possible issue is length and complexity of policies. According to a 2008 Carnegie Mellon study, the average length of a privacy policy is 2,500 words and requires an average of 10 minutes to read. The study cited that "Privacy policies are hard to read" and, as a result, "read infrequently". However, any efforts to make the information more presentable simplify the information to the point that it does not convey the extent to which users' data is being shared and sold. This is known as the "transparency paradox". There have been many studies carried out by researchers to evaluate the privacy policies of the websites of companies. One study uses natural language processing and deep learning as a proposed solution to automatically assess the efficiency of companies' privacy policies, in order to help the users become more aware.
Medical privacy, or health privacy, is the practice of maintaining the security and confidentiality of patient records. It involves both the conversational discretion of health care providers and the security of medical records. The terms can also refer to the physical privacy of patients from other patients and providers while in a medical facility, and to modesty in medical settings. Modern concerns include the degree of disclosure to insurance companies, employers, and other third parties. The advent of electronic medical records (EMR) and patient care management systems (PCMS) have raised new concerns about privacy, balanced with efforts to reduce duplication of services and medical errors. Most developed countries including Australia, Canada, Turkey, the United Kingdom, the United States, New Zealand, and the Netherlands have enacted laws protecting people's medical health privacy. However, many of these health-securing privacy laws have proven less effective in practice than in theory. In 1996, the United States passed the Health Insurance Portability and Accountability Act (HIPAA) which aimed to increase privacy precautions within medical institutions.
Electronic medical records are a more efficient way of storing medical information, yet there are many negative aspects of this type of filing system as well. Hospitals are willing to adopt this type of filing system only if they are able to ensure that the private information of their patients is sufficiently protected. Researchers have found that U.S. state legislation and regulation of medical privacy laws reduce the number of hospitals that adopt EMR by more than 24%. This is due to decreasing positive network externalities that are created by additional state protections. With increases in restrictions against the diffusion of medical information, hospitals have neglected to adopt the new EMRs because privacy laws restrict health information exchanges. With decreasing numbers of medical institutions adopting the EMR filing system, the U.S. government's plan of a national health network has not been fully recognized. The national network will ultimately cost US$156 billion in investments, yet in order for this to happen, the U.S. government needs to place a higher emphasis on protecting individual privacy. Many politicians and business leaders find that EMRs allow for more efficiency in both time and money, yet they neglect to address the decreasing privacy protections, demonstrating the significant trade-off between EMRs and individual privacy.
One of the main dangers to an individual's privacy are private corporations because of the profits they can receive from selling seemingly private information. Privacy merchants are made up of two groups - one that tries to collect people's personal information while the other focuses on using client's information to market company products. Subsequently, privacy merchants purchase information from other companies, such as health insurance companies, if there is not sufficient information from their own research. Privacy merchants target health insurance companies because, nowadays, they collect huge amounts of personal information and keep them in large databases. They often require patients to provide more information that is needed for purposes other than that of doctors and other medical workers. Additionally, people's information can be linked to other information outside of the medical field. For example, many employers use insurance information and medical records as an indicator of work ability and ethic. The selling of privacy information can also lead employers to make much money; however, this happens to many people without their consent or knowledge. Within the United States, in order to define clear privacy laws regarding medical privacy, Title 17 thoroughly explains the ownership of one's data and adjusted the law so that people have more control over their own property. The Privacy Act of 1974 offers more restrictions regarding what corporations can access outside of an individual's consent. States have created additional supplements to medical privacy laws. With HIPAA, many individuals were pleased to see the federal government take action in protecting the medical information of individuals. Yet when people looked into it, there was proof that the government was still protecting the rights of corporations. Many rules were seen as more of suggestions and the punishment for compromising the privacy of its patients were minimal. Even if release of medical information requires consent, blank authorizations can be allowed and will not ask for individuals for additional consent later on. Although there is a large group of people who oppose the selling of individual's medical information, there are groups such as the Health Benefits Coalition, the Healthcare Leadership Council, and the Health Insurance Association of America that are against the new reforms for data protection as it can ruin their work and profits. Previous controversies, such as Google's "Project Nightingale" in 2019 have demonstrated potential holes in regulations of patient data and medical information. Project Nightingale, a joint effort between Google and the healthcare network Ascension, saw to the selling of millions of patients' identifiable medical information without their consent. Though Google claimed that their process was legal in obtaining the information, there was concern between researchers on this claim.
On July 1, 2012, the Australian Government launched the Personally Controlled Electronic Health Record (PCEHR) (eHealth) system. The full implementation incorporates an electronic summary prepared by nominated healthcare providers along with consumer-provided notes. Further, the summary includes information on the individual's allergies, adverse reactions, medications, immunizations, diagnoses, and treatments. The consumer notes operate as a personal medical diary that only the individual can view and edit. The opt-in system gives people the option to choose whether to register for the eHealth record or not. As of January 2016, the Commonwealth Department of Health changed the name PCEHR to My Health Record.
2. System Architecture & Core Working Principles How does consent impact privacy? One concern is that personal control of the eHealth record via consent does not guarantee the protection of privacy. It is argued that a narrow definition, 'permission' or 'agreement', does not provide protection for privacy and is not well represented in Australian legislation. The PCEHR allows clinicians to assume consent by consumer participation in the system; however, the needs of the consumer may not be met. Critics argue that the broader definition of 'informed consent' is required, as it encompasses the provision of relevant information by the healthcare practitioner, and understanding of that information by the patient.
Is it legitimate to use personal information for public purposes? Data from the PCEHR is to be predominantly used in patient healthcare, but other uses are possible, for policy, research, audit and public health purposes. The concern is that in the case of research, what is allowed goes beyond existing privacy legislation. What are 'illegitimate' uses of health information? The involvement of pharmaceutical companies is viewed as potentially problematic. If they are perceived by the public to be more concerned with profit than public health, public acceptance of their use of PCEHRs could be challenged. Also perceived as problematic, is the potential for parties other than health care practitioners, such as insurance companies, employers, police or the government, to use information in a way which could result in discrimination or disadvantage.
What are the potential implications of unwanted disclosure of patient information? Information 'leakage' is seen as having the potential to discourage both patient and clinician from participating in the system. Critics argue the PCEHR initiative can only work, if a safe, effective continuum of care within a trusting patient/clinician relationship is established. If patients lose trust in the confidentiality of their eHealth information, they may withhold sensitive information from their health care providers.
Clinicians may be reluctant to participate in a system where they are uncertain about the completeness of the information. Are there sufficient safeguards for the protection of patient information? Security experts have questioned the registration process, where those registering only have to provide a Medicare card number, and names and birth dates of family members to verify their identity. Concerns have also been raised by some stakeholders, about the inherent complexities of the limited access features. They warn that access to PCEHR record content, may involve transfer of information to a local system, where PCEHR access controls would no longer apply.
The most comprehensive law passed is the Health Insurance Portability and Accountability Act of 1996 (HIPAA), which was later revised after the Final Omnibus Rule in 2013. HIPAA provides a federal minimum standard for medical privacy, sets standards for uses and disclosures of protected health information (PHI), and provides civil and criminal penalties for violations. Prior to HIPAA, only certain groups of people were protected under medical laws such as individuals with HIV or those who received Medicare aid. HIPAA provides protection of health information and supplements additional state and federal laws; yet it should be understood that the law's goal is to balance public health benefits, safety, and research while protecting the medical information of individuals. Yet many times, privacy is compromised for the benefits of the research and public health. According to HIPAA, the covered entities that must follow the law's set mandates are health plans, health care clearinghouses, and health care providers that electronically transmit PHI. Business associates of these covered entities are also subject to HIPAA's rules and regulations. In 2008, Congress passed the Genetic Information Nondiscrimination Act of 2008 (GINA), which aimed to prohibit genetic discrimination for individuals seeking health insurance and employment. The law also included a provision which mandated that genetic information held by employers be maintained in a separate file and prohibited disclosure of genetic information except in limited circumstances. In 2013, after GINA was passed, the HIPAA Omnibus Rule amended HIPAA regulations to include genetic information in the definition of Protected Health Information (PHI). This rule also expanded HIPAA by broadening the definition of business associates to include any entity that sends or accesses PHI such as health IT vendors.
In the course of having or being part of a medical practice, doctors may obtain information that they wish to share with the medical or research community. If this information is shared or published, the privacy of the patients must be respected. Likewise, participants in medical research that are outside the realm of direct patient care have a right to privacy as well. How to create HIPAA-compliant architecture diagrams for healthcare applications. Covers PHI data flows, encryption requirements, audit logging, BAA obligations, and AWS/Azure HIPAA-eligible services — with AI prompt templates.
HIPAA architecture diagrams are technical documentation artifacts that map how Protected Health Information (PHI) flows through a healthcare application, what controls protect it at each stage, and how the system demonstrates compliance with the HIPAA Security Rule. For health tech startups, digital health platforms, and healthcare SaaS products, a clear architecture diagram is not just good engineering practice — it is often required by compliance officers, enterprise customers, and cloud providers when executing Business Associate Agreements (BAAs). A well-structured HIPAA architecture diagram shows auditors and security reviewers exactly where PHI lives, how it's encrypted, and who can access it.
The HIPAA Security Rule (45 CFR Part 164) sets specific technical safeguard requirements that must be visible in your
Architecture
A standard architecture diagram becomes a HIPAA compliance artifact when you add the following annotations: Related guides: zero trust architecture , EU AI Act compliance architecture , DevSecOps architecture diagrams , and authentication architecture diagrams . I’d sum up HIPAA audit documentation this way: you need records that show controls exist , staff follow them , and someone checks them over time . In most cases, I’d keep these records for at least six years from creation or when they were last in effect, whichever is later. That usually includes policies, risk analysis files, training logs, BAAs, incident records, and breach files.
Architecture Tour Chicago
One point stands out: HHS has said poor or missing risk analysis was a repeat factor in breach cases. So if I were building an audit file from scratch, that’s where I’d start. The rest of this guide shows how I’d organize, store, track, and package that evidence so it’s ready when OCR asks for it. HIPAA Compliance Checklist: Essential Guide for Covered Entities & Business Associates Once owners are assigned, the next job is simple in theory and messy in practice: match each document to the rule, retention period, and audit request it supports. HIPAA documentation requirements come from the Privacy, Security, and Breach Notification Rules. These rules spell out what you need to document and how long you need to keep it. In most cases, keep HIPAA compliance records for at least six years from the date they were created or the date they were last in effect, whichever is later. [16] [15] [14] That covers policies, procedures, risk analyses, training records, breach logs, and business associate agreements. Clinical records may be subject to longer retention rules.
Architecture Boat Tour Chicago
Under the Privacy Rule (45 C.F.R. § 164.530), keep policies and procedures, Notices of Privacy Practices, authorization forms, complaint records, and role designations. Under the Security Rule (45 C.F.R. § 164.316), keep risk analyses, risk management plans, security incident logs, workforce security records, and written safeguard decisions, including encryption determinations. The Breach Notification Rule adds breach assessments, notices, and investigation records. If a required document is missing, write that down too, along with the reason. [11] After that, map those records to the OCR Audit Protocol.
Architecture Salary
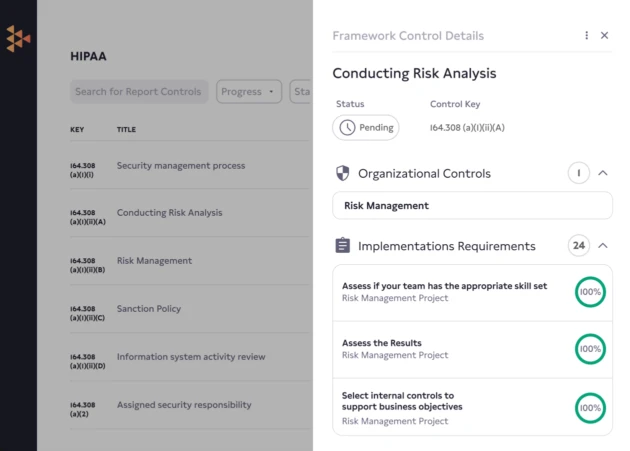
OCR's Audit Protocol is organized by rule, standard, and implementation specification. [1] [9] For each Security Rule standard, the protocol links a control to the records auditors expect to review. Under Security Management Process (164.308(a)(1)), for instance, auditors expect a written risk analysis and proof that identified risks are being managed. [1] [8] Tag each file with its CFR citation, such as Security Rule 164.312(a)(1), so an auditor can locate the right evidence without digging through folders. [1] [7] HHS's 2020 Annual Report to Congress on Breaches noted that deficient or non-existent risk analyses were a recurring contributing factor to breaches and clinical disruptions . [12] Auditors also want proof that the work happened in day-to-day operations, not just on paper. That usually means dated logs, access review sign-offs, incident tickets, and training rosters. [5] [11] Organize your evidence into three core groups. In most HIPAA audits, reviewers focus on three documentation areas that show compliance is happening in day-to-day work, not just sitting in a policy binder. [1] [19] [10] These groups give you a clean way to sort the records auditors are most likely to request.
Architecture Degree
This is the base of the audit package. Your Security Risk Analysis (SRA) should cover every environment where ePHI is handled. It needs to spell out the method used, the threats and vulnerabilities found, and the related likelihood and impact ratings. Update the SRA at least once a year and after major changes. [13] [17] [20] [22] [2] [4] Next to the SRA, keep a risk register and remediation plan that show which risks were found, who owns each one, the timeline for fixing them, and the current status. If a risk is accepted, document the reason and the approver. [17] [18] [20] Your technical controls should tie back to the risks listed in the SRA. Make that connection plain in both places.
Architecture Styles
Governance records pull the program together. Each policy should show a version number, effective date, review date, and approver. Keep sanction records for workforce HIPAA violations while protecting proper confidentiality. [1] [6] [19] [20] Think of these records as the control layer that shows the program was approved, reviewed, and kept current. 3. Software Implementation, Frameworks & Protocols Auditors will want proof that training happened, not just a statement that training exists. Keep a written training policy, the course materials or curriculum, and completion logs that show who was trained, on what date, and in which course. LMS completion logs or signed attestations both work. Role-based training also matters, especially for IT, clinical, and billing staff.
Architecture Schools
[19] [10] [20] Vendor records need close attention because many breaches involve third parties. You should keep a current inventory of every business associate and subcontractor that handles PHI or ePHI. That includes EHR hosts, billing companies, cloud storage providers, IT support firms, and medical device manufacturers. For each one, maintain a signed, current Business Associate Agreement (BAA) with terms that match current HIPAA requirements. Track the review date and renewal status for each BAA. Pre-contract security assessments and oversight records - such as SOC 2 reports or periodic reassessments - help round out this group. [19] [10] [20] [6] Put together, these records show that both staff and outside partners were trained, reviewed, and governed.
Architecture Boat Tour
This category is all about operational proof. Policy language alone won't do the job. The table below shows the main artifact types and what each one needs to prove: [1] [2] [20] Each control should link back to the risk that led to it. If an incident turns up a gap, that finding should feed into policy updates and staff training. Auditors use this set of records to check whether controls are operating over time. [1] [17] [2] [20] Use these three categories as the backbone of your evidence repository structure.
Architecture Design
Document categories only help if an auditor can find the right file fast. That means your evidence repository should line up with HIPAA requirements and controls , not your org chart or yearly archive folders. The goal is simple: for each citation, there should be one clear evidence trail. Set up the repository so each HIPAA citation maps to clear, easy-to-find proof. A top-level folder like HIPAA Audit Evidence works well. Under that, use subfolders that match what auditors usually look for: Use one file naming format across the whole repository. The section calls for MM-DD-YYYY , so stick with that every time. For example: 08-12-2026_Risk-Analysis_Final.pdf . That may sound small, but mixed date formats can turn a simple file search into a mess.
Architecture Jobs
You’ll also want a master evidence index in a spreadsheet or database table. Think of it as the map to the whole repository. Each row should represent one artifact and include the evidence ID, document name, document owner, source system, HIPAA citation covered, related control or policy reference, effective date, scheduled review date, and retention deadline. A good index makes missing items stand out before an auditor finds them. It also lets auditors filter by HIPAA citation and jump straight to the supporting file.
Once the folder structure is in place, handle version history and retention the same way for every document type. Each controlled document should include a version number, effective date, approval date, and a short changelog that says what changed and why. If a policy gets updated, mark the old copy Superseded and keep it in the same folder instead of deleting it. That older copy may be the exact record an auditor needs to review for a past period.
Use the same retention rule across training logs, risk analyses, and incident files, and log each retention deadline in the master index. [23] [25] For technical proof, don’t lean on a policy summary alone. Store the actual export file or screenshot as a dated artifact. For example: 08-12-2026_Access-Control-Config_EHR_Baseline.pdf . That gives the auditor direct proof of what was in place on that date.
Some platforms make this easier. Censinet RiskOps ™ , for example, keeps audit trails by default and logs each change to risk records, assessments, and attached evidence. That cuts down on the manual work needed to show version history during an audit. [24] In practice, an auditor should be able to go from a HIPAA citation to the related control and then to dated proof without asking your team to fill in the gaps.
Once your repository structure is set up, templates make the whole process easier to manage. They help keep evidence complete, current, and ready to share. More importantly, they cut down on the last-minute scramble that tends to happen before an audit. They also give IT, compliance, HR, and legal a common format, so people aren't rebuilding the same file five different ways.
The most useful templates are the ones that line up with what OCR auditors actually request. A risk assessment worksheet should record each information asset, its threats and vulnerabilities, likelihood and impact scores on a 1–5 scale, current controls, and a named owner with a remediation due date. An evidence matrix should tie each HIPAA citation - like §164.308(a)(1)(ii)(A) for risk analysis or §164.312(a)(2)(i) for unique user identification - to the exact evidence file and its last validation date. [27] [26] If a row in that matrix is blank, that's a gap you can fix before an auditor spots it.
Each template should also have a clear owner and a recurring trigger, such as vendor onboarding or an annual review. That's what keeps documentation from going stale. When evidence is spread across a lot of systems, one shared platform can save a lot of pain. Spreadsheets tend to break down once risk data starts stretching across vendors, applications, and devices.
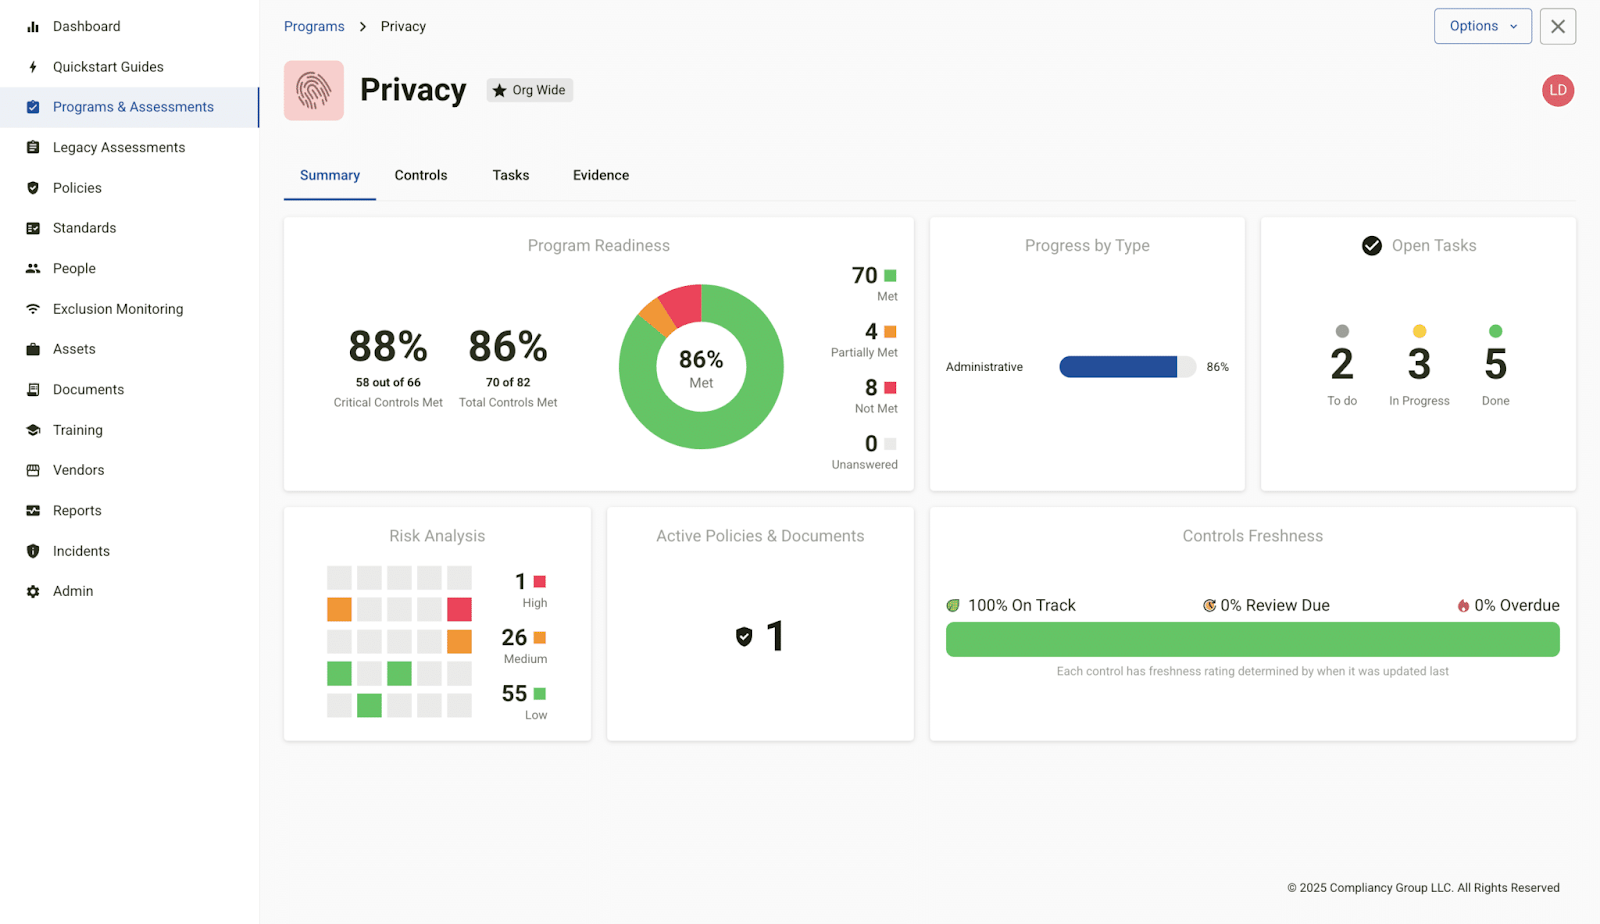
Censinet RiskOps™ brings completed vendor and internal risk assessments, linked evidence, BAA status, and mitigation tasks into one audit view. Censinet AI ™ can draft HIPAA-aligned policy language, map uploaded evidence to controls, flag stale documentation, and send high-risk findings for human review before approval. An audit package only works if the level of detail matches the type of audit. Desk audits, onsite reviews, and third-party assessments may pull from the same source records, but they do not ask for the same depth of documentation. [6] [28] [29] Use the OCR Audit Protocol as the framework, keep evidence current and version-controlled, and pull each package from the same repository. [1] [4] [3] Start with a thorough, organization-wide risk analysis . HIPAA requires it, and it should cover every system that handles ePHI.
The goal is simple: find threats, spot weak points, and estimate the impact if something goes wrong. Then build a compliance inventory for assets and documentation. That way, if auditors ask for proof, you can find the right records fast instead of scrambling to piece them together at the last minute. Review internal audits and risk analyses at least once a year . Also review them after major system upgrades, security incidents, or regulatory changes. Those events can shift risk fast, so waiting for the next annual check may leave gaps.
More fast-moving records need a tighter cadence. Access control matrices and risk assessments should be reviewed quarterly . Personnel access records should be updated right away when staffing changes happen, with routine audits layered in as well. Use a centralized, searchable evidence library as your single source of truth. Keep policies, risk analyses, training logs, incident reports, and system inventories in one organized, version-controlled repository.
A simple setup goes a long way. Group files by HIPAA control area, use the same naming format across the repository, and set role-based access controls so the right people can view or update the right records. Add change logging too, so you can see who changed what and when. For long-term recordkeeping, follow HIPAA’s six-year retention minimum. For audit logs, use immutable or WORM storage so those records can’t be altered after the fact.
4. Practical Deployment, Analysis & Case Studies Explore how healthcare organizations use Censinet to transform assessments into prioritized action and operational resilience. Explore how healthcare organizations use Censinet to transform assessments into prioritized action and operational resilience.
Master HIPAA audit documentation with our expert checklist. Ensure compliance, reduce audit risk, and streamline your healthcare organization's documentation processes. HIPAA Compliance Audit Documentation Checklist: A Healthcare Provider's Complete Guide Healthcare organizations face increasingly rigorous HIPAA compliance audits . With OCR enforcement actions rising and penalties exceeding $4.5 million for single violations, thorough documentation has never been more critical. This comprehensive checklist ensures your organization is audit-ready, protecting patient data and your reputation.
At Pentagon Infosec , our CISA-certified compliance architects have guided 200+ healthcare entities through HIPAA audits in just 15-20 days. We've identified the documentation gaps that trigger audit findings —and how to eliminate them. HIPAA audits evaluate three core pillars: Administrative, Physical, and Technical safeguards . Documentation proves your compliance efforts. Without it, auditors assume non-compliance. This creates legal exposure, operational disruptions, and financial penalties. Strong documentation demonstrates due diligence and reduces audit scope significantly.
Review your current documentation against this checklist. Identify gaps. Our compliance architects recommend categorizing gaps by severity: Critical (audit-blocking), High (significant findings), Medium (observations), Low (best practices). Focus on critical and high-severity gaps first. For technical controls, generate system configuration reports proving compliance. For administrative controls, draft policies if missing, then document implementation.
Deploy log aggregation, automate access reviews, and establish weekly compliance monitoring dashboards. This reduces manual effort during audits and demonstrates continuous compliance. Simulate OCR audit procedures. Review documentation completeness, verify system controls align with policies, test user access appropriately matches authorization forms.
Document remediation actions, completion dates, and responsible parties. Maintain remediation evidence for auditor review. Centralized Repository: Store all compliance documentation in a secure, organized location (shared drive, documentation management system). Use consistent naming conventions and version control. Ownership Assignment: Designate documentation owners by domain (IT, Privacy, Risk Management). Regular updates prevent outdated documentation.
Version Control: Maintain policy version history with effective dates and change summaries. Auditors expect controlled documentation evolution. Accessibility: Ensure audit teams can quickly access all requested documentation. Organized structures reduce audit timelines significantly—we typically complete document collection in 5-7 days.
The Security Rule requires minimum 6-year retention for all compliance documentation. Access logs require minimum 6-month retention. Best practice: Retain audit documentation for 7 years to account for investigation timelines and potential enforcement actions. Begin documenting immediately. Prospective documentation is better than nothing. For gaps, document remediation actions and corrective measures implemented. Auditors assess your current state and improvement trajectory—not just historical perfection.
Not necessarily. Centralized policies with location-specific annexes work well. However, access controls, physical security assessments, and log reviews should address each location. Document variations in your centralized system. Annual minimum for risk assessments and policy reviews. System documentation updates should occur whenever infrastructure, applications, or security controls change. Access authorization updates happen with staff changes. Continuous documentation refresh prevents last-minute scrambles before OCR audits.
Vendor documentation (system architecture, security certifications, SOC 2 reports) contributes but doesn't replace organizational documentation. You must document how vendor systems fit your HIPAA framework, your acceptance of residual risks, and your monitoring procedures. BAAs must specify vendor HIPAA obligations. Strong documentation transforms HIPAA compliance from abstract responsibility to measurable, auditable practice. It demonstrates leadership commitment, enables staff compliance, and protects patient privacy meaningfully. Organizations with comprehensive documentation typically reduce audit findings by 60-70%—turning audits from high-stress events into validation of mature security practices.
Your next step: Begin with this checklist today. Identify documentation priorities. Assign ownership. Set 30-day target for critical gaps. This disciplined approach reduces audit exposure and establishes a compliance culture protecting patient data continuously. For comprehensive audit preparation aligned with 2026 regulatory standards, explore our Compliance Audit Checklist 2026 service. Our CISA-certified architects deliver complete audit readiness in 15-20 days, combining technical verification with documentation excellence.
CISA, ISO 27001 LA, AWS Certified. 11+ years in information security, cloud services, and compliance. Founder of Pentagon Infosec. 5. Performance Evaluation & Extended Technical Observations Designing a HIPAA-compliant database starts with clear alignment to the Security Rule and a risk-based mindset. Your goal is to safeguard Electronic Protected Health Information (ePHI) by combining resilient architecture, strict access controls, strong encryption, comprehensive auditability, and a tested recovery strategy.
Segment your environment so the database that stores ePHI resides in a private, non-routable subnet with no public IPs. Place application tiers in separate subnets and expose only the minimal ingress through a Web Application Firewall (WAF) and application gateways, not directly to the database. Enforce least privilege at the network layer. Use allowlists between tiers, granular security groups, and micro-segmentation to restrict lateral movement. Route all administrative access through a hardened bastion or privileged access pathway, enforce MFA, and log every session.
Minimize the database’s egress. Deny default outbound traffic, allow only required destinations (for example, key management or logging endpoints), and proxy updates through controlled paths. Separate dev, test, and prod networks; replicate ePHI only where necessary and with masking or tokenization when possible. Apply Role-Based Access Control (RBAC) to align privileges with job functions. Map roles such as Reader, Data Steward, and DBA to explicit permissions; separate duties so no single role can both exfiltrate and approve access to ePHI.
Integrate database access with an identity provider for SSO and MFA. Prefer short-lived, just-in-time credentials issued via brokers, certificates, or Kerberos tickets. For service accounts, scope privileges narrowly, rotate secrets automatically, and monitor non-human access as closely as human access. Encrypt data at rest using Advanced Encryption Standard (AES-256) via transparent database encryption or volume-level encryption. For highly sensitive fields (for example, SSNs), add field-level or application-layer encryption to reduce blast radius.
Protect keys with a managed KMS or HSM, enforce role separation for key custodians, and rotate master and data keys on a defined cadence. Use envelope encryption and ensure cryptographic modules are validated to appropriate standards. Encrypt data in transit with Transport Layer Security (TLS 1.2+) —prefer TLS 1.3 where available. Enforce server-side certificate validation, consider mutual TLS for administrative and service-to-service traffic, and disable legacy ciphers and protocols to ensure forward secrecy.
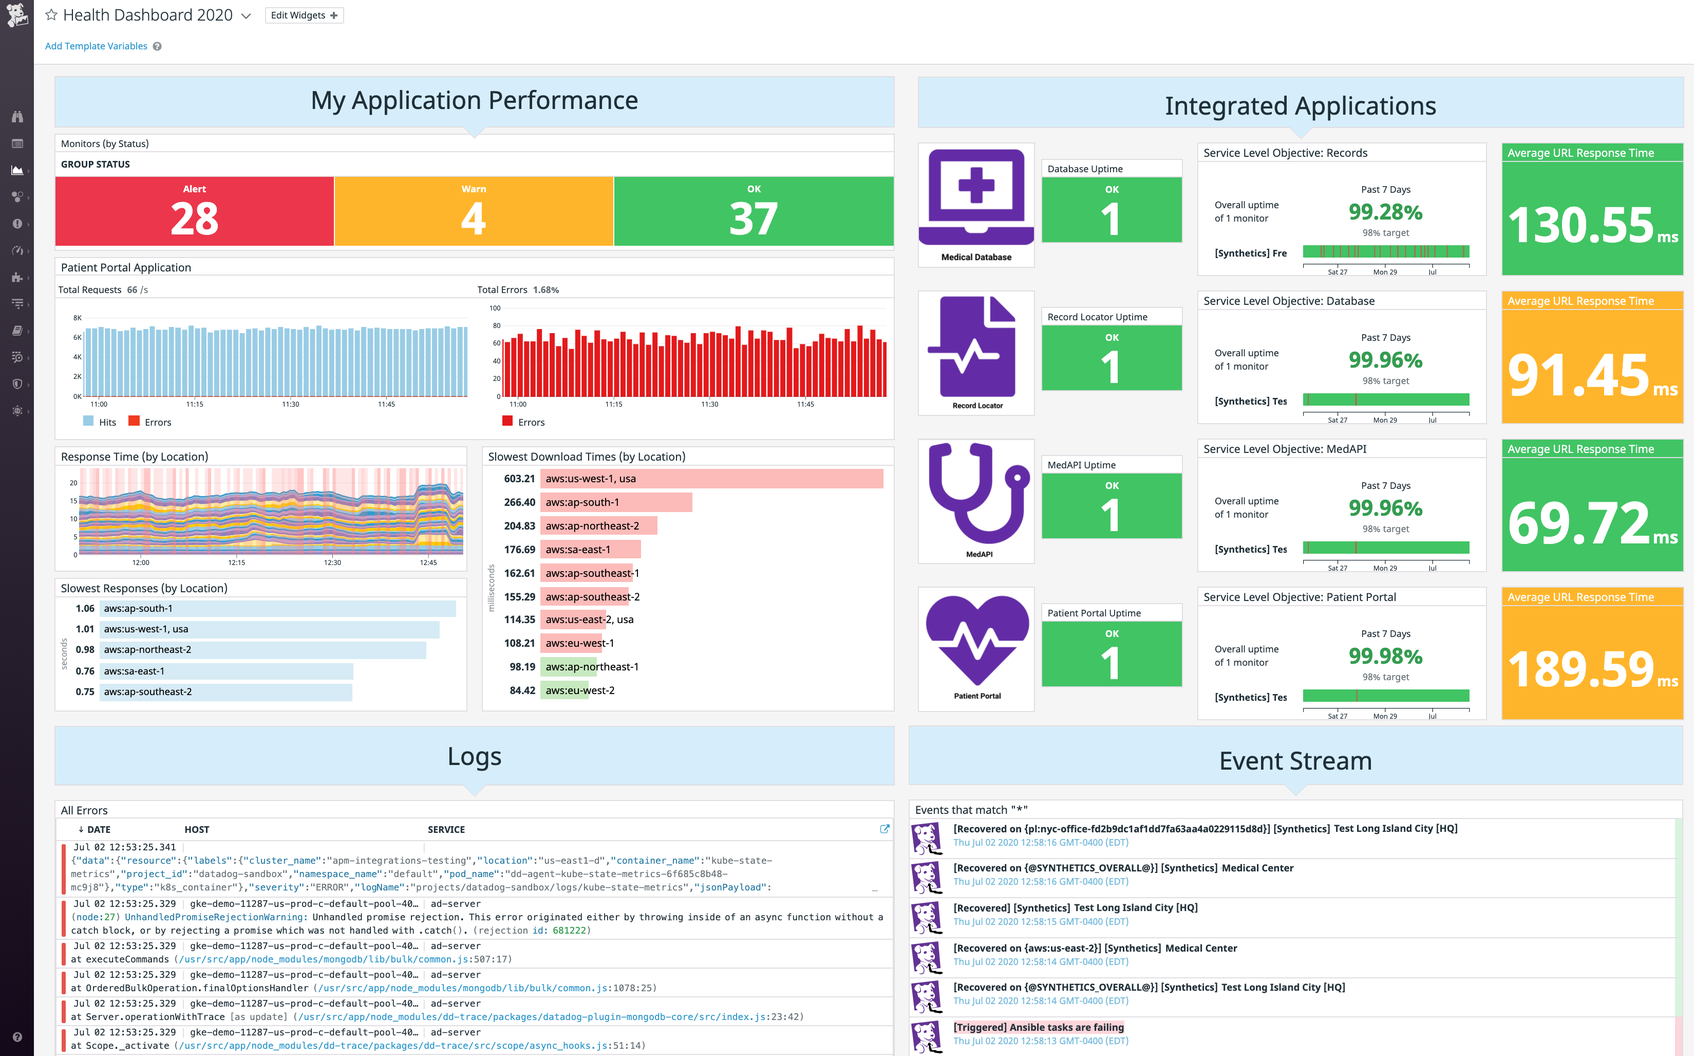
Implement audit controls that capture who accessed ePHI, what was viewed or changed, when and from where, and whether access was authorized or denied. Log authentication events, privilege changes, DDL/DCL/DML operations, exports, configuration changes, and key-management actions. Centralize logs in an append-only store with immutability controls. Hash and time-stamp records, synchronize clocks across systems, and monitor with a SIEM for anomaly detection and alerting. Redact sensitive values in logs to prevent accidental disclosure of ePHI.
Join thousands of organizations that trust Accountable to manage their compliance needs. Guarantee integrity using ACID transactions, foreign keys, and constraints that encode business rules. Apply row-versioning and checksums to detect tampering; for critical payloads, use cryptographic hashes or HMACs to verify that content has not changed.
Validate inputs at the application layer and use parameterized queries to prevent injection. Monitor for abnormal write patterns, and run continuous integrity checks that compare aggregates, counts, and hash samples against expected baselines. Secure all data flows carrying ePHI with TLS 1.2+ and prefer TLS 1.3 where supported. Use mutual TLS, IP allowlists, and strict certificate lifecycle management to prevent man-in-the-middle attacks.
Shield public-facing endpoints with a WAF to filter injection, deserialization, and bot traffic before it reaches application logic. When exchanging ePHI across organizations, employ VPNs or private connectivity and consider message-level encryption for store-and-forward workflows. Develop a written, tested Disaster Recovery Plan that defines Recovery Time Objective (RTO) and Recovery Point Objective (RPO) for the database and downstream systems. Replicate data across fault domains and regions with automated failover and consistent encryption and access controls.
Follow a 3-2-1 backup strategy with immutable, offline copies. Conduct periodic restore drills and cross-region failover exercises; document runbooks, escalation paths, and communication templates to keep teams aligned under stress. A HIPAA-compliant database weaves together segmented architecture, RBAC and strong authentication, AES-256 at rest and TLS 1.2+ in transit, rigorous audit logging, integrity safeguards, and a rehearsed recovery strategy. Treat compliance as an ongoing program—measure, test, and refine controls as your environment and risks evolve.
Prioritize network segmentation, least-privilege RBAC, MFA-backed authentication, AES-256 encryption at rest, TLS 1.2+ in transit, comprehensive audit controls with immutable storage, integrity protections (constraints, hashes, and PITR), a WAF for public-facing traffic, and a tested Disaster Recovery Plan. Together, these controls reduce attack surface, detect misuse, and sustain availability.
HIPAA requires retaining required documentation for six years from the date of creation or last effective date. Because security auditing supports those requirements, many organizations adopt a six-year Audit Trail Retention policy for logs relevant to the Security Rule . Your risk analysis , state laws, and contractual obligations may justify longer retention. HIPAA does not mandate specific algorithms, but industry-aligned practice is AES-256 for data at rest and Transport Layer Security (TLS 1.2+)—preferably TLS 1.3—for data in transit. Use FIPS-validated cryptographic modules, rotate keys regularly, and consider mutual TLS for administrative and service-to-service connections.
Use RBAC mapped to job functions, enforce MFA via SSO, and issue short-lived, just-in-time credentials. Restrict access with views, row/column-level security, and stored procedures; separate duties for administrators and data stewards; monitor and log all access; and employ approval-based, time-bound “break-glass” workflows for exceptional cases. Join thousands of organizations that trust Accountable to manage their compliance needs.
Strong dental compliance training protects patients, your team, and your practice. This guide tur... Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/Information%20privacy • https://en.wikipedia.org/wiki/Privacy%20policy • https://en.wikipedia.org/wiki/Medical%20privacy • https://architecturediagram.ai/blog/hipaa-architecture-diagrams • https://www.censinet.com/perspectives/ultimate-hipaa-audit-documentation-guide • https://pentagoninfosec.com/blog/hipaa-compliance-audit-documentation • https://www.accountablehq.com/post/how-to-design-a-hipaa-compliant-database-architecture-security-controls-and-audit-logs • https://www.peerbits.com/blog/hipaa-by-design-engineering-blueprint-for-compliant-healthcare-systems.html
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.
Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Hipaa Data Privacy Auditing Tool.
[*] Metasploit Scan Running on Target Subnet for Hipaa Data Privacy Auditing Tool... [✓] SafeBreach / AttackIQ Continuous Exposure Agent Triggered ──────────────────────────────────────────────────────────────────────── [11:48:02.104] PICUS Threat Scenario Dispatched: Lateral Movement SMB Probe [11:48:02.185] BLOCKED Endpoint EDR Detected Technique | Packet Tracer ACL Denied [11:48:02.240] CYMULATE Prevention Rate = 96.8% | SIEM Latency = 38 ms [11:48:02.312] ATTACKIQ Posture Validation: MITRE ATT&CK matrix fully validated ──────────────────────────────────────────────────────────────────────── [✓] BAS Simulation Run Complete: Defense-in-Depth Verified Across All Controls
| Simulation Platform | Simulated Threat / Scenario | Target Subsystem | Detection Latency | Security Control Status |
|---|---|---|---|---|
| Metasploit Framework | Port Reconnaissance & Fingerprinting | DMZ Gateway | 18 ms | MONITORED & DROPPED |
| AttackIQ Enterprise | Credential Access (LSASS Dump) | Windows Client | 42 ms | BLOCKED BY EDR |
| SafeBreach | Ransomware Lateral Movement | File Server Subnet | 65 ms | ISOLATED IN SANDBOX |
| Cymulate | Email Gateway Malicious Attachment | Corporate Mailbox | 120 ms | QUARANTINED |
| Picus Security | Command & Control (C2) Beaconing | Edge Firewall | 24 ms | BLOCKED BY ACL |