Complete Technical Paper Content — Medical Device Security Monitoring System For Hospitals
Overview & System Context
Medical Device Security Monitoring System For Hospitals: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~9583 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background A medical device is any device intended to be used for medical purposes. In countries around the world, medical devices must be proven safe and effective before they are marketed. As a general rule, the higher the associated risk of the device the more testing is required to establish safety and efficacy. Further, as associated risk increases the potential benefit to the patient must also increase. Discovery of what would be considered a medical device by modern standards dates as far back as c. 7000 BC in Baluchistan where Neolithic dentists used flint-tipped drills and bowstrings. Study of archeology and Roman medical literature also indicate that many types of medical devices were in widespread use during the time of ancient Rome.
In the United States, it was not until the Federal Food, Drug, and Cosmetic Act (FD&C Act) in 1938 that medical devices were regulated at all. It was not until later in 1976 that the Medical Device Amendments to the FD&C Act established medical device regulation and oversight as we know it today in the United States. Medical device regulation in Europe as we know it today came into effect in 1993 by what is collectively known as the Medical Device Directive (MDD). On May 26, 2017, the Medical Device Regulation (MDR) replaced the MDD. Medical devices vary in both their intended use and indications for use.
Examples range from simple, low-risk devices such as tongue depressors, medical thermometers, disposable gloves, and bedpans to complex, high-risk devices that are implanted and sustain life. Examples of high-risk devices include artificial hearts, pacemakers, joint replacements, and CT scans. The design of medical devices constitutes a major segment of the field of biomedical engineering. The global medical device market was estimated to be between $220 and US$250 billion in 2013. The United States controls ≈40% of the global market followed by Europe (25%), Japan (15%), and the rest of the world (20%). Although collectively Europe has a larger share, Japan has the second largest country market share. The largest market shares in Europe (in order of market share size) belong to Germany, Italy, France, and the United Kingdom. The rest of the world comprises regions like (in no particular order) Australia, Canada, China, India, and Iran.
A global definition for medical device is difficult to establish because there are numerous regulatory bodies worldwide overseeing the marketing of medical devices. Although these bodies often collaborate and discuss the definition in general, there are subtle differences in wording that prevent a global harmonization of the definition of a medical device, thus the appropriate definition of a medical device depends on the region. Often a portion of the definition of a medical device is intended to differentiate between medical devices and drugs, as the regulatory requirements of the two are different.
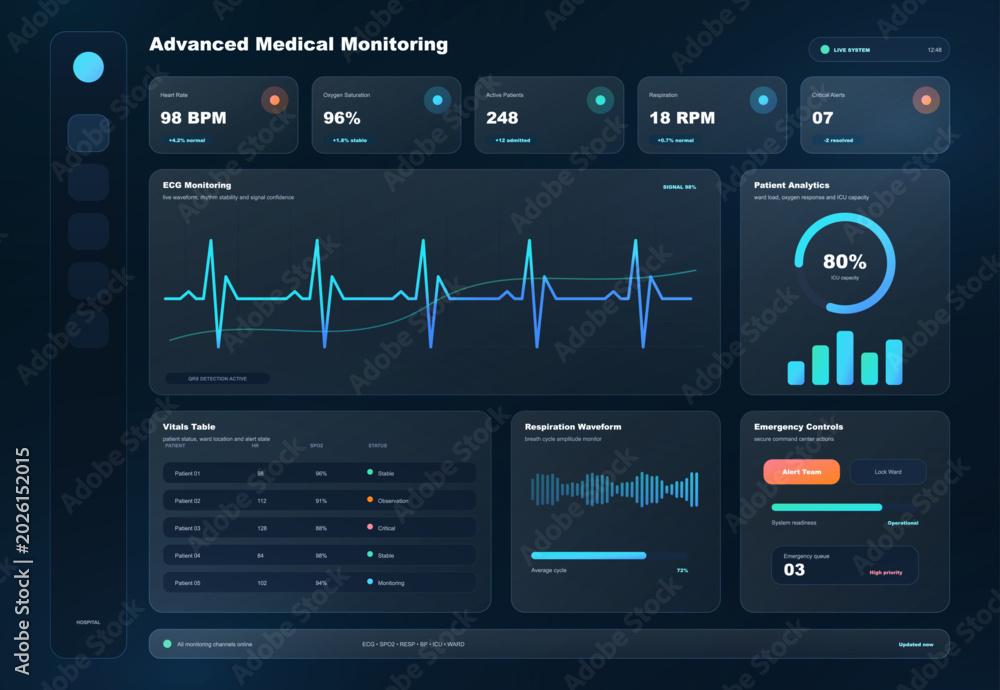
Definitions also often recognize In vitro diagnostics as a subclass of medical devices and establish accessories as medical devices. recognized in the official National Formulary, or the United States Pharmacopoeia, or any supplement to them Intended for use in the diagnosis of disease or other conditions, or in the cure, mitigation, treatment, or prevention of disease, in man or other animals, or Intended to affect the structure or any function of the body of man or other animals, and which does not achieve its primary intended purposes through chemical action within or on the body of man or other animals and which is not dependent upon being metabolized for the achievement of its primary intended purposes. The term 'device' does not include software functions excluded pursuant to section 520(o)." diagnosis, prevention, monitoring, treatment or alleviation of disease, diagnosis, monitoring, treatment, alleviation of or compensation for an injury or handicap, investigation, replacement or modification of the anatomy or of a physiological process, control of conception, and which does not achieve its principal intended action in or on the human body by pharmacological, immunological or metabolic means, but which may be assisted in its function by such means;" Figure 1: Advanced Medical Monitoring Dashboard Interface. Dark hospital ...
Directive 90/385/EEC regarding active implantable medical devices Directive 93/42/EEC regarding medical devices Directive 98/79/EC regarding in vitro diagnostic medical devices (Until 2022, the In Vitro Diagnosis Regulation (IVDR) will replace the EU's current Directive on In-Vitro Diagnostic (98/79/EC)). They aim at ensuring a high level of protection of human health and safety and the good functioning of the Single Market. These three main directives have been supplemented over time by several modifying and implementing directives, including the last technical revision brought about by Directive 2007/47 EC.
The government of each Member State must appoint a competent authority responsible for medical devices. The competent authority (CA) is a body with authority to act on behalf of the member state to ensure that member state government transposes requirements of medical device directives into national law and applies them. The CA reports to the minister of health in the member state. The CA in one Member State has no jurisdiction in any other member state, but exchanges information and tries to reach common positions. In the UK, for example, the Medicines and Healthcare products Regulatory Agency (MHRA) acted as a CA. In Italy it is the Ministero Salute (Ministry of Health) Medical devices must not be mistaken with medicinal products. In the EU, all medical devices must be identified with the CE mark. The conformity of a medium or high risk medical device with relevant regulations is also assessed by an external entity, the Notified Body, before it can be placed on the market. In September 2012, the European Commission proposed new legislation aimed at enhancing safety, traceability, and transparency. The regulation was adopted in 2017. The current core legal framework consists of two regulations, replacing the previous three directives: The Medical Devices Regulation (MDR (EU) 2017/745) The In Vitro Diagnostic medical devices regulation (IVDR (EU) 2017/746) The two regulations are supplemented by several guidances developed by the Medical Devices Coordination Group (MDCG).
The term medical device, as defined in the Food and Drugs Act, is "any article, instrument, apparatus or contrivance, including any component, part or accessory thereof, manufactured, sold or represented for use in: the diagnosis, treatment, mitigation or prevention of a disease, disorder or abnormal physical state, or its symptoms, in a human being; the restoration, correction or modification of a body function or the body structure of a human being; the diagnosis of pregnancy in a human being; or the care of a human being during pregnancy and at and after the birth of a child, including the care of the child. It also includes a contraceptive device but does not include a drug." The term covers a wide range of health or medical instruments used in the treatment, mitigation, diagnosis or prevention of a disease or abnormal physical condition. Health Canada reviews medical devices to assess their safety, effectiveness, and quality before authorizing their sale in Canada. According to the Act, medical device does not include any device that is intended for use in relation to animals.
The regulatory authorities recognize different classes of medical devices based on their potential for harm if misused, design complexity, and their use characteristics. Each country or region defines these categories in different ways. The authorities also recognize that some devices are provided in combination with drugs, and regulation of these combination products takes this factor into consideration. Classifying medical devices based on their risk is essential for maintaining patient and staff safety while simultaneously facilitating the marketing of medical products. By establishing different risk classifications, lower risk devices, for example, a stethoscope or tongue depressor, are not required to undergo the same level of testing that higher risk devices such as artificial pacemakers undergo. Under the GHTF model, regulatory controls increase from Class A to Class D and may include independently audited quality management systems, review of technical documentation and clinical evidence, and post-market evaluation.
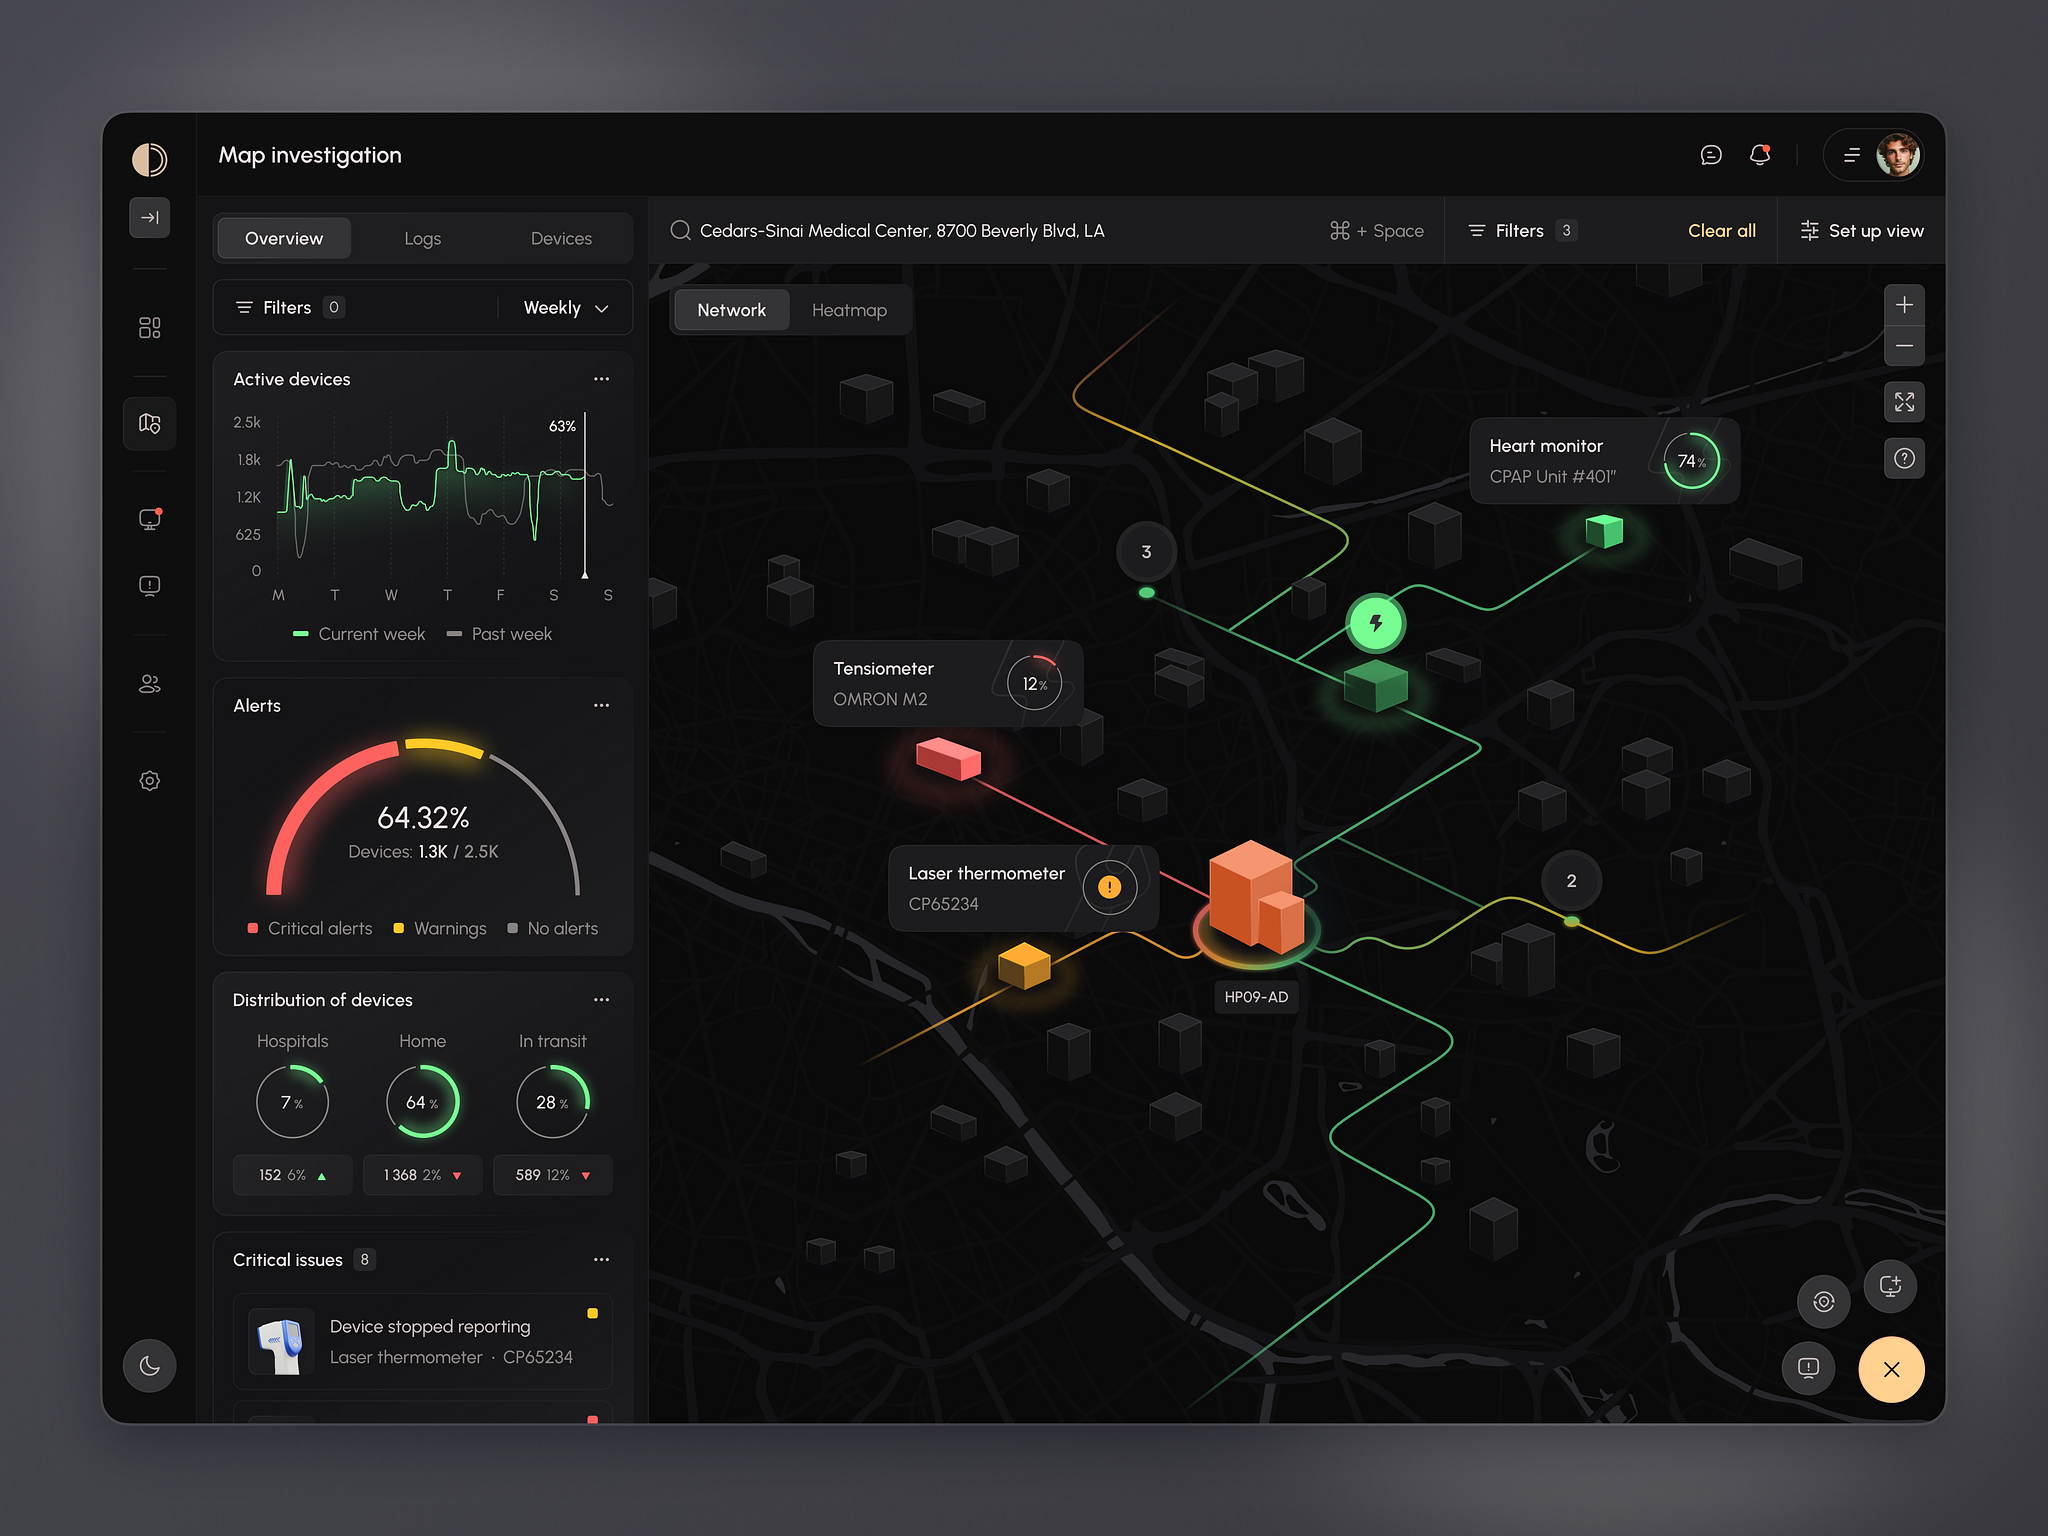
Figure 2: Smart Medical Device Monitoring - UI/UX design by Gotoinc Studio on ... Under the Food, Drug, and Cosmetic Act, the U.S. Food and Drug Administration recognizes three classes of medical devices, based on the level of control necessary to assure safety and effectiveness. The classification procedures are described in the Code of Federal Regulations, Title 21, part 860 (usually known as 21 CFR 860). Class I devices are subject to the least regulatory control and are not intended to help support or sustain life or be substantially important in preventing impairment to human health, and may not present an unreasonable risk of illness or injury. Examples of Class I devices include elastic bandages, examination gloves, and hand-held surgical instruments. Class II devices are subject to special labeling requirements, mandatory performance standards and postmarket surveillance.
Examples of Class II devices include acupuncture needles, powered wheelchairs, infusion pumps, air purifiers, surgical drapes, stereotaxic navigation systems, and surgical robots. Class III devices are usually those that support or sustain human life, are of substantial importance in preventing impairment of human health, or present a potential, unreasonable risk of illness or injury and require premarket approval. Examples of Class III devices include implantable pacemakers, pulse generators, HIV diagnostic tests, automated external defibrillators, and endosseous implants.
Class I Devices: Non-invasive, everyday devices or equipment. Class I devices are generally low risk and can include bandages, compression hosiery, or walking aids. Such devices require only for the manufacturer to complete a Technical File. Class Is Devices: Class Is devices are similarly non-invasive devices, however this sub-group extends to include sterile devices. Examples of Class Is devices include stethoscopes, examination gloves, colostomy bags, or oxygen masks. These devices also require a technical file, with the added requirement of an application to a European Notified Body for certification of manufacturing in conjunction with sterility standards. Class Im Devices: This refers chiefly to similarly low-risk measuring devices. Included in this category are: thermometers, droppers, and non-invasive blood pressure measuring devices. Once again the manufacturer must provide a technical file and be certified by a European Notified Body for manufacturing in accordance with metrology regulations. Class Ir Devices: Reusable surgical instruments include devices like ophthalmic scissors or needle holders. Under the MDR, a manufacturer of Class Ir devices must be certified by a Notified Body with regard to reusability aspects. Class IIa Devices: Class IIa devices generally constitute low to medium risk and pertain mainly to devices installed within the body in the short term. Class IIa devices are those which are installed within the body for only between 60 minutes and 30 days. Examples include hearing-aids, blood transfusion tubes, and catheters. Requirements include technical files and a conformity test carried out by a European Notified Body. Class IIb Devices: Slightly more complex than IIa devices, class IIb devices are generally medium to high risk and will often be devices installed within the body for periods of 30 days or longer. Examples include ventilators and intensive care monitoring equipment. Identical compliance route to Class IIa devices with an added requirement of a device type examination by a Notified Body. Note: Some parts of the regulations differentiate between Class IIb and Class IIb implantable devices, that is, some rules of the MDR apply specifically to Class IIb implantable and Class III devices, e.g. Article 52 paragraph 4 of the MDR. Class III Devices: Class III devices are strictly high risk devices. Examples include balloon catheters, prosthetic heart valves, pacemakers, etc. The steps to approval here include a full quality assurance system audit, along with examination of both the device's design and the device itself by a European Notified Body. The authorization of medical devices is guaranteed by a Declaration of Conformity. This declaration is issued by the manufacturer itself, but for products in Class Is, Im, Ir, IIa, IIb or III, it must be verified by a Certificate of Conformity issued by a Notified Body. A Notified Body is a public or private organisation that has been accredited to validate the compliance of the device to the European Directive. Medical devices that pertain to class I (on condition they do not require sterilization or do not measure a function) can be marketed purely by self-certification. The European classification depends on rules that involve the medical device's duration of body contact, invasive character, use of an energy source, effect on the central circulation or nervous system, diagnostic impact, or incorporation of a medicinal product. Certified medical devices should have the CE mark on the packaging, insert leaflets, etc.. These packagings should also show harmonised pictograms and EN standardised logos to indicate essential features such as instructions for use, expiry date, manufacturer, sterile, do not reuse, etc. In November 2018, the Federal Administrative Court of Switzerland decided that the "Sympto" app, used to analyze a woman's menstrual cycle, was a medical device because it calculates a fertility window for each woman using personal data. The manufacturer, Sympto-Therm Foundation, argued that this was a didactic, not a medical process. the court laid down that an app is a medical device if it is to be used for any of the medical purposes provided by law, and creates or modifies health information by calculations or comparison, providing information about an individual patient.
Classes I and II distinguish between extremely low and low risk devices. Classes III and IV, moderate and high risk respectively, are highly and specially controlled medical devices. In vitro diagnostics have three risk classifications. Figure 3: Cybersecurity in Patient Monitoring: Protecting Patient Data The Medical Devices Bureau of Health Canada recognizes four classes of medical devices based on the level of control necessary to assure the safety and effectiveness of the device. Class I devices present the lowest potential risk and do not require a licence. Class II devices require the manufacturer's declaration of device safety and effectiveness, whereas Class III and IV devices present a greater potential risk and are subject to in-depth scrutiny. A guidance document for device classification is published by Health Canada. Canadian classes of medical devices correspond to the European Council Directive 93/42/EEC (MDD) devices: Class I (Canada) generally corresponds to Class I (ECD) Class II (Canada) generally corresponds to Class IIa (ECD) Class III (Canada) generally corresponds to Class IIb (ECD) Class IV (Canada) generally corresponds to Class III (ECD) Examples include surgical instruments (Class I), contact lenses and ultrasound scanners (Class II), orthopedic implants and hemodialysis machines (Class III), and cardiac pacemakers (Class IV).
Iran produces about 2,000 types of medical devices and medical supplies, such as appliances, dental supplies, disposable sterile medical items, laboratory machines, various biomaterials and dental implants. 400 Medical products are produced at the C and D risk class with all of them licensed by the Iranian Health Ministry in terms of safety and performance based on EU-standards. Some Iranian medical devices are produced according to the European Union standards. Some producers in Iran export medical devices and supplies which adhere to European Union standards to applicant countries, including 40 Asian and European countries. Some Iranian producers export their products to foreign countries.
Validation and verification of medical devices ensure that they fulfil their intended purpose. Validation or verification is generally needed when a health facility acquires a new device to perform medical tests. The main difference between the two is that validation is focused on ensuring that the device meets the needs and requirements of its intended users and the intended use environment, whereas verification is focused on ensuring that the device meets its specified design requirements.
Medical device packaging is highly regulated. Often medical devices and products are sterilized in the package. Sterility must be maintained throughout distribution to allow immediate use by physicians. A series of special packaging tests measure the ability of the package to maintain sterility. Relevant standards include: ASTM F2097 – Standard Guide for Design and Evaluation of Primary Flexible Packaging for Medical Products ASTM F2475-11 – Standard Guide for Biocompatibility Evaluation of Medical Device Packaging Materials EN 868 Packaging materials and systems for medical devices to be sterilized, General requirements and test methods ISO 11607 Packaging for terminally sterilized medical devices Package testing is part of a quality management system including verification and validation. It is important to document and ensure that packages meet regulations and end-use requirements. Manufacturing processes must be controlled and validated to ensure consistent performance. EN ISO 15223-1 defines symbols that can be used to convey important information on packaging and labeling.
ASTM E2314: Standard Test Method for Determination of Effectiveness of Cleaning Processes for Reusable Medical Instruments Using a Microbiologic Method (Simulated Use Test)" ASTM D7225: Standard Guide for Blood Cleaning Efficiency of Detergents and Washer-Disinfectors ASTM F3208: Standard Guide for Selecting Test Soils for Validation of Cleaning Methods for Reusable Medical Devices The ASTM F04.15.17 task group is working on several new standards that involve designing implants for cleaning, selection and testing of brushes for cleaning reusable devices, and cleaning assessment of medical devices made by additive manufacturing. Additionally, the FDA is establishing new guidelines for reprocessing reusable medical devices, such as orthoscopic shavers, endoscopes, and suction tubes. New research was published in ACS Applied Interfaces and Material to keep Medical Tools pathogen free.
Medical device manufacturing requires a level of process control according to the classification of the device. Higher risk; more controls. When in the initial R&D phase, manufacturers are now beginning to design for manufacturability. This means products can be more precision-engineered to for production to result in shorter lead times, tighter tolerances and more advanced specifications and prototypes. The arrival of CAD and other modelling platforms accelerated this process, acting both as a tool for strategic design generation and marketing. Failure to meet cost targets will lead to substantial losses for an organisation. In addition, with global competition, the R&D of new devices is not just a necessity, it is an imperative for medical device manufacturers. The realisation of a new design can be very costly, especially with the shorter product life cycle. As technology advances, there is typically a level of quality, safety and reliability that increases exponentially with time. For example, initial models of the artificial cardiac pacemaker were external support devices that transmits pulses of electricity to the heart muscles via electrode leads on the chest. The electrodes contact the heart directly through the chest, allowing stimulation pulses to pass through the body. Recipients of this typically developed an infection at the entrance of the electrodes, which led to the subsequent trial of the first internal pacemaker, with electrodes attached to the myocardium by thoracotomy. Future developments led to the isotope-power source that would last for the lifespan of the patient.
Medical devices such as pacemakers, insulin pumps, operating room monitors, defibrillators, and surgical instruments, including deep-brain stimulators, can incorporate the ability to transmit vital health information from a patient's body to medical professionals. Some of these devices can be remotely controlled. This has engendered concern about privacy and security issues, human error, and technical glitches with this technology. While only a few studies have looked at the susceptibility of medical devices to hacking, there is a risk. In 2008, computer scientists proved that pacemakers and defibrillators can be hacked wirelessly via radio hardware, an antenna, and a personal computer. These researchers showed they could shut down a combination heart defibrillator and pacemaker and reprogram it to deliver potentially lethal shocks or run out its battery. Jay Radcliff, a security researcher interested in the security of medical devices, raised fears about the safety of these devices. He shared his concerns at the Black Hat security conference. Radcliff fears that the devices are vulnerable and has found that a lethal attack is possible against those with insulin pumps and glucose monitors. Some medical device makers downplay the threat from such attacks and argue that the demonstrated attacks have been performed by skilled security researchers and are unlikely to occur in the real world. At the same time, other makers have asked software security experts to investigate the safety of their devices. In June 2011, security experts showed that by using readily available hardware and a user manual, a scientist could tap into the information on the system of a wireless insulin pump in combination with a glucose monitor. With the PIN of the device, the scientist could wirelessly control the dosage of the insulin. Anand Raghunathan, a researcher in this study, explains that medical devices are getting smaller and lighter so that they can be easily worn. The downside is that additional security features would put an extra strain on the battery and size and drive up prices. Dr. William Maisel offered some thoughts on the motivation to engage in this activity. Motivation to do this hacking might include acquisition of private information for financial gain or competitive advantage; damage to a device manufacturer's reputation; sabotage; intent to inflict financial or personal injury or just satisfaction for the attacker. Researchers suggest a few safeguards. One would be to use rolling codes. Another solution is to use a technology called "body-coupled communication" that uses the human skin as a wave guide for wireless communication. On 28 December 2016, the US Food and Drug Administration released its recommendations that are not legally enforceable for how medical device manufacturers should maintain the security of Internet-connected devices. Similar to hazards, cybersecurity threats and vulnerabilities cannot be eliminated but must be managed and reduced to a reasonable level. When designing medical devices, the tier of cybersecurity risk should be determined early in the process in order to establish a cybersecurity vulnerability and management approach (including a set of cybersecurity design controls). The medical device design approach employed should be consistent with the NIST Cybersecurity Framework for managing cybersecurity-related risks. In August 2013, the FDA released over 20 regulations aiming to improve the security of data in medical devices, in response to the growing risks of limited cybersecurity.
2. System Architecture & Core Working Principles The number of approved medical devices using artificial intelligence or machine learning (AI/ML) is increasing. As of 2020, there were several hundred AI/ML medical devices approved by the US FDA or CE-marked devices in Europe. Most AI/ML devices focus upon radiology. As of 2020, there was no specific regulatory pathway for AI/ML-based medical devices in the US or Europe. However, in January 2021, the FDA published a proposed regulatory framework for AI/ML-based software, and the EU medical device regulation which replaces the EU Medical Device Directive in May 2021, defines regulatory requirements for medical devices, including AI/ML software. In January 2025, the FDA published a draft guidance document for AI-enabled medical devices, covering both lifecycle considerations and marketing submissions.
Medical equipment (also known as armamentarium) is designed to aid in the diagnosis, monitoring or treatment of medical conditions. Diagnostic equipment includes medical imaging machines, used to aid in diagnosis. Examples are ultrasound and MRI machines, PET and CT scanners, and x-ray machines. Treatment equipment includes infusion pumps, medical lasers and LASIK surgical machines. Life support equipment is used to maintain a patient's bodily function. This includes medical ventilators, incubators, anaesthetic machines, heart-lung machines, ECMO, and dialysis machines. Medical monitors allow medical staff to measure a patient's medical state. Monitors may measure patient vital signs and other parameters including ECG, EMG, and blood pressure. Medical laboratory equipment automates or helps analyze blood, urine, genes, and dissolved gases in the blood. Diagnostic medical equipment may also be used in the home for certain purposes, e.g. for the control of diabetes mellitus, such as in the case of continuous glucose monitoring. Therapeutic: physical therapy machines like continuous passive range of motion (CPM) machines Air purifying equipment may be used in the periphery of the operating room or at point sources including near the surgical site for the removal of surgical plume. The identification of medical devices has been recently improved by the introduction of Unique Device Identification (UDI) and standardised naming using the Global Medical Device Nomenclature (GMDN) which have been endorsed by the International Medical Device Regulatory Forum (IMDRF). A biomedical equipment technician (BMET) is a vital component of the healthcare delivery system. Employed primarily by hospitals, BMETs are the people responsible for maintaining a facility's medical equipment. BMET mainly act as an interface between doctor and equipment.
Internet of things (IoT) describes physical objects that are embedded with sensors, processing ability, software, and other technologies that connect and exchange data with other devices and systems over the Internet or other communication networks. The field of IoT encompasses electronics, communication, and computer science engineering. "Internet of things" has been considered a misnomer because most devices do not need to be connected to the public Internet; they only need to be connected to a network and be individually addressable. The field has evolved due to the convergence of multiple technologies, including ubiquitous computing, sensors, embedded systems, and machine learning. Traditional fields of embedded systems, wireless sensor networks, control systems, and automation independently and collectively enable the Internet of things. While in the consumer market, IoT technology is most commonly known as smart home products—including devices and appliances like thermostats and smart speakers—the technology's largest applications are in the business and industrial sectors. Commercial asset tracking and fleet management represent the largest single application of IoT, accounting for 22% of the total market, driven by the need to monitor mobile assets like vehicles and shipping containers. The largest asset tracking sub-segments in transport & logistics are trailer and intermodal container tracking, reaching 5.8 million and 5.3 million active devices globally at the end of 2024 respectively. Other major applications include industrial monitoring, smart metering in utilities, and connected healthcare. There are a number of concerns about the risks in the growth of IoT technologies and products, especially in the areas of privacy and security, and consequently there have been industry and government moves to address these concerns adequately and minimize safety risks, including the development and implementation of international and local standards, guidelines, and regulatory frameworks. Due to their interconnected nature, IoT devices are vulnerable to security breaches and privacy concerns. At the same time, the way these devices communicate wirelessly creates regulatory ambiguities, complicating jurisdictional boundaries of the data transfer.
The IoT can assist in the integration of communications, control, and information processing across various transportation systems. Application of the IoT extends to all aspects of transportation systems (i.e., the vehicle, the infrastructure, and the driver or user). Dynamic interaction between these components of a transport system enables inter- and intra-vehicular communication, smart traffic control, smart parking, electronic toll collection systems, logistics and fleet management, vehicle control, safety, and road assistance. In vehicle security applications, IoT-connected GPS trackers can operate for months or years on internal batteries, using low-power wide-area network protocols such as LTE-M to transmit location data to owners via smartphone applications when unauthorized movement is detected.
In vehicular communication systems, vehicle-to-everything communication (V2X), consists of three main components: vehicle-to-vehicle communication (V2V), vehicle-to-infrastructure communication (V2I), and vehicle-to-pedestrian communication (V2P). Eventually, V2X is the first step to autonomous driving and connected road infrastructure.
IoT devices can be used to monitor and control the mechanical, electrical, and electronic systems used in various types of buildings (e.g., public and private, industrial, institutions, or residential) in home automation and building automation systems. In this context, three main areas are being covered in the literature: The integration of the Internet with building energy management systems to create energy-efficient and IOT-driven "smart buildings". The possible means of real-time monitoring for reducing energy consumption and monitoring occupant behaviors.
The integration of smart devices in the built environment and how they might be used in future applications. Also known as IIoT, industrial IoT devices acquire and analyze data from connected equipment, operational technology (OT), locations, and people. Combined with operational technology (OT) monitoring devices, IIoT helps regulate and monitor industrial systems. Additionally, the same implementation can be carried out for automated record updates of asset placement in industrial storage units as the size of the assets can vary from a small screw to the whole motor spare part, and misplacement of such assets can cause a loss of manpower time and money.
The Internet of Military Things (IoMT) is the application of IoT technologies in the military domain for the purposes of reconnaissance, surveillance, and other combat-related objectives. It is heavily influenced by the future prospects of warfare in an urban environment and involves the use of sensors, munitions, vehicles, robots, human-wearable biometrics, and other smart technology that is relevant on the battlefield. One of the examples of IOT devices used in the military is the Xaver 1000 system. The Xaver 1000 was developed by Israel's Camero Tech, which is the latest in the company's line of "through-wall imaging systems." The Xaver line uses millimeter wave (MMW) radar, or radar in the range of 30-300 gigahertz. It is equipped with an AI-based life target tracking system as well as its own 3D 'sense-through-the-wall' technology.
IoT system architecture, in its simplistic view, consists of three tiers: Tier 1: Devices, Tier 2: the Edge Gateway, and Tier 3: the Cloud. Devices include networked things, such as the sensors and actuators found in IoT equipment, particularly those that use protocols such as Modbus, Bluetooth, Zigbee, or proprietary protocols, to connect to an Edge Gateway. The Edge Gateway layer consists of sensor data aggregation systems called Edge Gateways that provide functionality, such as pre-processing of the data, securing connectivity to cloud, using systems such as WebSockets, the event hub, and, even in some cases, edge analytics or fog computing. Edge Gateway layer is also required to give a common view of the devices to the upper layers to facilitate in easier management. The final tier includes the cloud application built for IoT using the microservices architecture, which are usually polyglot and inherently secure in nature using HTTPS/OAuth. It includes various database systems that store sensor data, such as time series databases or asset stores using backend data storage systems (e.g. Cassandra, PostgreSQL). The cloud tier in most cloud-based IoT system features event queuing and messaging system that handles communication that transpires in all tiers. Some experts classified the three-tiers in the IoT system as edge, platform, and enterprise and these are connected by proximity network, access network, and service network, respectively.
Different technologies have different roles in a protocol stack. Below is a simplified presentation of the roles of several popular communication technologies in IoT applications: Data security – At the time of designing IoT companies should ensure that data collection, storage and processing would be secure at all times. Companies should adopt a "defense in depth" approach and encrypt data at each stage. Data consent – users should have a choice as to what data they share with IoT companies and the users must be informed if their data gets exposed. Data minimisation – IoT companies should collect only the data they need and retain the collected information only for a limited time. However, the FTC stopped at just making recommendations for now. According to an FTC analysis, the existing framework, consisting of the FTC Act, the Fair Credit Reporting Act, and the Children's Online Privacy Protection Act, along with developing consumer education and business guidance, participation in multi-stakeholder efforts and advocacy to other agencies at the federal, state and local level, is sufficient to protect consumer rights. A resolution passed by the Senate in March 2015, is already being considered by the Congress. This resolution recognized the need for formulating a National Policy on IoT and the matter of privacy, security and spectrum. Furthermore, to provide an impetus to the IoT ecosystem, in March 2016, a bipartisan group of four Senators proposed a bill, The Developing Innovation and Growing the Internet of Things (DIGIT) Act, to direct the Federal Communications Commission to assess the need for more spectrum to connect IoT devices. Approved on 28 September 2018, California Senate Bill No. 327 goes into effect on 1 January 2020. The bill requires "a manufacturer of a connected device, as those terms are defined, to equip the device with a reasonable security feature or features that are appropriate to the nature and function of the device, appropriate to the information it may collect, contain, or transmit, and designed to protect the device and any information contained therein from unauthorized access, destruction, use, modification, or disclosure," Several standards for the IoT industry are actually being established relating to automobiles because most concerns arising from use of connected cars apply to healthcare devices as well. In fact, the National Highway Traffic Safety Administration (NHTSA) is preparing cybersecurity guidelines and a database of best practices to make automotive computer systems more secure. A recent report from the World Bank examines the challenges and opportunities in government adoption of IoT. These include – Still early days for the IoT in government Underdeveloped policy and regulatory frameworks Unclear business models, despite a strong value proposition Clear institutional and capacity gap in government AND the private sector Inconsistent data valuation and management Infrastructure a major barrier Government as an enabler Most successful pilots share common characteristics (public-private partnership, local, leadership) In early December 2021, the U.K. government introduced the Product Security and Telecommunications Infrastructure bill (PST), an effort to legislate IoT distributors, manufacturers, and importers to meet certain cybersecurity standards. The bill also seeks to improve the security credentials of consumer IoT devices.
A study issued by Ericsson regarding the adoption of Internet of things among Danish companies identified a "clash between IoT and companies' traditional governance structures, as IoT still presents both uncertainties and a lack of historical precedence." Among the respondents interviewed, 60 percent stated that they "do not believe they have the organizational capabilities, and three of four do not believe they have the processes needed, to capture the IoT opportunity." This has led to a need to understand organizational culture in order to facilitate organizational design processes and to test new innovation management practices. A lack of digital leadership in the age of digital transformation has also stifled innovation and IoT adoption to a degree that many companies, in the face of uncertainty, "were waiting for the market dynamics to play out", or further action in regards to IoT "was pending competitor moves, customer pull, or regulatory requirements". Some of these companies risk being "kodaked" – "Kodak was a market leader until digital disruption eclipsed film photography with digital photos" – failing to "see the disruptive forces affecting their industry" and "to truly embrace the new business models the disruptive change opens up". Scott Anthony has written in Harvard Business Review that Kodak "created a digital camera, invested in the technology, and even understood that photos would be shared online" but ultimately failed to realize that "online photo sharing was the new business, not just a way to expand the printing business." A separate research and development phase A Proof-of-Concept/Prototype before the actual project begins Project managers with interdisciplinary technical knowledge Universally defined business and technical jargon Acharjya, D.P.; Geetha, M.K., eds. (2017). Internet of Things: Novel Advances and Envisioned Applications. Springer. p. 311.
978-0-12-804505-3. Rowland, C.; Goodman, E.; Charlier, M.; et al., eds. (2015). Designing Connected Products: UX for the Industrial Internet Application Development: Simplify IIoT development using the elasticity of Public Cloud and Native Cloud 978-0-8144-3977-7. Due to the many regulations in the industry, the design of medical devices presents significant challenges from both engineering and legal perspectives.
Medical devices are defined by the US Food and Drug Administration (FDA) as any object or component used in diagnosis, treatment, prevention, or cure of medical conditions or diseases, or affects body structure or function through means other than chemical or metabolic reaction in humans or animals. This includes all medical tools, excluding drugs, ranging from tongue depressors to Computerized Axial Tomography (CAT) scanners to radiology treatments. Because of the wide variety of equipment classified as medical devices, the FDA has no single standard to which a specific device must be manufactured; instead they have created an encompassing guide that all manufacturers must follow. Manufacturers are required to develop comprehensive procedures within the FDA framework in order to produce a specific device to approved safety standards.
Class II Class II are devices with moderate risk. Class I and Class II devices are subject to less stringent regulatory processes than Class III devices. Class I or II devices are focused on registration, manufacturing, and labeling. In general they do not require clinical data. Most class II devices go through a pre-market notification (PMN) process (a 510[k] clearance). The PMN will not require stringent clinical trial evidence.
Class III Class III are devices which support or sustain human life, are of substantial importance in preventing impairment of human health, or present a potential, unreasonable risk of illness or injury. All new devices by default are placed in the class III category. The FDA then requires these devices to undergo stringent clinical reviews. For these reviews, the FDA require some type of clinical evidence or trials. If the sponsor believes the device is low to moderate risk, the sponsor may apply to change this default classification. The FDA, upon review may then reclassify these devices as de novo. De novo devices require a less rigorous FDA regulatory process and the FDA treats de novo devices like class I and II devices.
3. Software Implementation, Frameworks & Protocols Class III devices with predicates Class III devices with predicates (devices with a substantially equivalent device already on the market) are reclassified as class I or II devices. This is done through a 513(g) pathway. Class III devices reclassified as a class I or II, are then subject to less stringent testing requirements. As reclassified class II devices they would require a PMN (510[k]) process, not the PMA process.
adulteration misbranding device registration and listing premarket notification banned devices notification, including repair, replacement, or refund records and reports restricted devices good manufacturing practices Class I: General Controls Class II: General Controls and Special Controls Class III: General Controls and Premarket Approval Regulations differ by class based on their complexity or the potential hazards in the event of malfunction. Class I devices are the least likely to cause major bodily harm or death in the event of failure, and are subjected to less stringent regulations than devices categorized as Class II or Class III. In the regulation process, 2021 statistics showed: 47% of devices were class I, 43% were class II and 10% were class III.
For use in supporting or sustaining life; Of substantial importance in preventing impairment to human life or health; and May not present an unreasonable risk of illness or injury. Most Class I devices are exempt from premarket notification and a few are also exempted from most good manufacturing practices regulations. Examples of Class I devices include hand-held surgical instruments, (elastic) bandages, examination gloves, bed-patient monitoring systems, medical disposable bedding, and some prosthetics such as hearing aids.
Many medical devices have either been successfully attacked or had potentially deadly vulnerabilities demonstrated, including both in-hospital diagnostic equipment and implanted devices including pacemakers and insulin pumps. On 28 December 2016 the US Food and Drug Administration released its recommendations that are not legally enforceable for how medical device manufacturers should maintain the security of Internet-connected devices.
Medical Device Cybersecurity is the discipline of designing, building, deploying and maintaining networked and software-enabled medical devices so that they preserve safety, effectiveness and data protection across their entire life cycle. Unlike general enterprise IT security, medical device security must reconcile clinical safety (a device must not harm a patient), regulatory compliance (a device must clear market authorisation) and operational resilience (a device must keep working in a hospital that cannot be patched on demand). This guide provides an auditor-grade, implementer-ready deep-dive spanning the two dominant regulatory and standards pillars: the U.S. Food and Drug Admi nist ration (FDA) premarket and postmarket cybersecurity expectations, and the IEC 81001-5-1 / IEC/TR 60601-4-5 / AAMI TIR57 / UL 2900-2-1 standards ecosystem, all anchored to a Total Product Life Cycle (TPLC) and Secure Product Development Framework (SPDF) philosophy.
The scope covers Software as a Medical Device (SaMD), Software in a Medical Device (SiMD), connected diagnostic and therapeutic devices, implantables, wearables, hospital gateways and the supporting infrastructure. The guide is written for two audiences at once: the assessor/auditor who must gather objective evidence and render a finding, and the manufacturer/product team who must engineer, document and sustain the controls that produce that evidence.
A defining characteristic of this domain is asymmetry of tempo. Enterprise IT patches on a weekly or monthly cadence; a medical device may be validated for a specific software configuration, deployed for ten to fifteen years, and legally frozen against unvalidated change. This means that security must be engineered in at design time, because the opportunity to retrofit is severely constrained once a device reaches the bedside. It also means that manufacturers and healthcare delivery organisations must share responsibility explicitly: the manufacturer builds intrinsic controls and a safe update path, while the hospital provides compensating network controls, monitoring and physical protection. The documentation that records this shared-responsibility boundary — often expressed through the MDS2 disclosure and the security use instructions — is itself a first-class audit artefact. Assessors who ignore it will misattribute residual risk and reach an unsound conclusion.
The reader should treat this guide as a lattice rather than a linear checklist. Section 4 defines the domains; Section 5 enumerates every control group with a verify/evidence pairing; Sections 6 through 12 wrap those controls in scoping, implementation phasing, maturity grading, audit method, evidence collection, role assignment and measurement. The concluding sections give a readiness checklist, catalogue the failure modes we most frequently observe in the field, and map the scheme to adjacent frameworks so that an organisation already certified to ISO/IEC 27001 or conformant to IEC 62443 can reuse evidence rather than duplicate effort.
Medical Device Security is the application of cybersecurity engineering and governance to devices whose intended use is diagnosis, cure, mitigation, treatment or prevention of disease. It differs materially from IT and OT security because the primary asset under protection is the patient and the clinical outcome, not merely data confidentiality. A ransomware event on a patient-monitoring gateway is a patient-safety event, not only a data-availability event; a firmware flaw in an insulin pump is a potential loss of life. Consequently the field fuses three engineering disciplines: safety risk management (ISO 14971), software life-cycle management (IEC 62304) and security risk management (IEC 81001-5-1 / AAMI TIR57).
The regulatory centre of gravity in the United States is Section 524B of the Federal Food, Drug, and Cosmetic Act (added by the Consolidated Appropriations Act, 2023), which makes cybersecurity a mandatory condition of premarket submission for 'cyber devices'. FDA operationalises this through its premarket cybersecurity guidance (final September 2023), which requires a Secure Product Development Framework, a Software Bill of Materials (SBOM), threat modelling, security architecture views and a plan to monitor, identify and address postmarket vulnerabilities. The international standards centre of gravity is IEC 81001-5-1 (health software and health IT systems safety, effectiveness and security — security activities in the product life cycle), harmonised in the EU under the Medical Device Regulation (MDR 2017/745) and the NIS2 / Radio Equipment Directive (RED) cybersecurity essential requirements.
It is worth naming the specific engineering constructs the scheme expects, because vague conformity claims fail review. The FDA package expects an explicit threat model methodology (STRIDE or attack-tree based), four named architecture views (global system, multi-patient harm, updateability/patchability, and security use case), a machine-readable SBOM in SPDX or CycloneDX format carrying the CISA minimum elements, and a postmarket plan whose remediation clock starts when an uncontrolled risk is identified. IEC 81001-5-1 in turn defines a set of security-activity processes — planning, requirements, design, implementation, verification, release, and problem resolution — that mirror IEC 62304 but add security-specific expectations. Where independent testing or certification is pursued, schemes such as UL 2900-2-1 define structured penetration and known-vulnerability testing, IEC 62443-4-1 (via the ISASecure programme) defines a graded secure-development-lifecycle assurance, and Common Criteria defines Evaluation Assurance Levels (EAL 1 to EAL 7).
Cryptographic modules are frequently validated to FIPS 140-3, which itself defines four security levels of increasing physical and logical protection. Assessors should always establish which of these named levels and constructs a manufacturer is claiming, because the level is what makes a claim testable. Obligations attach to any organisation that manufactures, integrates, distributes, or operates connected or software-enabled medical devices. The concept of a 'cyber device' under Section 524B is broad: any device that (a) includes software validated, installed, or authorised by the sponsor, (b) has the ability to connect to the internet, and (c) contains technological characteristics that could be vulnerable to cybersecurity threats.
Medical Device Security is not a single monolithic control set; it is a lattice of overlapping frameworks that together define premarket engineering expectations, testing/certification schemes and postmarket operations. The table below maps the principal domains, the standard or scheme that owns each, and the representative control families within it. These domains form the backbone of the master assessment checklist in Section 5.
This is the operational heart of the guide. Every control group below is expressed as an h3 with a table whose columns are 'What to verify' (the assessor's test) and 'Typical evidence' (the objective artefact that satisfies it). No domain from Section 4 is omitted. Assessors should sample across the TPLC — do not accept a design document without evidence that its controls were verified in the built device and are sustained in the field.
5.6 Design Security Capabilities — Authentication and Authorisation (IEC/TR 60601-4-5 / IEC 62443-4-2) 5.12 Postmarket Vulnerability and Incident Management (FDA 2016 / ISO/IEC 30111 / 29147) 5.14 Certification and Conformity Assessment (UL 2900-2-1 / ISASecure / Common Criteria) Where a manufacturer claims a graded assurance level, the assessor must verify the claim against the scheme's defined scale. The table below consolidates the principal named levels an auditor encounters in medical device security so that the claimed level, the awarding scheme, and its meaning are unambiguous.
Certification and independent testing follow a defined lifecycle that runs in parallel with, and feeds, the regulatory submission. Auditors should confirm each stage produced its expected artefact and that the certificate remains valid and in scope. Scoping determines what is assessed and to what depth. For medical device security the boundary is the 'device system' as intended and labelled — including firmware, embedded OS, application software, companion mobile apps, cloud back-ends, gateways, accessories and the interfaces between them. Scoping must be driven by intended use and by where cybersecurity failures could translate into patient harm.
4. Practical Deployment, Analysis & Case Studies A disciplined scoping exercise begins from the intended use statement and the essential performance defined for the device, then works outward along every path by which data or control can enter or leave the system. Each such path is an entry point and therefore part of the attack surface. The scope boundary should be drawn to include everything the manufacturer controls or can influence, and to explicitly exclude — with written rationale — anything transferred to the operating environment. A common scoping error is to evaluate the physical device while excluding its cloud analytics back-end; because a compromise of a shared back-end can affect every deployed unit simultaneously, that back-end almost always belongs inside the multi-patient harm view and therefore inside scope. Equally, wireless interfaces are frequently under-scoped: Bluetooth Low Energy pairing, Wi-Fi association and cellular management channels each carry their own threat surface and each must be enumerated.
Implementation follows a phased Secure Product Development Framework mapped to the Total Product Life Cycle. Each phase below lists key activities and the deliverables an auditor should expect. A maturity model helps both manufacturers and auditors calibrate where a product security programme sits and what 'good' looks like. The five-level model below is adapted from common capability-maturity constructs and aligned to IEC 81001-5-1 and SPDF expectations. Regulatory conformity is achievable at Level 3, where the SPDF is defined and consistently applied across the Total Product Life Cycle; Levels 4 and 5 add the quantitative management and continuous-improvement characteristics that distinguish a resilient, defensible programme from a merely compliant one. Auditors should score each control group in Section 5 independently, because a programme is often mature in design but immature in postmarket operation, or vice versa; the overall rating is only as strong as its weakest safety-relevant domain.
The following artefacts, grouped by category, constitute a typical evidence pack for a medical device security assessment. Checklists, evidence registers and policy templates our auditors actually use on engagements. CERT-In empanelled, PCI QSA senior auditors can take you from reading about it to compliant — with a scoped, guided programme.
An effective medical device security program must consider the Medical Equipment Lifecycle (MELC). MELC divides medical device management into four parts. Each part needs special security actions: Before buying a new device, healthcare managers and IT staff must do careful risk checks. They should look at: The FDA will ask manufacturers to share SBOMs from 2023, giving healthcare places better knowledge of software parts and making risk checks more accurate.
Since more than half of hospital IoMT devices had serious security problems in a 2022 report, these early checks are very important. They help keep unsafe devices out of healthcare networks. After buying devices, putting them to use is another chance for risks to enter. IT teams should: Working with IoMT cybersecurity experts can help set up secure deployments. For example, some big health systems use platforms that watch connected devices all the time. They find problems like strange network traffic quickly.
Deployment can be hard because devices are complex and many types exist. But it is a key step for device security. Security teams need tools that send real-time alerts about device health. Continuous monitoring is important because over half of hospital IoMT devices show critical risks. It is not safe to check them only sometimes. Old devices can cause the biggest security problems if they stay connected after they are done being used. These devices might not get security updates and can be attacked.
Failing to remove devices right can cause data leaks, service stops, or harm patients. Working with device makers and security experts helps a lot during this step. Well-trained workers make fewer mistakes and reduce inside risks that might break device security. Constant education helps staff stay up-to-date on new threats and rules.
New artificial intelligence (AI) and automation can help improve device security. AI software can study huge amounts of device data, network traffic, and security reports faster than people. AI tools help reduce workload and improve accuracy in managing device security. As devices get more complex, using AI is a good step for healthcare groups across the U.S.
Protecting medical devices needs teamwork. Healthcare groups cannot do it alone. Working together with: One example is a partnership of a large hospital and a cybersecurity provider. They shared data and found strange network activity linked to patient monitors. This helped fix problems quickly and keep devices working well and patients safe. 5. Performance Evaluation & Extended Technical Observations Healthcare managers should keep open communication with manufacturers and security experts to manage risks fully.
Hospitals and clinics can lower cyber risks by following these steps carefully. This will help keep patients safe and meet federal rules. Healthcare organizations in the U.S. face big risks from unsecured medical devices. But following the Medical Equipment Lifecycle can reduce these risks well. By doing good risk checks, securing networks, monitoring devices, training staff, retiring devices properly, and using AI while working closely with manufacturers and security experts, healthcare leaders can protect patients, data, and systems effectively.
The Medical Equipment Lifecycle (MELC) is a framework for managing medical devices from initial purchase through maintenance to eventual disposal. It helps maintain device integrity throughout its lifetime and is essential for ensuring cybersecurity in the Internet of Medical Things (IoMT). The four stages are: 1) Pre-Procurement, involving risk assessments; 2) Deployment, focusing on securing network-connected devices; 3) Operation, managing device vulnerabilities; and 4) Decommissioning, ensuring legacy devices are secured before disposal.
Manufacturers are responsible for designing and testing medical devices to comply with security standards. They must provide ongoing support, including addressing new risks and releasing necessary upgrades or patches to secure devices post-release. HDOs must create secure networks, conduct regular vulnerability scans, and manage updates efficiently. Implementing strict access controls and ensuring collaboration with manufacturers and IoMT cybersecurity providers are crucial for maintaining security.
HDOs often struggle when manufacturers do not release timely patches for vulnerabilities. Budget constraints and the complexity of decommissioning outdated devices can also hinder effective risk management and security efforts. Collaborative efforts between manufacturers, HDOs, and IoMT cybersecurity providers facilitate better risk management, enhance communication about vulnerabilities, and lead to more comprehensive security measures across the Medical Equipment Lifecycle.
Steps include: 1) Conducting comprehensive risk assessments; 2) Implementing access controls; 3) Regularly monitoring devices for anomalies; 4) Keeping devices updated with security patches; and 5) Establishing ongoing security training programs for staff. MDS2s provide essential information on securing medical device components, while SBOMs list all software installed on a device. Both are crucial for managing vulnerabilities and ensuring devices remain secure over time.
IoMT cybersecurity providers help assess risk levels, identify security gaps, and provide strategies for risk management. They can handle the monitoring and operational aspects of medical device security throughout the equipment lifecycle. One example is a health system with patient monitor issues. Collaboration with Asimily revealed abnormal network traffic, allowing for corrective action. The partnership enhanced the system’s security posture and improved device functionality.
Smarter, Chearper, and Faster AI Answering Service. Set up and go live within minutes. Generative AI: Transforming Administrative Efficiency in Healthcare Through Automation and Streamlined Processes Designing and Implementing Multi-Agent AI Systems for Scalable, Interoperable, and Efficient Healthcare Service Delivery and Clinical Data Management The Ethical Implications of Diverse Voice Technologies in Healthcare: Addressing Privacy and Racial Profiling Concerns Simbo is using AI agents to automate all phone related workflows. Connect now to know more.
A medical device cybersecurity risk assessment is no longer a documentation exercise that supports a submission — it is now a condition of market access. Since the FDA’s authority under Section 524B of the FD&C Act became effective on 29 March 2023, and with the final premarket cybersecurity guidance issued in June 2025 and terminology aligned to the QMSR in February 2026, a “cyber device” submission that lacks an adequate threat model, security risk assessment or Software Bill of Materials can be refused outright. In the EU, the same expectation arrives through EU MDR Annex I and the MDCG 2019-16 guidance. This guide explains how to perform a medical device cybersecurity risk assessment that satisfies both regimes: scoping and asset identification, data flow diagrams, STRIDE threat modeling, risk estimation, control mapping, and how the whole thing connects to your ISO 14971 safety risk file.
It is written for quality, regulatory and security professionals who already operate a quality management system and need the cybersecurity risk assessment to be submission-proof rather than merely present. It completes the cybersecurity cluster alongside our IEC 81001-5-1 cybersecurity guide and our medical device cybersecurity testing article, and it depends throughout on the safety risk framework described in our ISO 14971 risk management guide.
For years cybersecurity in medical devices was treated as advisory — a section auditors might probe but rarely blocked a submission over. That era has ended. The FDA’s June 2025 final guidance, Cybersecurity in Medical Devices: Quality System Considerations and Content of Premarket Submissions , operationalises Section 524B and makes cybersecurity an independent regulatory standard: a device with unresolved cybersecurity risk can be considered to lack a reasonable assurance of safety and effectiveness on cybersecurity grounds alone. Both the FDA and EU Notified Bodies now reject submissions for cybersecurity shortcomings — a missing SBOM, an inadequate threat model, or absent post-market surveillance planning — independently of any other deficiency.
Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/Medical%20device • https://en.wikipedia.org/wiki/Internet%20of%20things • https://en.wikipedia.org/wiki/Medical%20device%20design • https://cybersigmacs.com/knowledge-center/medical-device-cybersecurity/ • https://www.simbo.ai/blog/implementing-an-effective-medical-device-security-program-step-by-step-guide-for-healthcare-faci lities-344216/ • https://mdregulatory.com/medical-device-cybersecurity-risk-assessment/
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.

Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Medical Device Security Monitoring System For Hospitals.
[*] Metasploit Scan Running on Target Subnet for Medical Device Security Monitoring System For Hospitals... [✓] SafeBreach / AttackIQ Continuous Exposure Agent Triggered ──────────────────────────────────────────────────────────────────────── [11:48:02.104] PICUS Threat Scenario Dispatched: Lateral Movement SMB Probe [11:48:02.185] BLOCKED Endpoint EDR Detected Technique | Packet Tracer ACL Denied [11:48:02.240] CYMULATE Prevention Rate = 96.8% | SIEM Latency = 38 ms [11:48:02.312] ATTACKIQ Posture Validation: MITRE ATT&CK matrix fully validated ──────────────────────────────────────────────────────────────────────── [✓] BAS Simulation Run Complete: Defense-in-Depth Verified Across All Controls
| Simulation Platform | Simulated Threat / Scenario | Target Subsystem | Detection Latency | Security Control Status |
|---|---|---|---|---|
| Metasploit Framework | Port Reconnaissance & Fingerprinting | DMZ Gateway | 18 ms | MONITORED & DROPPED |
| AttackIQ Enterprise | Credential Access (LSASS Dump) | Windows Client | 42 ms | BLOCKED BY EDR |
| SafeBreach | Ransomware Lateral Movement | File Server Subnet | 65 ms | ISOLATED IN SANDBOX |
| Cymulate | Email Gateway Malicious Attachment | Corporate Mailbox | 120 ms | QUARANTINED |
| Picus Security | Command & Control (C2) Beaconing | Edge Firewall | 24 ms | BLOCKED BY ACL |