Complete Technical Paper Content — Secure Electronic Medical Prescription
Overview & System Context
Secure Electronic Medical Prescription: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~9526 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background A prescription in the medical context, often abbreviated as I or Rx in North America, is a formal communication from physicians or other registered healthcare professionals to a pharmacist, authorizing them to dispense a specific prescription drug for a specific patient. Historically, it was a physician's instruction to an apothecary listing the materials to be compounded into a treatment—the symbol I (a capital letter R, crossed to indicate abbreviation) comes from the first word of a medieval prescription, Latin recipe (lit. 'you take'), that gave the list of the materials to be compounded. Requirements for content, who may prescribe, and how prescriptions are transmitted vary by country; many jurisdictions use electronic prescribing systems.
In law, a prescription in the medical context is a written or electronic order for a medicinal product or medical device issued by a health professional—such as a physician, physician assistant, dentist, or veterinarian—who is legally entitled to prescribe within the jurisdiction where it is issued. In pharmacy usage, the term prescription generally refers to instructions for medicines that patients obtain from a pharmacy or doctor's office and take themselves outside the hospital. This contrasts with medication orders, which are recorded in hospital or institutional charts to guide nurses and other staff in administering medicines directly to inpatients. Prescriptions may be issued on paper, electronically, or, where it is permitted, verbally (e.g., by telephone). Paper prescriptions normally require the prescriber's handwritten signature and the date of issue. In some jurisdictions, a digital signature may be accepted, while prescriptions for controlled drugs often carry additional legal requirements, such as a handwritten signature, specified wording, or security features. Electronic prescriptions are accepted in many jurisdictions, and verbal prescriptions, when accepted, are subject to restrictions and read-back procedures to reduce error. The content of a prescription includes the name and address of the prescribing provider and any other legal requirements, such as a registration number (e.g., a DEA number in the United States). Unique to each prescription is the name of the patient. In the United Kingdom and Ireland, the patient's name and address must also be recorded. Each prescription is dated, and some jurisdictions may place a time limit on the prescription. Due to the addictive properties of certain drugs, incidents where security hackers have compromised online prescription accounts and employees have forged paper scripts to be sold on the black market have occurred. In the past, prescriptions contained instructions for the pharmacist to use for compounding the pharmaceutical product, but most prescriptions now specify pharmaceutical products that were manufactured and require little or no preparation by the pharmacist. Prescriptions also contain directions for the patient to follow when taking the drug. These directions are printed on the label of the pharmaceutical product. The word prescription, from pre- ('before') and script ('writing, written'), refers to the fact that the prescription is an order that must be written down before a drug can be dispensed. Those within the industry will often call prescriptions simply "scripts". The symbol "I", sometimes transliterated as "Rx" or "Rx", is recorded in 16th century manuscripts as an abbreviation of the late Latin instruction recipe, meaning 'receive'. Originally abbreviated Rc, the later convention of using a slash to indicate abbreviation resulted in an R with a straight stroke through its right "leg". Medieval prescriptions invariably began with the instruction from the physician to the apothecary to "take" certain materials and compound them in specified ways.
Every prescription contains who prescribed the prescription, who the prescription is valid for, and what is prescribed. Some jurisdictions, drug types or patient groups require additional information as explained below. Dose size Dosing interval Duration of therapy Route of administration Selection of an appropriate dose regimen is important for achieving therapeutic benefit. Incorrect dosing schedules may lead to treatment failure or drug toxicity, especially for medicines with a narrow therapeutic index.
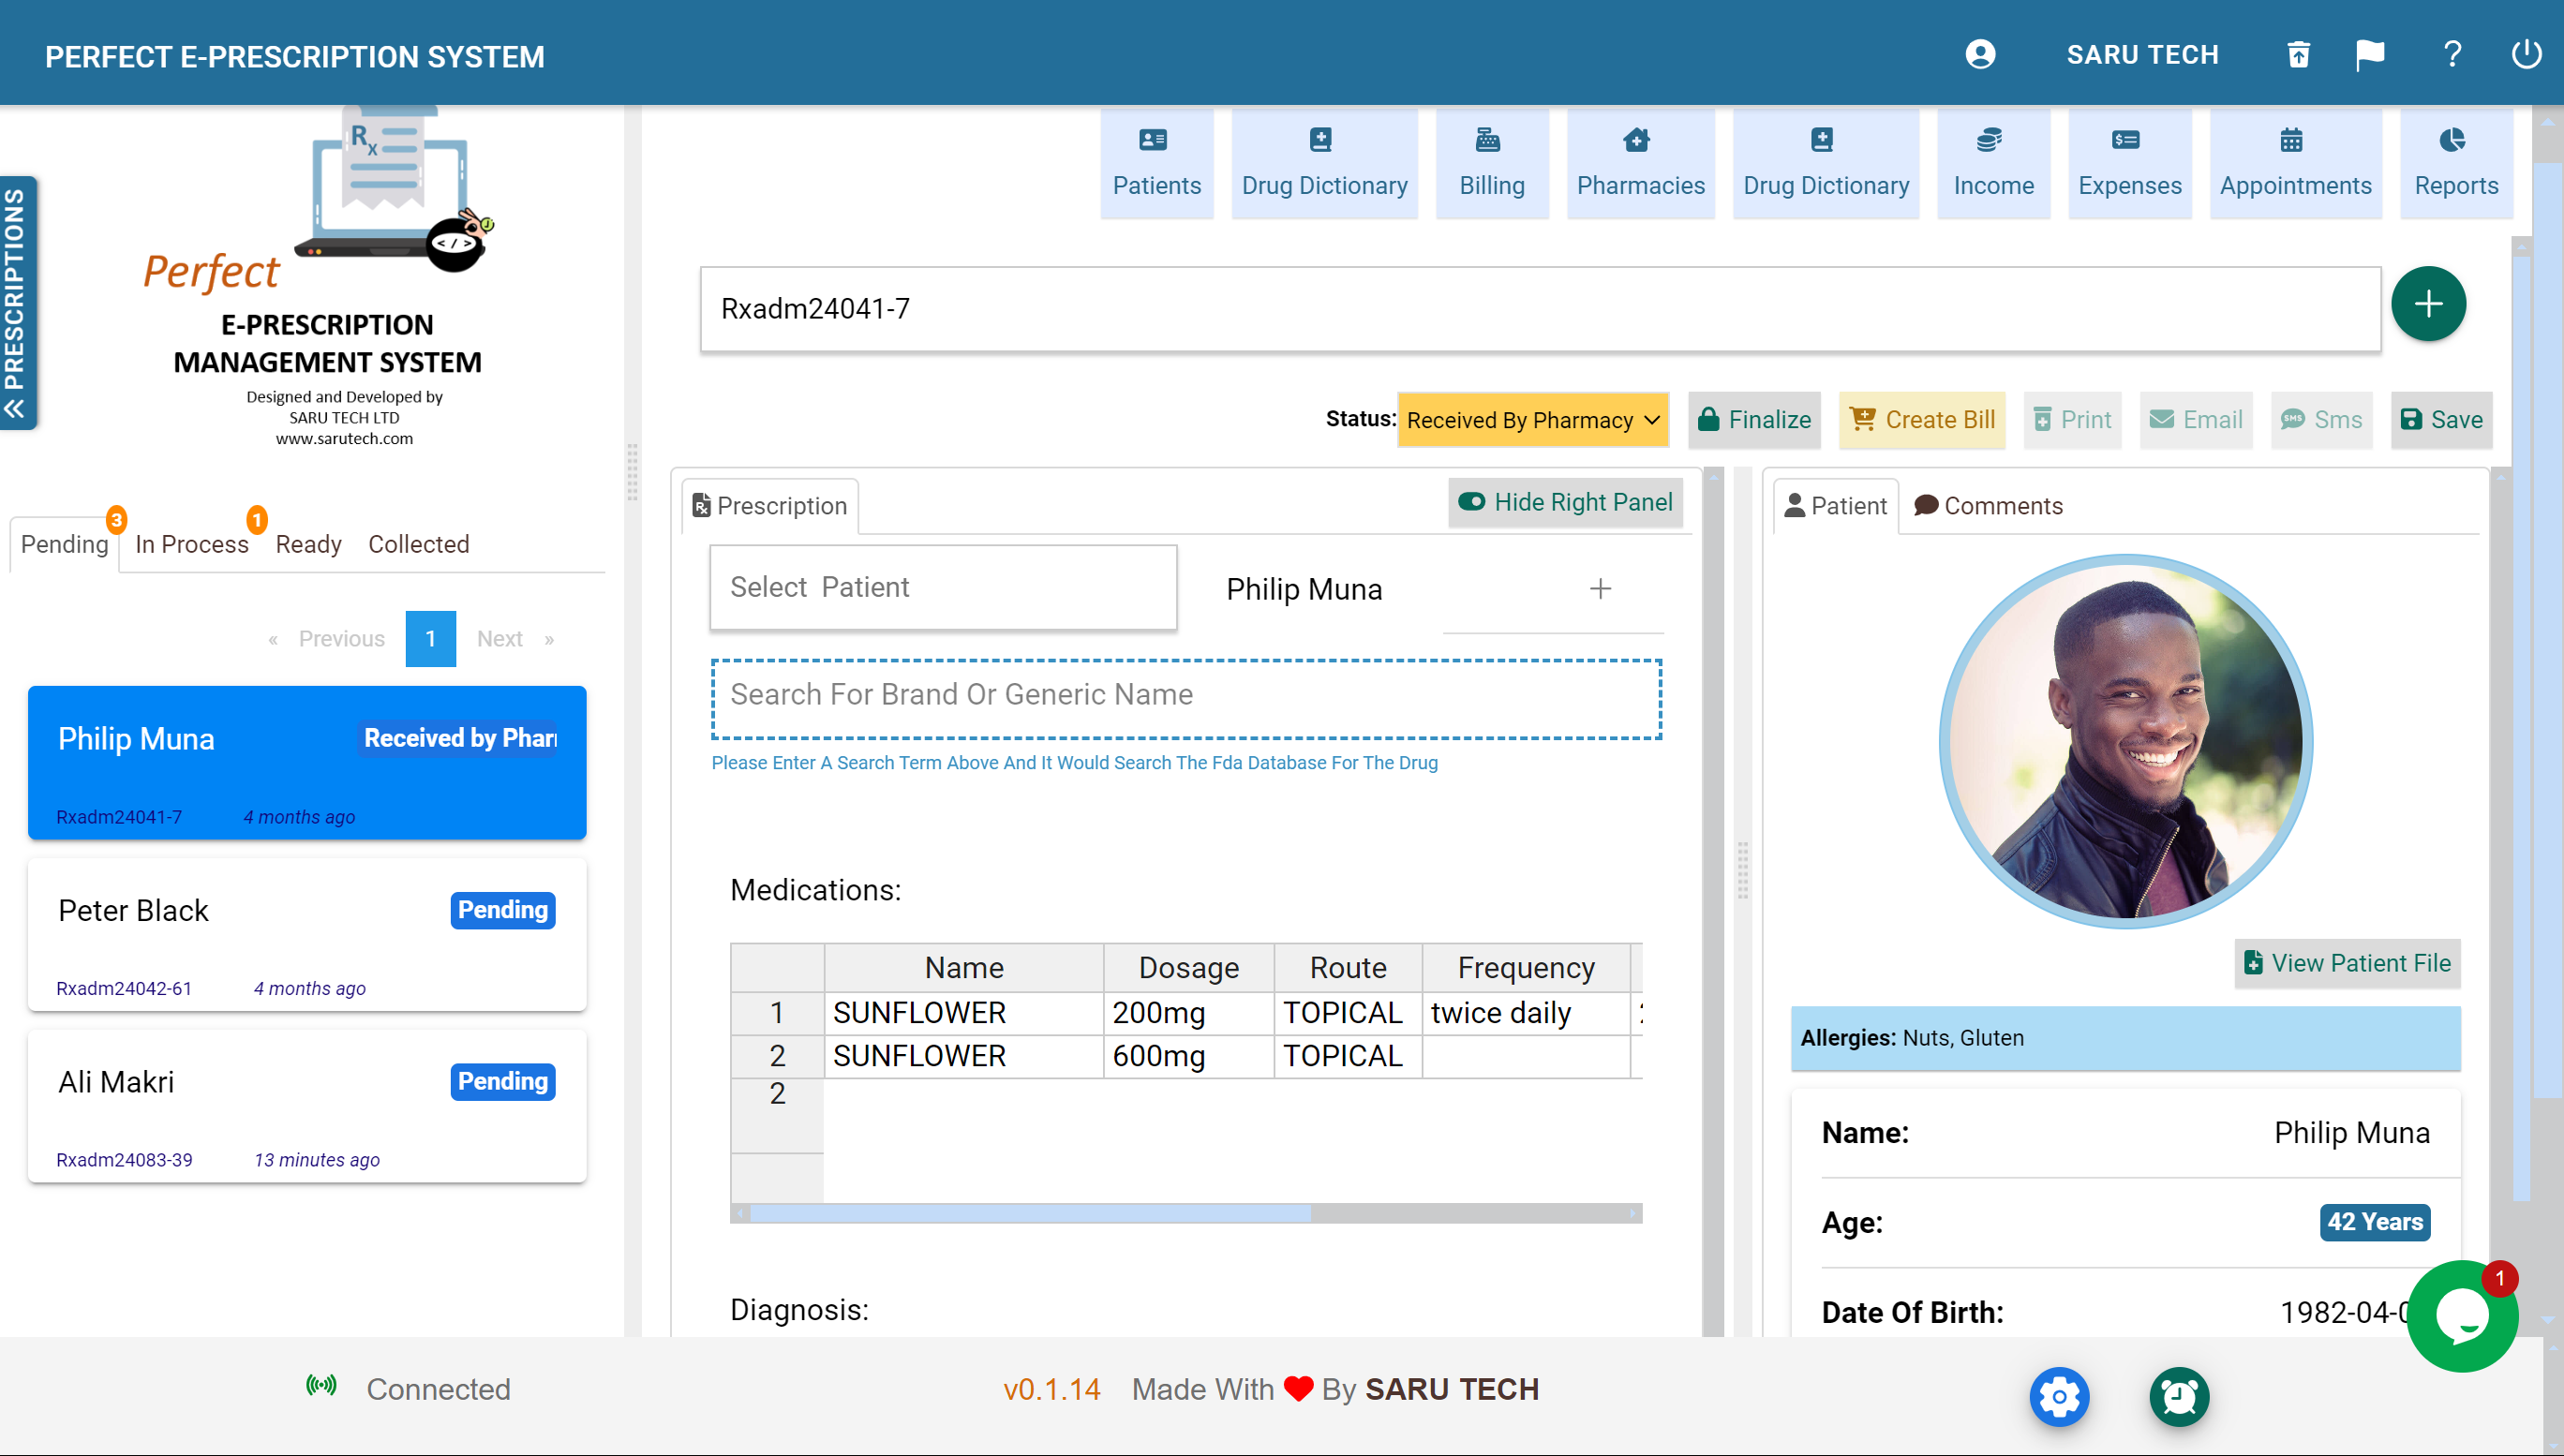
Figure 1: Digital Prescription Software with AI Dosage Verification | Perfect E ... Careful use of decimal points to avoid ambiguity: Avoiding unnecessary decimal points and trailing zeros, e.g. 5 mL rather than 5.0 mL. Always using leading zeros on decimal numbers less than 1: e.g. 0.5 rather than .5 to avoid misinterpretation as 5. Directions written out in full in English (although some common Latin abbreviations are listed below). Quantities given directly or implied by the frequency and duration of the directions. Where the directions are "as needed", the quantity should always be specified. Where possible, usage directions should specify times (7 am, 3 pm, 11 pm) rather than simply frequency (three times a day) and especially relationship to meals for orally consumed medication. The use of permanent ink is encouraged. Avoiding units such as "teaspoons" or "tablespoons". Writing out numbers as words and numerals ("dispense #30 (thirty)") as in a bank draft or cheque. The use of the apothecaries' system or avoirdupois units and symbols of measure – pints (O), ounces (I), drams (I), scruples (I), grains (gr), and minims (II) – is discouraged given the potential for confusion.
For example, the abbreviation for a grain ("gr") can be confused with the gram, abbreviated g, and the symbol for minims (II), which looks almost identical to an "m", can be confused with micrograms or metres. Also, the symbols for ounce (I) and dram (I) can easily be confused with the numeral "3" and the Latin letter ezh, "I" and the symbol for pint (O) can be easily read as a "0". Given the potential for errors, metric equivalents should always be used. The degree symbol (°), which is commonly used as an abbreviation for hours (e.g., "q 2-4°" for every 2–4 hours), should not be used, since it can be confused with a "0" (zero). Further, the use of the degree symbol for primary, secondary, and tertiary (1°, 2°, and 3°) is discouraged, since the former could be confused with quantities (i.e. 10, 20 and 30, respectively). Micrograms are abbreviated "mcg" rather than "µg" (which, if handwritten, could easily be mistaken for "mg" (milligrams). Even so, pharmacists must be on the alert for inadvertent over- or under-prescribing through a momentary lapse of concentration.
Many abbreviations are derived from Latin phrases. Hospital pharmacies have more abbreviations, some specific to the hospital. Different jurisdictions follow different conventions on what is abbreviated or not. Prescriptions that do not follow area conventions may be flagged as possible forgeries. Some abbreviations that are ambiguous, or that in their written form might be confused with something else, are not recommended and should be avoided. These are flagged in the table in the main article. However, all abbreviations carry an increased risk for confusion and misinterpretation and should be used cautiously.
a basis or chief ingredient intended to cure (curare) an adjuvant to assist its action and make it cure quickly (cito) a corrective to prevent or lessen any undesirable effect (tuto) a vehicle or excipient to make it suitable for administration and pleasant to the patient (jucunde) The subscription section contains dispensing directions to the pharmacist. This may be compounding instructions or quantities. The signature section contains directions to the patient and is often abbreviated "Sig." or "Signa." It also obviously contains the signature of the prescribing medical practitioner though the word signature has two distinct meanings here and the abbreviations are sometimes used to avoid confusion. Thus sample prescriptions in modern textbooks are often presented as: As a prescription is nothing more than information among a prescriber, pharmacist and patient, information technology can be applied to it. Existing information technology is adequate to print out prescriptions. Hospital information systems in some hospitals do away with prescriptions within the hospital. There are proposals to securely transmit the prescription from the prescriber to the pharmacist using smartcard or the internet. In the UK, a project called the Electronic Transfer of Prescriptions (ETP) within the National Programme for IT (NPfIT) piloted such a scheme between prescribers and pharmacies. Within computerized pharmacies, the information on paper prescriptions is recorded into a database. Afterwards, the paper prescription is archived for storage and legal reasons. A pharmacy chain is often linked together through corporate headquarters with computer networking. A person who has a prescription filled at one branch can get a refill of that prescription at any other store in the chain, as well as have their information available for new prescriptions at any branch.
Some online pharmacies also offer services to customers over the internet, allowing users to specify the store that they will pick up the medicine from. Many pharmacies provide services to ship prescription refills to the patient's home. They also offer mail service where a customer can mail in a new, original prescription and a signed document, and they will ship the filled prescription back. Pharmacy information systems are a potential source of information for pharmaceutical companies, as it contains information about the prescriber's prescribing habits. Prescription data mining of such data is a developing, specialized field. Many prescribers lack the digitized information systems that reduce prescribing errors. To reduce these errors, some investigators have developed modified prescription forms that prompt the prescriber to provide all the desired elements of a good prescription. The modified forms also contain predefined choices such as common quantities, units and frequencies that the prescriber may circle rather than write out. Such forms are thought to reduce errors, especially omission and handwriting errors and are actively under evaluation.
Figure 2: 5 Powerful Benefits of E-Prescriptions in Healthcare Electronic prescription (e-prescribing or e-Rx) is the computer-based electronic generation, transmission, and filling of a medical prescription, taking the place of paper and faxed prescriptions. E-prescribing allows a physician, physician assistant, pharmacist, or nurse practitioner to use digital prescription software to electronically transmit a new prescription or renewal authorization to a community or mail-order pharmacy. It outlines the ability to send error-free, accurate, and understandable prescriptions electronically from the healthcare provider to the pharmacy. E-prescribing is meant to reduce the risks associated with traditional prescription script writing. It is also one of the major reasons for the push for electronic medical records. By sharing medical prescription information, e-prescribing seeks to connect the patient's team of healthcare providers to facilitate knowledgeable decision making.
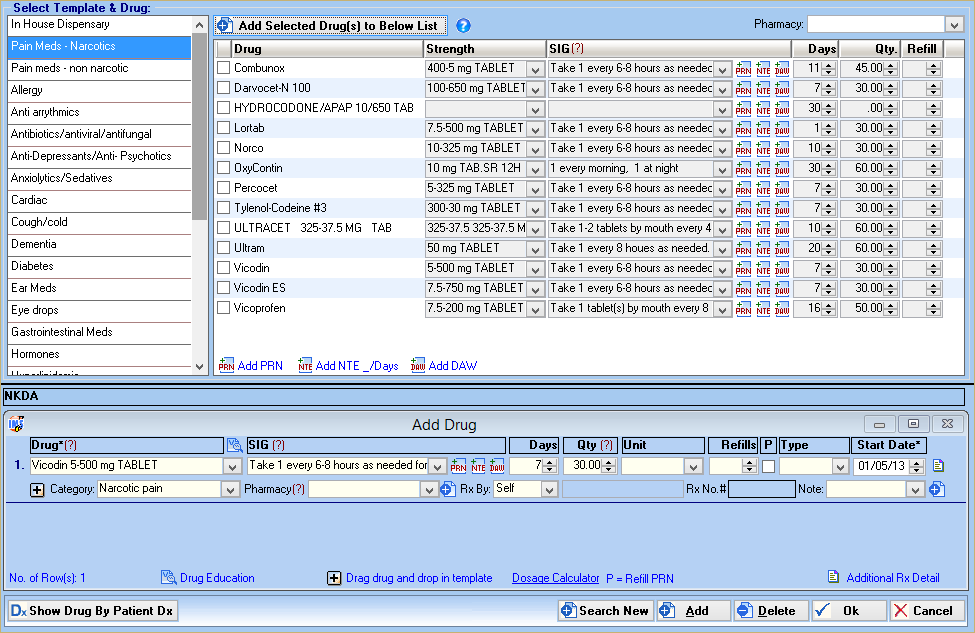
Patient's identification Generating a complete active medication list, possibly incorporating electronic data received from an insurance provider Access to patient historical data Prescribe or add new medication and select the pharmacy where the prescription will be filled. Work with an existing medication within the practice, this can involve viewing details of a medication, remove a medication from the active medication list, change dose, etc., for a medication or renew one or more medications Printing prescriptions Electronically transmitting prescriptions to a transaction hub Conducting all safety checks using an integrated decision support system, known as a Drug Utilization Review. Safety checks include: automated prompts that offer information on the drug being prescribed, potential inappropriate dose or route of administration, drug-drug interactions, allergy concerns, or warnings of caution Flagging availability of lower cost, therapeutically appropriate alternatives (if any) Providing information on formulary or tiered formulary medications, patient eligibility, and authorization requirements received electronically from the patient's insurance provider System integration capabilities (e.g., connection with various databases, connection with pharmacy and pharmacy benefit manager systems) Educational capabilities (e.g., patient education, provider feedback) Prescriber - typically a physician Transaction hub Pharmacy with implemented electronic prescribing software Pharmacy Benefit Manager (PBM) The PBM and transaction hub work closely together. The PBM works as an intermediate actor to ensure the accuracy of information, although other models may not include this to streamline the communication process. In addition to pharmacies, medical tests can also be prescribed.
Reduce prescribing and dispensing errors Decrease the work needed to execute a prescription Speed receipt of prescribed drugs Avoid more adverse drug interactions and reactions More reliably offer to substitute less expensive drug alternatives by checking the formulary of the insurance provider in the doctor's office Improve medication compliance (taking the prescribed medications on time) by reducing lost and unfilled prescriptions and minimizing patient costs Reduce the incidence of drug diversion (drug abuse) by alerting providers and pharmacists of duplicative prescriptions for controlled substances. Safety improvements are highly desirable; in 2000, the Institute of Medicine identified medication errors as the most common type of medical error in health care, estimating that this leads to several thousand deaths each year.
Figure 3: EMR E-Prescription Software | EMR-EHRS Financial Cost and Return on Investment (ROI) - The costs associated with purchasing, implementing, supporting and maintaining such a system may be beyond the means of most small clinical practices, and noted to be one of the greatest implementation barriers. Health care workers who are responsible for medical prescription, especially those in small practices, inner-city areas, or remote rural settings, may bear more than their fair share of the cost associated with e-prescribing. This is in response to the various other stakeholders that may reap the benefits from such a system, without having to financially support it, disseminating their risk substantially. Clinical practices therefore need to invest significantly in both hardware and software, with varying costs based on system specifications (stand alone system or entire EHR system). Even clinics that receive free e-prescribing systems may face financial costs pertaining to management of the interface, customization due to flexibility, training, maintenance, and upgrades. On top of this, the clinic must also take into consideration the lost time and efficiency during the transition period of implementation. As a result, large urban areas may see the greatest ROI when compared to those in rural areas. Change management - Many underestimate the challenges pertaining to change management when transitioning from paper-based prescriptions to e-prescribing. This is especially true in busy practices where healthcare providers and associated staff are accustomed to their current management system, in which case change management becomes extremely important. Potentially difficult and time-consuming analysis may be needed to understand how to change workflow around the management of prescriptions with the introduction of an electronic system. The change also requires pharmacists to increase their awareness of new types of errors associated with e-prescribing, in order to best target their activities to reduce clinical risk. As a result, steps must be taken to ensure effective planning, training, support, and continuous quality improvement for successful transition. Hardware and software selection - Choosing the right hardware platform and software applications can be a rather daunting task for practices, especially in regards to small and busy settings. Many have limited access to expert information technology personnel/staff, leading them to struggle with how to get started, appropriate vendor selection, cost and function negotiations, and most importantly, long-term support to ensure continuous functionality and meaningful use. Erroneous alerts - The inability to effectively use clinical decision support systems due to the erroneous triggering of pop-up alerts with ill-defined software is also a great limitation. Under such circumstances, many opt to turn the notifications off, disabling one of the system's most beneficial aspects. Integrity of data input - Accidental data entry errors such as selecting the wrong patient or clicking on the wrong choice in a menu of dosages may occur. Software vendors can reduce errors by continually reviewing user feedback and follow best practices in user interface design. Security and privacy - As with many eHealth solutions, privacy of patient information stored in electronic format may lead to the possibility of novel errors, such as inadvertently divulging protected health information on the Internet through inadequate security practices. Instances of negligence may also arise, where employees may forward prescriptions to organizations outside its intended use. Another security issue that needs to be addressed up front is the verification of electronic signatures, in ensuring the medical integrity of the prescriptions received by pharmacists. Hospitals, clinics, and pharmacies are counselled to be protected with firewalls, use strict computer permission settings, and remain vigilant toward signs of an intrusion. System downtime - Periods of system downtime may arise, either due to network-related issues, hardware failure, or loss of electricity. The inability to use electronic prescribing when the system is not accessible is of great concern, and must be addressed with the discussion of fall-back procedures and mechanisms when such situations arise.
Patient Access Lost - In the event of a development beyond the control of the patient, such as a software malfunction in the health care provider's office, the patient can no longer ask the care provider for a paper prescription to take to a pharmacy (in New York, where e-prescribing is mandatory with exceptions; other states to follow suit) in order to obtain needed medicines. States such as New York, Connecticut, Maine and Pennsylvania do however, allow a prescriber to issue paper prescriptions in cases of temporary technological or electronic failure. This leaves the patient at the mercy of technicians or other undiscoverable workers.
The use of electronic prescription has been designated as an important strategic policy to improve health care in Europe. The aim of the European Union is to have a cross-border electronic healthcare system in Europe which will enable EU citizens to obtain e-Prescriptions anywhere in Europe. The Scandinavian countries are leading Europe in deploying e-Prescription. Other countries which use the prescription process routinely are Norway, Denmark, Finland, Sweden, Belgium, the Netherlands, Italy, Iceland, Greece, England, Scotland, Wales and Northern Ireland. The European Union is pushing for more cross border health data exchange. These developments reflect broader trends toward the digital integration of consultation, prescribing, and medication supply within European healthcare systems. Multiple perceived barriers impede its incorporation in clinical practice. There are varying interpretations and implementations of data protection and confidentiality laws in the 27 member states. Infrastructures are not in place to support the system and stakeholders in some jurisdictions are reluctant to embrace e-health due to the high cost and the lack of security of the systems. Interoperability of different systems is only a partial solution. Security and enforcement of privacy must also be equally enforced.
About 420 million repeat prescriptions are generated in the UK each year - about 200 for each general practitioner each week. They account for about 80% of the cost of medication in primary care. Paper based Repeat Dispensing Services were introduced by the NHS in 1991, and in 1992 it became possible to use the NHS Electronic Prescription Service for this purpose. In 2017 awareness of the scheme among patients was low. In October 2017 Keith McNeil, NHS England's chief clinical information officer demanded that NHS hospitals should be moved rapidly onto electronic prescribing in the light of research showing it would cut serious prescribing errors by more than half. There was no information about the extent to which it is happening in hospitals. After successful pilots in London and the East Midlands it was agreed in April 2018 that electronic prescribing should be introduced in all urgent care settings in England, including NHS 111 and other Out-of-hours services so that dispensed medication can be ready for collection at a pharmacy when patients arrive. £78 million was allocated in December 2018 to encourage progress with implementing electronic prescribing in NHS organisations which were struggling. Electronic prescribing is to start in English hospitals in the summer of 2022, using the IC24 system which was piloted at Midlands Partnership NHS Foundation Trust from 2020.
An electronic health record (EHR) is the systematized collection of electronically stored patient and population health information in a digital format. These records can be shared across different health care settings. Records are shared through network-connected, enterprise-wide information systems or other information networks and exchanges. EHRs may include a range of data, including demographics, medical history, medication and allergies, immunization status, laboratory test results, radiology images, vital signs, personal statistics like age and weight, and billing information. For several decades, EHRs have been touted as key to increasing quality of care. EHR combines all patients' demographics into a large pool, which assists providers in the creation of "new treatments or innovation in healthcare delivery" to improve quality outcomes in healthcare.
Combining multiple types of clinical data within electronic health records has enabled clinicians to identify and stratify patients with chronic conditions. EHR systems may also support improvements in quality of care through the use of data and analytics to help prevent hospitalizations among high-risk patients. EHR systems are designed to store data accurately and to capture a patient's state across time. It eliminates the need to track down a patient's previous paper medical records and assists in ensuring data is up-to-date, accurate, and legible. It also allows open communication between the patient and the provider while providing "privacy and security." EHR is cost-efficient, decreases the risk of lost paperwork, and can reduce risk of data replication as there is only one modifiable file, which means the file is more likely up to date. Due to the digital information being searchable and in a single file, EMRs (electronic medical records) are more effective when extracting medical data to examine possible trends and long-term changes in a patient. The widespread adoption of EHRs and EMRs may also facilitate population-based studies of medical records.
Electronic medical records could also be studied to quantify disease burdens – such as the number of deaths from antimicrobial resistance – or help identify causes of, factors of, links between, and contributors to diseases, especially when combined with genome-wide association studies. This may enable increased flexibility, improved disease surveillance, better medical product safety surveillance, better public health monitoring (such as for evaluation of health policy effectiveness), increased quality of care (via guidelines and improved medical history sharing), and novel life-saving treatments.
Theoretically, free software such as GNU Health and other open-source health software could be used or modified for various purposes that use electronic medical records, i.e., via securely sharing anonymized patient treatments, medical history, and individual outcomes (including by common primary care physicians). Decision support: Electronic health records could support clinical decision-support systems. Personalized medicine: They could be used among other biodata for digital twins (also called health avatars) for personalized medicine. mHealth integration: They could be coupled with mHealth mobile applications and wearable technology. Screening: Artificial intelligence systems could use this data, as well as other integrated data, to screen for potential diseases via multimodal learning. Syndromic surveillance: Real-time analysis and data mining of the records could be used, along with other data, in syndromic surveillance to rapidly identify common exposures among patients suspected of being part of an outbreak, for epidemic forecasting and for early outbreak detection, especially in identified potential pandemic pathogen (PPP) hotspot regions and potentially as a means for pandemic prevention. Vaccination deployment: Interoperable, collaboratively developed, standardization-based health records systems could increase the speed of vaccination campaigns and reduce their costs or workloads. According to Dr. Bob Kocher, as of 2021, there are "1,000 different electronic health record systems in the U.S., and almost every hospital and clinic has a slightly different system tailored to its own needs" which caused difficulties and delays during COVID-19 vaccinations, with similar problems being reported in other countries. Medical outcomes data: Such records could also be used to match patients to clinical trials with software, reducing the burden on users to partake in research and making previously siloed primary care data more valuable to society at larger or other patients.
Track care (e.g., prescriptions) and outcomes (e.g., blood pressure) Trigger warnings and reminders Send and receive orders, reports, and results Decrease billing processing time and create more accurate billing systems Facilitate Health Information Exchange - a technical and social framework that enables information to move electronically between organizations Using an EMR to read and write a patient's record is not only possible through a workstation but, depending on the type of system and health care settings, may also be possible through mobile devices that are handwriting capable, such as tablets and smartphones. Electronic medical records may include access to personal health records (PHR) which makes individual notes from an EMR readily visible and accessible to consumers. Some EMR systems automatically monitor clinical events by analyzing patient data from an electronic health record to predict, detect, and potentially prevent adverse events. This can include discharge/transfer orders, pharmacy orders, radiology results, laboratory results, and any other data from ancillary services or provider notes. This type of event monitoring has been implemented using the Louisiana Public Health Information Exchange, which links statewide public health with electronic medical records. This system alerted medical providers when a patient with HIV/AIDS had not received care in over twelve months. This system greatly reduced the number of missed critical opportunities.
Human threats, such as employees or hackers. Natural and environmental threats, such as earthquakes, hurricanes, and fires. Technology failures, such as a system crashing. These threats can either be internal, external, intentional, or unintentional. Health information systems professionals consider these particular threats when discussing ways to protect patients' health information. It has been found that there is a lack of security awareness among health care professionals in countries such as Spain. The Health Insurance Portability and Accountability Act (HIPAA) has developed a framework to mitigate the harm of these threats that is comprehensive but not so specific as to limit the options of healthcare professionals who may have access to different technology. With the increase of clinical notes being shared electronically due to the 21st Century Cures Act, an increase in sensitive terms used across the records of all patients, including minors, are increasingly shared amongst care teams, complicating efforts to maintain privacy. Personal Information Protection and Electronic Documents Act (PIPEDA) was given Royal Assent in Canada on 13 April 2000 to establish rules on the use, disclosure, and collection of personal information. The personal information includes both non-digital and electronic forms. In 2002, PIPEDA extended to the health sector in Stage 2 of the law's implementation. There are four provinces where this law does not apply because their privacy laws were considered similar to PIPEDA: Alberta, British Columbia, Ontario, and Quebec. The COVID-19 pandemic in the United Kingdom led to radical changes. NHS Digital and NHSX made changes, said to be only for the duration of the crisis, to the information sharing system GP Connect across England, meaning that patient records are shared across primary care. Only patients who have specifically opted out are excluded.
The majority of the countries in Europe have made a strategy for the development and implementation of electronic health record systems. This would mean greater access to health records by numerous stakeholders, even from countries with lower levels of privacy protection. The implementation of the Cross-Border Health Directive and the European Commission's plans to centralize all health records are of prime concern to the EU public who believe that the health care organizations and governments cannot be trusted to manage their data electronically and expose them to more threats. The idea of a centralized electronic health record system was poorly received by the public who are wary that governments may use of the system beyond its intended purpose. There is also the risk for privacy breaches that could allow sensitive health care information to fall into the wrong hands. Some countries have enacted laws requiring safeguards to be put in place to protect the security and confidentiality of medical information. These safeguards add protection for records that are shared electronically and give patients some important rights to monitor their medical records and receive notification for loss and unauthorized acquisition of health information. The United States and the EU have imposed mandatory medical data breach notifications. The risks associated with centralized electronic health record infrastructure were underscored in 2024 when a ransomware attack on Change Healthcare, a major healthcare claims processing system, disrupted electronic prescriptions and insurance claims for healthcare providers across the United States for several weeks, demonstrating how attacks on shared EHR infrastructure can have cascading effects across the healthcare system. Researchers noted that extreme market concentration in health information technology created systemic cybersecurity and national security risks, as the compromise of a single entity could affect access to health records for a significant portion of the population.
Sentinel Common Data Model: Initially started as Mini-Sentinel in 2008. Use by the Sentinel Initiative of the USA's Food and Drug Administration. OMOP Common Data Model: A model that defines how electronic health record data, medical billing data, or other health care data from multiple institutions can be harmonized and queried in unified way. It is maintained by Observational Health Data Sciences and Informatics consortium. PCORNet Common Data Model: First defined in 2014 and used by PCORI and People-Centered Research Foundation. Virtual Data Warehouse: First defined in 2006 by HMO Research Network. Since 2015, by Health Care System Research Network.
The sharing of patient information between health care organizations and IT systems is changing from a "point to point" model to a "many to many" one. The European Commission is supporting moves to facilitate cross-border interoperability of e-health systems and to remove potential legal hurdles. To allow for global shared workflow, studies will be locked when they are being read and then unlocked and updated once reading is complete. This enables Radiologists to serve multiple health care facilities and read and report across large geographical areas, thus balancing workloads. The biggest challenges will relate to interoperability and legal clarity. In some countries, it is almost forbidden to practice teleradiology. The variety of languages spoken is a problem, and multilingual reporting templates for all anatomical regions are not yet available. However, the market for e-health and teleradiology is evolving more rapidly than any laws or regulations.
The complete TRA is available online for CMS users at https://tra.cloud.cms.gov . This is an internal CMS website that is not available to the public. If you have any feedback regarding TRA content or website, please contact us at the following link: TRA Feedback Survey The Centers for Medicare & Medicaid Services (CMS) develops and implements information technology guidance known as the CMS Technical Reference Architecture (TRA), which is critical to the effective implementation and operations of all agency processing environments (hereafter simply “CMS Processing Environments”).
The CMS Technical Reference Architecture provides CMS’s authoritative technical architecture approach and technical reference standards to assure the secure and high-quality delivery of healthcare services to beneficiaries, providers, and business partners. It is intended for all agency business partners in developing, transitioning to, and maintaining CMS Processing Environments.
The CMS TRA spans five sections which provide engineering detail that adheres to the approved CMS architecture and other CMS standards. As technology and standards evolve, so does the TRA guidance. What if prescribing medication took seconds, with built-in safety checks, real-time patient data, and zero ambiguity? The market momentum is strong. The global e-prescribing market is projected to exceed $7 billion by 2027, driven by regulatory push, increasing digitization, and the need to reduce medication errors. Leaders like Epic Systems and DrFirst are already shaping the space, yet there is still massive opportunity for smarter, AI-enabled solutions.
2. System Architecture & Core Working Principles Healthcare providers are shifting from manual prescriptions toward intelligent platforms that improve accuracy, streamline workflows, and enhance patient safety. If you’re planning to build an e-prescription system, this is a high-impact space with immediate value.
E-prescription software is a digital solution that allows healthcare providers to create, manage, and send prescriptions electronically to pharmacies. Digital prescription creation Medication history tracking Drug interaction checks Pharmacy integration Refill and renewal management Unlike traditional handwritten prescriptions, these systems reduce ambiguity and improve coordination between clinicians and pharmacies.
Traditional prescribing methods rely heavily on manual processes, which increases the likelihood of errors and delays. Reduced medication errors Automated checks for drug interactions, allergies, and dosage accuracy significantly lower risk. Faster prescribing workflows Clinicians can generate and send prescriptions instantly, reducing patient wait times. Improved patient safety Real-time access to patient history ensures more informed prescribing decisions.
Better pharmacy coordination Direct digital transmission eliminates the need for paper prescriptions and manual entry. Enhanced compliance and tracking Digital records provide complete traceability for prescriptions, refills, and audits. 1) Digital prescription management- Allow clinicians to create, edit, and send prescriptions electronically with standardized formats.
2) Drug interaction and allergy checks - Automated safety checks flag potential risks in real time, ensuring safer prescribing. 3) Medication history tracking - Maintain a complete record of patient prescriptions to support better clinical decisions. 4) Pharmacy integration - Enable seamless communication with pharmacies for prescription fulfillment and updates. 5) Refill and renewal management- Automate refill requests and approvals to streamline ongoing patient care.
6) Clinical decision support- AI-driven recommendations assist with dosage, alternatives, and treatment optimization. Frontend layer Interfaces for clinicians, pharmacists, and patients with intuitive workflows. Data layer Stores patient records, medication data, and prescription history securely. Integration layer Connects with EHR systems, pharmacies, and third-party drug databases.
AI and analytics layer Supports decision-making with predictive insights and safety alerts. Security and compliance layer Ensures adherence to regulations such as HIPAA and GDPR with encryption and access control. EHR/EMR integration Access patient medical history, allergies, and diagnoses in real time.
Pharmacy network integration Enable direct transmission of prescriptions to retail and hospital pharmacies. Drug databases Integrate with comprehensive medication databases for accurate drug information and interaction checks. Regulatory systems Ensure compliance with electronic prescribing standards and controlled substance regulations. Identify your target users and scope. Are you building for clinics, hospitals, or telehealth platforms? Collect data from EHR systems, drug databases, and pharmacy networks. Ensure interoperability and compliance.
Connect with EHRs, pharmacies, and third-party systems using APIs and standards like HL7 and FHIR. Cloud infrastructure AWS HealthLake or Google Cloud Healthcare API for secure data management Basic solution ($20,000 – $40,000) Includes core prescription features and basic integrations. 3. Software Implementation, Frameworks & Protocols Mid-level solution ($40,000 – $80,000) Includes advanced safety checks, EHR integration, and user-friendly dashboards.
Enterprise-grade solution ($80,000 – $150,000+) Includes AI-driven insights, real-time processing, and full regulatory compliance. Feature complexity Number of integrations Compliance and security requirements AI capabilities Team expertise Testing and validation Building in this space is about more than digitizing prescriptions. It is about improving safety, speed, and accuracy at scale.
The real opportunity lies in creating intelligent systems that reduce errors, enhance workflows, and integrate seamlessly into the broader healthcare ecosystem. 1. How much does it cost to build e-prescription software? The cost typically ranges from $20,000 to $150,000+, depending on features and integrations.
2. What are the key features of e-prescription software? Key features include digital prescriptions, drug interaction checks, medication history tracking, pharmacy integration, and clinical decision support. 3. How long does it take to develop e-prescription software? Development usually takes 3 to 9+ months depending on complexity and compliance requirements.
4. What technologies are used in e-prescription systems? Common technologies include React, Node.js, Python, PostgreSQL, MongoDB, and cloud healthcare platforms. 5. What challenges are involved in building such systems? Challenges include regulatory compliance, data security, interoperability, and integration with pharmacy networks.
What if outpatient clinics could run with the efficiency of a well-orchestrated system, where every appointment… CES 2026 continued through Day 4 with products that felt quietly surprising. Many of them seemed obvious once you saw… CES 2026 continued on Day 3 with a familiar pattern. The most interesting products were not trying to impress through… Day 1 & 2 at CES 2026 made one thing obvious. The most impressive products were not the loudest ones.
The backbone of modern virtual care is interoperability. Yet most digital health startups hit a wall when they try to… The future of hospital triage is not about crowded waiting rooms. It is about intelligent, AI-powered digital front… The fintech landscape is undergoing a significant transformation. Recent strategic acquisitions, such as Amazon’s… Global attention on sovereign AI, such as India’s national initiatives, highlights the importance of control and… Official websites use .gov A .gov website belongs to an official government organization in the United States.
Secure .gov websites use HTTPS A lock ( ) or https:// means you've safely connected to the .gov website. Share sensitive information only on official, secure websites. The CMS Technical Reference Architecture (TRA) provides CMS-approved technical standards and architecture guidance for designing, integrating, modernizing, and maintaining information systems across all CMS processing environments, ensuring consistency, interoperab The CMS Technical Reference Architecture (hereafter referred to as the “CMS TRA”) articulates the technical architecture of all Centers for Medicare & Medicaid Services (CMS) processing environments (hereafter simply the “CMS Processing Environments”). A CMS Processing Environment is defined as: Any computing environment (e.g., CMS data center, virtual computing environment, or cloud computing including Infrastructure as a Service (IaaS), Software as a Service (SaaS), and Platform as a Service (PaaS)) that creates, consumes, and/or stores CMS-related data. CMS data includes sensitive, non-sensitive, and security information and event management-related information used to provide CMS services to the public and internal CMS users.
The CMS TRA represents the Agency’s policy guidance to all Agency business partners wishing to develop, transition, and maintain information systems that interact with the CMS Processing Environments. The CMS TRA is approved and authorized by the CMS Chief Information Officer (CIO) and Chief Enterprise Architect (CEA). Toward these ends, the CMS TRA defines a common set of terms and definitions to support CMS’s architecture approach and ensure an effective operating environment. It conveys required design considerations, including security policies and controls (for confidentiality, integrity, and availability), reusability, scalability, and sustainability. The common framework of the CMS TRA supports future application designs as well as architecting and engineering CMS applications. It encourages the use and creation of enterprise shared services and presents clear guidance on their appropriate use and interaction among CMS data centers. By promoting a technical reference standard for future CMS task orders and acquisitions, the CMS TRA clarifies the decision-making process and target technical environments, which helps Agency contractors develop sound and acceptable transition approaches.
This topic introduces the CMS TRA and is the keystone of CMS TRA guidance, as shown in Essential Guidance for the Entire CMS TRA . It articulates the CMS Architectural Vision and provides guidance relevant to all stakeholders. It establishes the guiding principles of the CMS architecture that informs all guidance in subsequent topics and presents overviews of CMS Services Framework and Multi-Zone Architectures.
This topic also summarizes how to request a change to the CMS TRA through the Architecture Change Request (ACR) process. Stakeholders interested in specific architectural topics can find detailed guidance organized in topics as follows: The guidance in each CMS TRA topic includes narrative providing context; Business Rules (BR), which are requirements for TRA compliance; and Recommended Practices (RP), which are strongly encouraged for use within the CMS Processing Environments but not required.
The CMS TRA is intended to guide system architects, business owners, system maintainers, and security auditors in working with CMS’s technical environment. A publicly available version is located at CMS TRA . CMS restricts access to the complete CMS TRA to the following authorized users: CMS executive or management approval is required to provide this document to other entities pursuant to business need.
4. Practical Deployment, Analysis & Case Studies The CMS TRA complements CMS standards documentation. The CMS TRA supersedes and takes precedence over other existing CMS standards documentation, with the following exceptions: The CMS ARS is located at: CMS Acceptable Risk Safeguards (ARS) on the CMS CyberGeek website.
CMS provides an orientation briefing for CMS TRA Document Development (MS PowerPoint) and the ACR Form (PDF) for initiating an Architecture Change Request. Please direct all questions, comments, suggestions, or requests for further information to the CMS CIO Policy Officer at IT_Policy@cms.hhs.gov .
The CMS TRA informs the development of the Agency’s Common Enterprise Infrastructure (CEI) and is the foundation for the design and implementation of processing components and computing environments across the CMS Enterprise. Ensuring the secure operation of all CMS Processing Environments (as defined in CMS Processing Environments ) is a primary architectural consideration. Adhering to the CMS TRA improves interoperability of services across the enterprise, supporting the goal of providing high-value services at lower cost, with higher availability, reduced implementation times, and improved maintainability.
The CMS TRA describes the technical baseline for all CMS Processing Environments. The CMS TRA cites proven, effective, and tested common controls that meet legislatively mandated mission, security, and privacy requirements. The Agency updates the CMS TRA as required to respond to CMS’s changing needs and direction and to reflect current technical standards.
As CMS’s repository of technical reference standards, the CMS TRA plays a critical role in all contracts. Contracting Officers refer to the CMS TRA topics in task orders and solicitations to ensure that contractors understand and apply technical consistency across data centers and contract efforts. The TRA focuses on services, outcomes, and effects instead of physical structures, specific products, or system components.
Unless explicitly stated, references to specific products and/or vendors within the CMS TRA provide information about the existing technical environment rather than express an Agency preference. The CMS TRA supports the Department of Health and Human Services (HHS) Enterprise Architecture principles and satisfies the CMS ARS security control, CM-2, Baseline Configuration .
Defense-in-Depth employs multiple, coordinated security countermeasures to protect against security issues throughout the infrastructure. A Services Framework architecture separates services by their function and encapsulates them with their own layers of protection/defense providing adaptable layers of depth.
A multi-zone architecture, which is a type of Services Framework architecture, places multiple layers of protection/defense on each zone by segregating networks and controlling inter-zone communications. The CMS TRA adheres to the security concept of least privilege , the security objective of granting users only those accesses they need to perform their official duties. When a user is permitted to “self-elevate” temporarily (e.g., Linux sudo command), this action is logged.
Unless explicitly stated, the CMS TRA does not advocate a preferred vendor or suite of products. One notable exception to this rule is shared services (including security services), where a specific technology has been selected and is mandated for use of or integration with this shared service. CMS encourages innovation of supportable solutions within the parameters of the CMS TRA .
When selecting software, business owners should evaluate competing product licenses and leverage existing agency purchasing sources before approving new contractor purchases. The focus should be on minimizing costs and promoting consistency across CMS applications and environments. Business owners are required to utilize Inter-Agency Agreements (IAA), CMS Enterprise License Agreements (ELA), and Government Furnished Software (GFS) to the greatest extent possible. These actions will support CIO Directive 25-02 Use of CMS Enterprise License Agreements , issued July 1, 2025.
For more information on IAA, ELA, or GFS agreements, please contact the Software Asset Management Program Management Office (SAM PMO) at SoftwareLicensesCMS@cms.hhs.gov . CMS encourages reuse and sharing wherever practicable to avoid creating redundant services/applications. There can be multiple cloud and physical data centers in the CMS environment. Any application can reside in any combination of CMS data centers (including CMS Clouds) and use software services—for example, Identity Management (IDM) and Enterprise Portal—of the other data centers. Application software in one data center may leverage services in another data center.
CMS employs several strategies for reuse: adoption of a Service-Oriented Architecture, use of Microservices, and the implementation and use of Strategic and Preferred Solutions. SOA defines a set of principles for developing software as interoperable, reusable, distributed services to fulfill business functions. For example, the Medicaid Information Technology Architecture (MITA) is a SOA framework that allows CMS and state Medicaid organizations to create, deploy, execute, and manage reusable, modular, and interoperable business, data, and technology services. The Application Development section addresses SOA extensively.
Microservices (MS) are a modern interpretation of SOAs for building distributed software systems. Each component/ module of an application is developed and deployed separately. This contrasts with a traditional, “monolithic” application in which all components are developed and deployed as one piece. Microservices are well suited to DevOps methods and tools. The Application Development section addresses Microservices, with additional detail in the TRB Research Spotlight, “Microservice Architecture,” published April 11, 2023.
CMS strongly encourages the use of Strategic and Preferred Solutions. These are solutions which have been designed, tested, and approved for broad use within CMS. Utilizing these existing solutions, which include formally designated Enterprise Shared Services (ESS), shortens the Time-to-Delivery (TTD), facilitates efficient infrastructure use, reduces redundant capabilities, improves access, and leads to more consistent cybersecurity posture. The Office of Management and Budget (OMB) Memorandum M-19-16, Centralized Mission Support Capabilities for the Federal Government , April 26 2019, defines federal IT shared services and policy. (Also see Solutions to Improve Agency Management Efficiency (ussm.gsa.gov) and cio.gov/policies-and-priorities/shared-services ) Details and guidance for the use of these services are described in the following section, CMS Strategic Guidance and Preferred Solutions .
Common platform services are technology services provided in support of all hosted applications. The CMS ecosystem now supports platform services across both cloud and on-premises environments. These capabilities are designed to standardize and simplify support and management. Application developers should use enterprise shared services and common platform services where possible rather than implementing specialized or single-use software.
The CMS TRA supports the Federal Cloud Computing Strategy’s (OMB/Federal CIO Kundra, February 14, 2011) Cloud First Policy. For details, please refer to the Network Services and Infrastructure Services sections. Pursuant to this objective, CMS is closing its on-premises data centers and is migrating all on-premise applications to cloud environments. Any residual on-premises functionality is migrating to cloud-connected collocation facilities. This strategy is aligned with OMB M-19-19 regarding the Data Center Optimization Initiative . “Agencies may not budget any funds or resources toward initiating a new agency-owned data center or significantly expanding an existing agency-owned data center without approval from OMB.” See the full OMB M-19-19 directive for more information. The objective is to drive meaningful improvement to IT infrastructure, achieve cost savings through optimizations and closures, and foster IT modernization.
CMS has a robust set of recommended cloud services and capabilities available to enable rapid migration to and deployment within the cloud. See the CMS Strategic Guidance and Preferred Solutions section for further detail. The CMS TRA permits the use of supportable Open Source software in CMS Processing Environments. For details, please refer to the chapter on Open Source Software in the Application Services Section. Unsupported software in any capacity cannot be patched in a timely manner; accordingly, any Open Source software without a dedicated support matrix violates the CMS ARS .
The CMS TRA applies to all CMS Processing Environments regardless of the approach used to develop and maintain CMS Federal Information Security Modernization Act (FISMA) applications (e.g., using Waterfall, Prototyping, Incremental, Spiral, Rapid Application Development, and Agile). The CMS TRA encourages the appropriate use of automation to reduce variability and increase speed. In code development and deployment process, continuous integration automation (code checkout/build, static code analysis, dependency check, unit testing), continuous deployment release orchestration, Infrastructure as code can be used to avoid manual errors and manage complexity. In production, operational monitoring can be automated by vulnerability scanning, system health, alerts, etc.
The CMS TRA encourages projects to consider sustainability as a critical element of architectural solutions. Projects should apply appropriate attention to future scale, cost, security, operational efficiency, technology, and vendor support. The long-term viability of applications and data products must be considered when integrating any solution into the CMS Processing Environments. Risk and mitigation planning for sustainability should address personnel (technical expertise), operational processes (automation), adherence to Service Level Agreements, and total cost of ownership.
In cloud environment the sustainability for cost, scalability, service level agreements can be achieved by adoption of cloud native features like dynamic scaling up/down of resources based on usage, use of shared instances vs reserved instance and optimal sizing of resources. 5. Performance Evaluation & Extended Technical Observations Inaccessible technology interferes with an individual’s ability to obtain and use information quickly and easily. Section 508 of the Rehabilitation Act of 1973 was enacted to eliminate barriers in IT, to make available new opportunities for people with disabilities, and to encourage development of technologies that will help achieve these goals. CMS operates many programs that are critically important to people with disabilities. IT is often the vehicle for delivering these programs. The most effective and least costly approach to technology accessibility is for CMS to incorporate accessibility into its IT governance, development, and procurement processes.
Under Section 508, federal agencies must give federal employees and members of the public with disabilities access to Information Communication Technology (ICT) and information that is comparable to the access available to individuals without disabilities. For CMS Processing Environments and applications, adherence to the Agency’s Section 508 policies include: CMS provides resources for Section 508 compliance, including policies, validation procedures, and a list of CMS Section 508 Clearance Officers, at: Section 508 and CMS .
PREFERRED: Additional CMS guidance and resources are found in Application Development, Web-based UI Services , as well as in the CMS Design System . The CMS Section 508 Policy provides a clear rationale and compliance road map for CMS Processing Environments and applications and takes precedence over the CMS TRA . The following paragraphs summarize the basis for these requirements, which is explained further in the CMS Section 508 Policy.
In 1986, Congress added Section 508 to the Rehabilitation Act of 1973. Section 508 established non-binding guidelines for IT accessibility. On August 7, 1998, the president signed into law the Workforce Investment Act of 1998, which included amendments to the Rehabilitation Act. These amendments significantly expanded and strengthened the IT accessibility requirements in Section 508 and made them binding on federal agencies.
Section 508 applies to Information Communication Technology, previously referred to as Electronic and Information Technology (EIT). Section 508, as amended, specifically requires that, when federal agencies develop, procure, maintain, or use ICT: Section 501 of the Act requires CMS to be a model employer of people with disabilities. Section 504 requires CMS to ensure equally effective access to its programs and services. CMS can reach both objectives only if it adheres to the requirements of Section 508.
The CMS Section 508 policy is based on the standards described in the following subtopics. The U.S. Access Board’s Information and Communication Technology Revised 508 Standards and 255 Guidelines apply to a wide range of products and services, including but not limited to, the following: The final rule jointly updates requirements for information and communications technology covered by Section 508 of the Rehabilitation Act and Section 255 of the Telecommunications Act. The Section 508 Standards apply to electronic and information technology procured by the federal government. The Section 255 Guidelines address access to telecommunications products and services and apply to manufacturers of telecommunication equipment.
Web Content Accessibility Guidelines (WCAG) 2.1 define how to make web content more accessible to people with disabilities. WCAG 2.0 is developed through the World Wide Web Consortium (W3C) process in cooperation with individuals and organizations around the world. The goal is to provide a shared standard for web content accessibility that meets the needs of individuals, organizations, and governments internationally. WCAG 2.0 is designed to apply broadly to different web technologies now and in the future, and to be testable with a combination of automated testing and human evaluation. WCAG 2.0 has three conformance levels, including A (lowest), AA, and AAA (highest). CMS requires that the WCAG 2.0 standards be met at both the Level A and Level AA conformance level.
Web accessibility depends on accessible content as well as accessible web browsers and other user agents. Authoring tools also have an important role in web accessibility. For an overview of how these components of web development and interaction work together, please refer to the following links: The Portable Document Format/Universal Accessibility (PDF/UA-2) standard, defined by ISO 14289-2:2024 , describes technical requirements for universally accessible PDF documents by identifying a set of relevant PDF functions (including text content, images, form fields, comments, bookmarks, and metadata) based on ISO 32000-2:2020 (PDF 2.0) and specifies how they should be used in PDF/UA-compliant documents. Successful access to content within PDFs depends both on compliant documents and compliant PDF programs and assistive technology. PDF/UA therefore also specifies requirements for compliant assistive technology.
For assistive technologies to work properly with PDF/UA, they must meet the following requirements: For information about designing accessible documents that adhere to HHS’s requirements, please refer to the HHS Section 508 Accessibility Conformance Checklists . HHS Web Standards apply to all HHS Office of the Secretary (OS) websites—including all Operating Divisions (OPDIVs) / Staff Divisions (STAFFDIVs) and Secretarial Priority websites, whether aimed at internal or external audiences. These standards are required for the design and development of all HHS/OS websites and may be adopted by OPDIVs.
The Framework covers all HHS web sites, internal or external, that are owned, managed, or funded by Operating and Staff Divisions, including CMS, whether developed by staff or acquired through contracts, cooperative agreements, grants, and/or formally established partnerships with other government entities and/or the private sector. The Framework covers traditional web content, including all attached or linked HHS files, and all news and social media, including videos, podcasts, blogs, Wikis, and associated applications on all HHS web sites.
CMS uses the following tools and methods to test IT products and artifacts for Section 508 compliance: The architectural guidelines described by the CMS TRA are designed to provide flexibility to development teams in choosing a technical approach, and yet there are cases where CMS has a strongly preferred approach or solution option. This section provides information about such Strategic Guidance and Preferred Solutions.
CMS systems and data must be protected from a constantly evolving threat and vulnerability landscape. Aligning to strategic guidance and utilizing preferred solutions strengthens CMS security posture through extending the use of thoroughly validated and tested security controls and procedures. Maintaining CMS data within the CMS security boundary facilitates CMS stewardship of the data.
The use of preferred solutions also shortens time-to-delivery, reduces redundant development, facilitates efficient use of infrastructure, and leverages CMS strategic investments and economies of scale. This aligns to the TRA Guiding Principle of Reuse as well as broader federal IT policy (see Office of Management and Budget (OMB) Memorandum M-19-16, Centralized Mission Support Capabilities for the Federal Government , April 26 2019, and Federal Shared Services ).
The goal is to speed secure system deployment by utilizing existing solutions that may provide built-in automation, approved security configurations, and pre-authorized infrastructure. Use of these solutions is strongly encouraged unless there is a more compelling business case for an alternative. CMS encourages its organizations to maximize the benefits of utilizing the Microsoft 365 Government Community Cloud (GCC) capabilities through the CMS tenant. All CMS email accounts include G5 subscriptions that provide access to Office 365 applications , storage, and other advanced security and data management features. CMS has completed transition from Zoom to Microsoft Teams for all CMS-hosted meetings and is migrating from the on-premises SharePoint 2019 environment to SharePoint Online.
The CMS TRA will provide high-level information about preferred solutions. Detailed information including their setup and use will be found through the supplementary sources/ links to additional information. Note that hyperlinks in this section may refer to CMS internal information sources; a CMS EUA ID and access to the CMS intranet may be required for access.
Additionally, links to Strategic Guidance and Preferred Services will be included throughout the TRA, aligned to associated TRA guidance. PREFERRED - CMS strategic guidance and preferred solution information throughout the CMS TRA will appear like this. The preferred solutions in this section are CMS “enterprise services”, based on an expanded definition of the term. The updated CMS definition of enterprise services reflects that these capabilities may be developed and provided by any CMS Center or Office or by a vetted partnership of Centers/Offices. This includes but extends well beyond centrally provided “shared services”. In the new model, enterprise services can be leveraged as a shared capability or provide a pattern for a new implementation if required.
A CMS enterprise service may be leveraged without onboarding with an established support organization or a central enterprise instance. CMS encourages the use of the most appropriate deployment model depending on business requirements. A project might, for example, choose to deploy a parallel instance but still use the standards and processes of the enterprise instance, potentially enabling them to utilize existing support staff. An existing, validated solution can be used as an architectural pattern, with any refinements shared back with the original.
The overall group of enterprise services form a federated set of capabilities which development teams can tap into, avoiding duplication and aligning with CMS standards. Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/Medical%20prescription • https://en.wikipedia.org/wiki/Electronic%20prescribing • https://en.wikipedia.org/wiki/Electronic%20health%20record • https://www.cms.gov/data-research/cms-information-technology/cio-resource-library/technical-reference-architecture • https://www.linkedin.com/pulse/how-build-e-prescription-software-2026-features-architecture-uducc • https://security.cms.gov/policy-guidance/cms-technical-reference-architecture
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.

Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Secure Electronic Medical Prescription.
[*] Metasploit Scan Running on Target Subnet for Secure Electronic Medical Prescription... [✓] SafeBreach / AttackIQ Continuous Exposure Agent Triggered ──────────────────────────────────────────────────────────────────────── [11:48:02.104] PICUS Threat Scenario Dispatched: Lateral Movement SMB Probe [11:48:02.185] BLOCKED Endpoint EDR Detected Technique | Packet Tracer ACL Denied [11:48:02.240] CYMULATE Prevention Rate = 96.8% | SIEM Latency = 38 ms [11:48:02.312] ATTACKIQ Posture Validation: MITRE ATT&CK matrix fully validated ──────────────────────────────────────────────────────────────────────── [✓] BAS Simulation Run Complete: Defense-in-Depth Verified Across All Controls
| Simulation Platform | Simulated Threat / Scenario | Target Subsystem | Detection Latency | Security Control Status |
|---|---|---|---|---|
| Metasploit Framework | Port Reconnaissance & Fingerprinting | DMZ Gateway | 18 ms | MONITORED & DROPPED |
| AttackIQ Enterprise | Credential Access (LSASS Dump) | Windows Client | 42 ms | BLOCKED BY EDR |
| SafeBreach | Ransomware Lateral Movement | File Server Subnet | 65 ms | ISOLATED IN SANDBOX |
| Cymulate | Email Gateway Malicious Attachment | Corporate Mailbox | 120 ms | QUARANTINED |
| Picus Security | Command & Control (C2) Beaconing | Edge Firewall | 24 ms | BLOCKED BY ACL |