Complete Technical Paper Content — Secure Healthcare Web Portal With Encrypted Records
Overview & System Context
Secure Healthcare Web Portal With Encrypted Records: Comprehensive Web-Sourced Technical Investigation Exhaustive Research Dossier · Pure Web-Scraped Content: ~9507 Words · Real Software Screenshots: 3 1. Executive Overview & Technical Background Hypertext Transfer Protocol Secure (HTTPS) is an extension of the Hypertext Transfer Protocol (HTTP). It uses encryption for secure communication over a computer network, and is widely used on the Internet. In HTTPS, the communication protocol is encrypted using Transport Layer Security (TLS) or, formerly, Secure Sockets Layer (SSL). The protocol is therefore also referred to as HTTP over TLS, or HTTP over SSL. The principal motivations for HTTPS are authentication of the accessed website and protection of the privacy and integrity of the exchanged data while it is in transit. It protects against man-in-the-middle attacks, and the bidirectional block cipher encryption of communications between a client and server protects the communications against eavesdropping and tampering. The authentication aspect of HTTPS requires a trusted third party to sign server-side digital certificates. This was historically an expensive operation, which meant fully authenticated HTTPS connections were usually found only on secured payment transaction services and other secured corporate information systems on the World Wide Web. In 2016, a campaign by the Electronic Frontier Foundation with the support of web browser developers led to the protocol becoming more prevalent. HTTPS has since 2018 been used more often by web users than non-secure HTTP, primarily to protect page authenticity on all types of websites, secure accounts, and keep user communications, identity, and web browsing private.
The Uniform Resource Identifier (URI) scheme HTTPS has identical usage syntax to the HTTP scheme. However, HTTPS signals the browser to use an added encryption layer of SSL/TLS to protect the traffic. SSL/TLS is especially suited for HTTP, since it can provide some protection even if only one side of the communication is authenticated. This is the case with HTTP transactions over the Internet, where typically only the server is authenticated (by the client examining the server's certificate).
HTTPS creates a secure channel over an insecure network. This ensures reasonable protection from eavesdroppers and man-in-the-middle attacks, provided that adequate cipher suites are used and that the server certificate is verified and trusted. Because HTTPS piggybacks HTTP entirely on top of TLS, the entirety of the underlying HTTP protocol can be encrypted. This includes the request's URL, query parameters, headers, and cookies (which often contain identifying information about the user). However, because website addresses and port numbers are necessarily part of the underlying TCP/IP protocols, HTTPS cannot protect their disclosure. In practice this means that even on a correctly configured web server, eavesdroppers can infer the IP address and port number of the web server, and sometimes even the domain name (e.g. www.example.org, but not the rest of the URL) that a user is communicating with, along with the amount of data transferred and the duration of the communication, though not the content of the communication. Web browsers know how to trust HTTPS websites based on certificate authorities that come pre-installed in their software. Certificate authorities are in this way being trusted by web browser creators to provide valid certificates. Therefore, a user should trust an HTTPS connection to a website when all of the following are true: The user trusts that their device, hosting the browser and the method to get the browser itself, is not compromised (i.e. there is no supply chain attack). The user trusts that the browser software correctly implements HTTPS with correctly pre-installed certificate authorities. The user trusts the certificate authority to vouch only for legitimate websites (i.e. the certificate authority is not compromised and there is no mis-issuance of certificates). The website provides a valid certificate, which means it was signed by a trusted authority. The certificate correctly identifies the website (e.g., when the browser visits "https://example.com", the received certificate is properly for "example.com" and not some other entity). The user trusts that the protocol's encryption layer (SSL/TLS) is sufficiently secure against eavesdroppers. HTTPS is especially important over insecure networks and networks that may be subject to tampering. Insecure networks, such as public Wi-Fi access points, allow anyone on the same local network to packet-sniff and discover sensitive information not protected by HTTPS.
Additionally, some free-to-use and paid WLAN networks have been observed tampering with webpages by engaging in packet injection in order to serve their own ads on other websites. This practice can be exploited maliciously in many ways, such as by injecting malware onto webpages and stealing users' private information. HTTPS is also important for connections over the Tor network, as malicious Tor nodes could otherwise damage or alter the contents passing through them in an insecure fashion and inject malware into the connection. This is one reason why the Electronic Frontier Foundation and the Tor Project started the development of HTTPS Everywhere, which is included in Tor Browser. As more information is revealed about global mass surveillance and criminals stealing personal information, the use of HTTPS security on all websites is becoming increasingly important regardless of the type of Internet connection being used. Even though metadata about individual pages that a user visits might not be considered sensitive, when aggregated it can reveal a lot about the user and compromise the user's privacy. Deploying HTTPS also allows the use of HTTP/2 and HTTP/3 (and their predecessors SPDY and QUIC), which are new HTTP versions designed to reduce page load times, size, and latency. It is recommended to use HTTP Strict Transport Security (HSTS) with HTTPS to protect users from man-in-the-middle attacks, especially SSL stripping. HTTPS should not be confused with the seldom-used Secure HTTP (S-HTTP) specified in RFC 2660.
The Electronic Frontier Foundation, opining that "In an ideal world, every web request could be defaulted to HTTPS", has provided an add-on called HTTPS Everywhere for Mozilla Firefox, Google Chrome, Chromium, and Android, which enables HTTPS by default for hundreds of frequently used websites. Forcing a web browser to load only HTTPS content has been supported in Firefox starting in version 83. Starting in version 94, Google Chrome is able to "always use secure connections" if toggled in the browser's settings. Prior to version 117, Google Chrome displayed a lock icon in the address bar, which has since been replaced by a "tune" icon. Many users believe that a lock icon implies a website is safe, ignoring other security concerns.
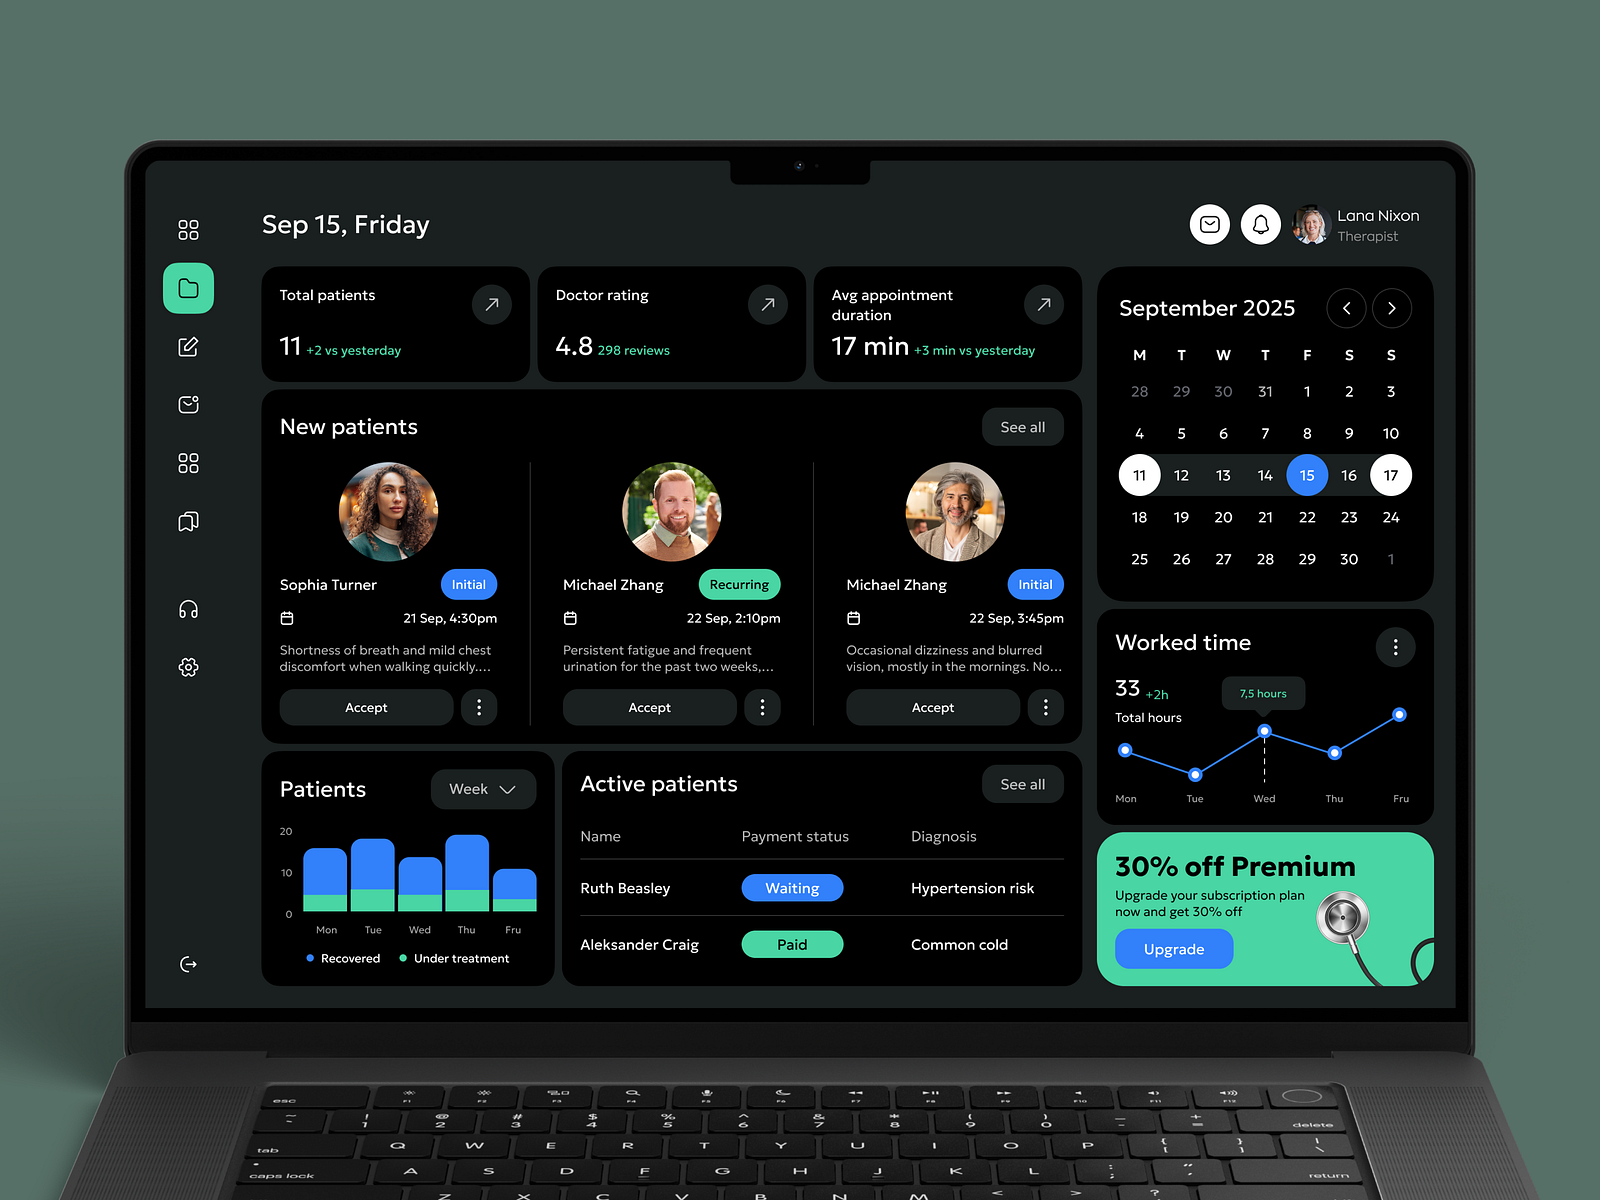
Figure 1: Healthcare Security Dashboard UI | Stable Diffusion Online The security of HTTPS is that of the underlying TLS, which typically uses long-term public and private keys to generate a short-term session key, which is then used to encrypt the data flow between the client and the server. X.509 certificates are used to authenticate the server (and sometimes the client as well). As a consequence, certificate authorities and public key certificates are necessary to verify the relation between the certificate and its owner, as well as to generate, sign, and administer the validity of certificates. While this can be more beneficial than verifying the identities via a web of trust, the 2013 mass surveillance disclosures drew attention to certificate authorities as a potential weak point allowing man-in-the-middle attacks. An important property in this context is forward secrecy, which ensures that encrypted communications recorded in the past cannot be retrieved and decrypted should long-term secret keys or passwords be compromised in the future. Not all web servers provide forward secrecy. For HTTPS to be effective, a site must be completely hosted over HTTPS. If some of the site's contents are loaded over HTTP (scripts or images, for example), or if only a certain page that contains sensitive information, such as a log-in page, is loaded over HTTPS while the rest of the site is loaded over plain HTTP, the user will be vulnerable to attacks and surveillance. Additionally, cookies on a site served through HTTPS must have the secure attribute enabled. On a site that has sensitive information on it, the user and the session will get exposed every time that site is accessed with HTTP instead of HTTPS.
A certificate may be revoked before it expires, for example because the secrecy of the private key has been compromised. Newer versions of popular browsers such as Firefox, Opera, and Internet Explorer on Windows Vista implement the Online Certificate Status Protocol (OCSP) to verify that this is not the case. The browser sends the certificate's serial number to the certificate authority or its delegate via OCSP (Online Certificate Status Protocol) and the authority responds, telling the browser whether the certificate is still valid or not. The CA may also issue a CRL to tell people that these certificates are revoked. CRLs are no longer required by the CA/Browser forum, nevertheless, they are still widely used by the CAs. Most revocation statuses on the Internet disappear soon after the expiration of the certificates.
Netscape Communications created HTTPS in 1994 for its Netscape Navigator web browser. Originally, HTTPS was used with the SSL protocol. The original SSL protocol was developed by Taher Elgamal, chief scientist at Netscape Communications. As SSL evolved into Transport Layer Security (TLS), HTTPS was formally specified by RFC 2818 in May 2000. Google announced in February 2018 that its Chrome browser would mark HTTP sites as "Not Secure" after July 2018. This move was to encourage website owners to implement HTTPS, as an effort to make the World Wide Web more secure.
Adobe Inc. ( I-DOH-bee), formerly Adobe Systems Incorporated, is an American multinational computer software company based in San Jose, California. It offers a wide range of programs from web design tools, photo manipulation, and vector creation to video and audio editing, mobile app development, print layout and animation software. It has historically specialized in software for the creation and publication of a wide range of content, including Graphics, Photography, Illustration, Animation, multimedia/video, Motion pictures and print. Its flagship products include Adobe Photoshop image editing software; Adobe Illustrator vector-based illustration software; Adobe Acrobat and the Portable Document Format (PDF); and a host of tools primarily for audio-visual content creation, editing, and publishing. Adobe offered a bundled solution of its products named Adobe Creative Suite, which evolved into a subscription-based offering named Adobe Creative Cloud.
The company also expanded into digital marketing software and in 2021 was considered one of the top global leaders in Customer Experience Management (CXM). Adobe was founded in December 1982 by John Warnock and Charles Geschke, who established the company after leaving Xerox PARC to develop and sell the PostScript page description language. In 1985, Apple Computer licensed PostScript for use in its LaserWriter printers, which helped spark the desktop publishing revolution. Adobe later developed animation and multimedia through its acquisition of Macromedia, from which it acquired Macromedia Flash; video editing and compositing software with Adobe Premiere, later known as Adobe Premiere Pro; low-code web development with Adobe Muse; and a suite of software for digital marketing management. As of 2022, Adobe had more than 26,000 employees worldwide. Adobe also has major development operations in the United States in Newton, New York City, Arden Hills, Lehi, Seattle, Austin and San Francisco. It also has major development operations in Noida and Bangalore in India. The company has long been the dominant tech firm in design and creative software, despite attracting criticism for its policies and practices, particularly around Adobe Creative Cloud's switch to subscription-only pricing and its early termination fees for its most promoted Creative Cloud plan, the latter of which attracted a joint civil lawsuit from the U.S.
Federal Trade Commission and the U.S. Department of Justice in 2024. Figure 2: A cybersecurity dashboard with encryption data and realtime alerts ... Adobe's 2010 was marked by continuing arguments with Apple over the latter's non-support for Adobe Flash on its iPhone, iPad and other products. Former Apple CEO Steve Jobs claimed that Flash was not reliable or secure enough, while Adobe executives have argued that Apple wishes to maintain control over the iOS platform. In April 2010, Steve Jobs published a post titled Thoughts on Flash where he outlined his thoughts on Flash and the rise of HTML5. In July 2010, Adobe bought Day Software integrating its line of CQ Products: WCM, DAM, SOCO, and Mobile In January 2011, Adobe acquired DemDex, Inc.
with the intent of adding DemDex's audience-optimization software to its online marketing suite. At Photoshop World 2011, Adobe unveiled a new mobile photo service. Carousel was a new application for iPhone, iPad, and Mac that used Photoshop Lightroom technology to allow users to adjust and fine-tune images on all platforms. Carousel also allowed users to automatically sync, share and browse photos. The service was later renamed "Adobe Revel". Later that same year in October, Adobe acquired Nitobi Software, the maker of the mobile application development framework PhoneGap. As part of the acquisition, the source code of PhoneGap was submitted to the Apache Foundation, where it became Apache Cordova. In November 2011, Adobe announced that it would cease development of Flash Player for mobile devices following version 11.1. Instead, it would focus on HTML5 for mobile web development. In December 2011, Adobe announced that it had entered into a definitive agreement to acquire privately held Efficient Frontier. In December 2012, Adobe opened a new 280,000-square-foot (26,000 m2) corporate campus in Lehi, Utah. In 2013, Adobe endured a major security breach. Vast portions of the source code for the company's software were stolen and posted online and over 150 million records of Adobe's customers were made readily available for download. In 2012, about 40 million sets of payment card information were compromised by a hack at Adobe. A class-action lawsuit alleging that the company suppressed employee compensation was filed against Adobe, and three other Silicon Valley–based companies in a California federal district court in 2013. In May 2014, it was revealed the four companies, Adobe, Apple, Google, and Intel had reached an agreement with the plaintiffs, 64,000 employees of the four companies, to pay a sum of $324.5 million to settle the suit.
Adobe's currently supported roster of software, online services and file formats comprises the following (as of October 2022): On October 3, 2013, the company initially revealed that 2.9 million customers' sensitive and personal data was stolen in a security breach which included encrypted credit card information. Adobe later admitted that 38 million active users have been affected and the attackers obtained access to their IDs and encrypted passwords, as well as to many inactive Adobe accounts. The company did not make it clear if all the personal information was encrypted, such as email addresses and physical addresses, though data privacy laws in 44 states require this information to be encrypted. In late 2013 a 3.8 GB file stolen from Adobe and containing 152 million usernames, reversibly encrypted passwords and unencrypted password hints was posted on AnonNews.org. LastPass, a password security firm, said that Adobe failed to use best practices for securing the passwords and has not salted them. Another security firm, Sophos, showed that Adobe used a weak encryption method permitting the recovery of a lot of information with very little effort. According to IT expert Simon Bain, Adobe has failed its customers and 'should hang their heads in shame'. Many of the credit cards were tied to the Creative Cloud software-by-subscription service. Adobe offered its affected US customers a free membership in a credit monitoring service, but no similar arrangements have been made for non-US customers. When a data breach occurs in the US, penalties depend on the state where the victim resides, not where the company is based. After stealing the customers' data, cyber-thieves also accessed Adobe's source code repository, likely in mid-August 2013. Because hackers acquired copies of the source code of Adobe proprietary products, they could find and exploit any potential weaknesses in its security, computer experts warned.
Security researcher Alex Holden, chief information security officer of Hold Security, characterized this Adobe breach, which affected Acrobat, ColdFusion and numerous other applications, as "one of the worst in US history". Adobe also announced that hackers stole parts of the source code of Photoshop, which according to commentators could allow programmers to copy its engineering techniques and would make it easier to pirate Adobe's expensive products. Published on a server of a Russian-speaking hacker group, the "disclosure of encryption algorithms, other security schemes, and software vulnerabilities can be used to bypass protections for individual and corporate data" and may have opened the gateway to new generation zero-day attacks. Hackers already used ColdFusion exploits to make off with usernames and encrypted passwords of PR Newswire's customers, which has been tied to the Adobe security breach. They also used a ColdFusion exploit to breach Washington state court and expose up to 200,000 Social Security numbers.
Adobe has violated federal and state antitrust laws by abusing its dominant position in the professional vector graphic illustration software market [...] Adobe has engaged in a series of exclusionary and anti-competitive acts and strategies designed to kill FreeHand, the dominant competitor to Adobe's Illustrator software product, instead of competing on the basis of product merit according to the principals of free market capitalism. Adobe had no response to the claims and the lawsuit was eventually settled. The FreeHand community believes Adobe should release the product to an open-source community if it cannot update it internally. As of 2010, on its FreeHand product page, Adobe stated, "While we recognize FreeHand has a loyal customer base, we encourage users to migrate to the new Adobe Illustrator CS4 software which supports both PowerPC and Intel–based Macs and Microsoft Windows XP and Windows Vista." As of 2016, the FreeHand page no longer exists; instead, it simply redirects to the Illustrator page. Adobe's software FTP server still contains a directory for FreeHand, but it is empty.
Figure 3: Healthcare Patient Portal Dashboard by Ronas IT | UI/UX Team on Dribbble Adobe MAX Digital rights management (DRM) List of acquisitions by Adobe United States v. Elcom Ltd. HealthCare.gov is a health insurance exchange website operated by the United States federal government under the provisions of the Affordable Care Act (ACA), informally referred to as "Obamacare", which currently serves the residents of the U.S. states which have opted not to create their own state exchanges. The exchange facilitates the sale of private health insurance plans to residents of the United States and offers subsidies to those who earn between one and four times the federal poverty line, but not to those earning less than the federal poverty line. The website also assists those persons who are eligible to sign up for Medicaid, and has a separate marketplace for small businesses. On October 1, 2013, HealthCare.gov was rolled out as planned, despite the concurrent partial government shutdown. The launch was marred by serious technological problems, making it difficult for the public to sign up for health insurance. The deadline to sign up for coverage that would begin January 1, 2014, was December 23, 2013, by which time the problems had largely been fixed. The open enrollment period for 2016 coverage ran from November 1, 2015, to January 31, 2016. State exchanges also have had the same deadlines; their performance has been varied. The design of the website was overseen by the Centers for Medicare and Medicaid Services and built by a number of federal contractors, most prominently CGI Inc. of Canada. The original budget for CGI was $93.7 million, but this grew to $292 million prior to launch of the website. While estimates that the overall cost for building the website had reached over $500 million prior to launch and in early 2014 HHS secretary Sylvia Mathews Burwell said there would be "approximately $834 million on Marketplace-related IT contracts and interagency agreements," the Office of Inspector General released a report in August 2014 finding that the total cost of the HealthCare.gov website had reached $1.7 billion and a month later, including costs beyond "computer systems," Bloomberg News estimated it at $2.1 billion. On July 30, 2014, the Government Accountability Office released a non-partisan study that concluded the administration did not provide "effective planning or oversight practices" in developing the HealthCare.gov website.
The site functions as a clearing house to allow Americans to compare prices on health insurance plans in their states, to begin enrollment in a chosen plan, and to simultaneously find out if they qualify for government healthcare subsidies. Visitors sign up and create their own specific user account first, listing some personal information, before receiving detailed information about what is available in their area. Designed to assist the millions of uninsured Americans, the comparison shopping features involve a visual format somewhat analogous to websites such as Amazon.com and Etsy. HealthCare.gov also details Medicaid options for individuals. This relates to an expansion of the long-running program undertaken as a joint effort under the ACA. The Congressional Budget Office (CBO) projected that the exchange would be used by an estimated seven million Americans to obtain coverage during the first year after its launch; current estimates suggest that the combined figure is slightly above eight million.
President Barack Obama signed the Affordable Care Act (ACA) into law on March 23, 2010, in the East Room before a select audience of nearly 300 people. He stated that the health reform effort, designed after a long and acrimonious debate facing fierce opposition in the Congress to expand health insurance coverage, was based on "the core principle that everybody should have some basic security when it comes to their health care". The primary purpose of the ACA was to increase coverage to the American people either through public or private insurance and control healthcare costs. The Congressional Budget Office (CBO) estimated that the ACA would reduce the number of uninsured by 32 million, increasing coverage for the non-elderly citizens from 83 to 94 percent. Insurers were not allowed to deny insurance to applicants with pre-existing conditions. The Sunlight Foundation has stated that at least forty-seven private company contractors have been involved with the ACA in some capacity as of fall 2013, with the measure causing a wide variety of policy changes. Journalists writing for The New York Times have called the ACA "the most expansive social legislation enacted in decades". A report by Reuters described HealthCare.gov itself as the "key" to the reform measure. Development of the website's interface as well as its supporting back-end services, to make sure that the website could work to help people compare between health insurance plans, were both outsourced to private companies. The front-end of the website was developed by the startup Development Seed. The back-end work was contracted out to CGI Federal Inc., a subsidiary of the Canadian IT Multinational corporation CGI Group, which subcontracted the work to other companies, as is common on large government contracts. CGI was also responsible for building some of the state-level healthcare exchanges, with varying levels of success (some did not open on schedule).
According to author and journalist John J. Xenakis, CGI Federal's attempt in Massachusetts is characterized as a complete failure. In Xenakis' view, despite the Massachusetts connector being the type of website which a small team of five to ten could create in a few months on a 10 million dollar budget, a team of around 300 with a 200 million dollar budget failed. Xenakis claims CGI Federal were likely to have hired many incompetent programmers due to Massachusetts transferring the development contract to another firm, Optum. The software created by CGI was of poor quality and unusable by Optum, who had to start from scratch. CGI has also been accused of committing fraudulent tests and reports to those in charge of oversight. Similar problems occurred in many other states. Specifically, aspects of HealthCare.gov relating to digital identity authentication were assigned to Experian. Quality Software Services, Inc. (QSSI) also played a role. The total number of companies enlisted in the website's creation, and their names, has not been disclosed by the Department of Health and Human Services. The whole effort was officially coordinated by the Centers for Medicare and Medicaid Services (CMS), an agency that commentators such as journalists David Perera and Sean Gallagher have speculated was ill-suited to that task.
Social activist and technologist Clay Johnson later said that the federal government had issues come up given that it "leans towards a write-down-all-the-requirements-then-build-to-those-requirements type of methodology" not well suited to current IT especially when government contractors are focused on maximizing profits. "The firms that typically get contracts are the firms that are good at getting contracts, not typically good at executing on them," Alex Howard, a fellow at the Harvard Ash Center for Democratic Governance and Innovation, remarked to The Verge as he evaluated the back-end of the project. In contrast, the web-magazine's journalist Adrianne Jeffries praised the successful use of an "innovative" startup business for the front-end. However, she found the overall rollout "bone-headed". The Obama administration repeatedly modified regulations and policies until summer 2013, meaning contractors had to deal with changing requirements. However, changing requirements are by no means unusual in a large, expensive custom software project; they are a well-known factor in historical project failures, and methodologies such as agile software development have been developed to cope with them.
Unfortunately, regulations pertaining to large government contracts in many countries, including the United States, are not a good match for agile software development. 2. System Architecture & Core Working Principles The HealthCare.gov website was launched on the scheduled date of October 1, 2013. Although the government shutdown began on the same day, HealthCare.gov was one of the federal government websites that remained open through the events.
Although it appeared to be up and running normally, visitors quickly encountered numerous types of technical problems, and, by some estimates, only 1% of interested people were able to enroll to the site in the first week of its operations. Even for those that did manage to enroll, insurance providers later reported some instances of applications submitted through the site with required information missing. In Bloomberg Businessweek journalist Paul Ford summed up the issue by remarking, "Regardless of your opinions on the health-care law, this is the wrong way to make software." He also wrote, "In the meantime, it's clear that tens of millions of dollars have been spent to launch something broken." A ConsumerReports.org article re-iterated previous advice, with the group recommending for people to stay "away from HealthCare.gov for at least another month". The group stated as well, "Hopefully that will be long enough for its software vendors to clean up the mess they've made." In its third week of operations, technical problems continued. A CNN.com article highlighted the "maddeningly long wait times" as an issue. A variety of other problems included broken pull-down menus that have only worked intermittently, for example. Todd Park, the U.S. chief technology officer, initially said on October 6 that the glitches were caused by unexpected high volume when the site drew 250,000 simultaneous users instead of the 50,000-60,000 expected.
He claimed that the site would have worked with fewer simultaneous users. More than 8.1 million people visited the site from October 1 to 4. White House officials subsequently conceded that it was not just an issue of volume, but involved software and systems design issues. For example, consumers are required to create an account before being able to compare plans, and the registration process may have created a bottleneck that led to the long wait times. Also, stress tests done by contractors 1 day before the launch date revealed that the site became too slow with only 1,100 simultaneous users, nowhere near even the 50,000-60,000 expected. Despite later comments, concerns about the readiness of the exchanges had been raised in March 2013, by Henry Chao, the deputy chief information officer at the Centers for Medicare and Medicaid Services (CMS), who had said that "let's just make sure it's not a third-world experience". A colleague of his, Gary Cohen, had also remarked, "Everyone recognizes that day one will not be perfect." Even by 2011, when the CMS awarded its private sector contracts, most of the ACA regulations and implementation measures were still in flux. The New York Times and The Washington Post reported in November 2013 that the Obama administration brought in consulting firm McKinsey & Company to assess the website. Their report, delivered in March 2013, warned that the effort to build the HealthCare.gov site was falling behind and was at risk of failure unless immediate steps were taken to correct the problems. On October 21, 2013, President Barack Obama addressed the technical problems and other issues in a thirty-minute press conference at the White House Rose Garden, saying that there was "no excuse" for them. He remarked, "There's no sugar coating: the website has been too slow, people have been getting stuck during the application process and I think it's fair to say that nobody's more frustrated by that than I am." He also stated that a "tech surge" was underway to fix the problems. The President additionally pointed out that people could instead apply through a call center or in person. White House Press Secretary Jay Carney said more time was needed to get the website working properly. Carney also hinted that if the problems remained unresolved for such a long time that it prevented people from meeting their legal obligation to obtain insurance in time for the February deadline, the legal penalty for not obtaining insurance would not be applicable because the Obamacare law states that if affordable care is not available, the penalty will not be payable. So, shortly after HealthCare.gov's launch, the problems still did not affect the legal requirement for Americans to have health insurance by December 15, which remained on the books as stated. However, on October 23, the effective legal deadline for applying for health insurance via HealthCare.gov without getting a penalty via the individual mandate was extended to March 31, 2014, possibly because of the problems with HealthCare.gov and some of the state healthcare exchanges (but without a de jure explanation as such given). The Obama administration appointed a contractor, Quality Software Services, Inc (QSSI), to coordinate the work of the fixing of the website problems. The company had already worked on the website's back-end before the website went live. As stated before, prior to the launch, the Centers for Medicare and Medicaid Services (CMS) had been playing the role of coordinator, but critics charged that it was ill-suited for such a systems integration role. The administration appointed Jeffrey Zients to act as their adviser in the matter. On October 25, Zients promised, in a conference call to the media, that the site would be working well "for the vast majority of users" by the end of November. He also claimed that 90% of visitors are now able to complete the account-creation process and actually used HealthCare.gov to compare plans. Perhaps the largest issue he faces, as he acknowledged in the call, are the error-riddled reports given to insurers, often messing up basic details such as an individual's gender. As stated before, HealthCare.gov problems have persisted even weeks after the launch. For example, a networking failure error at the related data services hub killed the website's functionality again October 28. This occurred the exact day after Health and Human Services head Kathleen Sebelius had highlighted the design of that data hub as a government success. However, state-based exchanges have mostly worked well in registering individuals during this time period, with CNN.com describing them as "largely error free". A large number of technical fixes took place through October and November, with an NPR.org report later remarking that the website seemed to be "working more smoothly." Yet, on November 13, the Obama administration revealed that fewer than 27,000 people had signed up to private health insurance through the site. By November 30, more than 137,000 people had obtained health insurance through the federal website. That figure represented a strong increase, but enrollment figures were still vastly below past U.S. government forecasts. Accenture was chosen to replace CGI Group as the lead contractor for the website in January 2014. A large issue with future enrollments is dealing with the accuracy of HealthCare.gov information sent to insurance companies. As stated in an NPR.org article citing "continuing problems" with HealthCare.gov, about one in ten enrollment notices have contained a significant error.
The technical problems were heavily criticized, and Republican representatives sent President Obama a list of questions, demanding explanations for what went wrong. Some Republicans called for the Secretary of Health and Human Services, Kathleen Sebelius, to be fired, because she oversaw the planning for the site launch. Former White House Press Secretary Robert Gibbs described the technical problems as "excruciatingly embarrassing", and he said that some people should be fired. Scott Amey of the Project on Government Oversight pointed to the development cost ceiling being raised from $93.7 million to $292 million, and he asked: "Where was the contract oversight?" American conservative commentators such as National Review writers Jonah Goldberg and Mark Steyn have argued that the website's launch was a disaster that presages larger problems throughout the entire law, with Goldberg asserting that "the Republicans who insisted that this monstrosity had to be delayed are looking just a little bit more reasonable with every passing tick." In a statement, the Republican National Committee (RNC) responded to President Obama's comments that the "tech surge" was code for a "spending surge" and will waste millions of dollars. Said statement also read, "The federal bureaucracy has proven itself too slow, too bloated, too incompetent, and too outdated to manage America's health care." Speaker of the House John Boehner, a Republican Representative from Ohio, told reporters that throughout November "more Americans are going to lose their health care than are going to sign up." Ohio Governor John Kasich stated on NBC's Meet the Press program on October 27 that the roll-out has "got everybody just shaking their heads". He also added that it seemed highly likely that most Ohioans would pay more on the HealthCare.gov plans. Kentucky Governor Steve Beshear counter-argued that while the website didn't work well yet that it soon would since HealthCare.gov represents "the future of health care", and he commented as well, "You know, the advice I would give the news media and the critics up here is take a deep breath." The Daily Show host Jon Stewart notably lampooned the HealthCare.gov controversy during an interview with Sebelius. He jokingly challenged her to an online race: "I'm going to try and download every movie ever made, and you're going to try to sign up for Obamacare, and we'll see which happens first." She also faced grilling over the Obama administration's opposition to an extended individual mandate delay.
Sebelius later said in response to criticism, "The majority of people calling for me to resign I would say are people who I don't work for and who do not want this program to work in the first place". She also said, "I have had frequent conversations with the President and I have committed to him that my role is to get the program up and running, and we will do just that." Her popularity in her native Kansas where she previously served as governor, according to University of Kansas political science professor Burdett Loomis, has spurred her on to stay on. U.S. House Minority Leader Nancy Pelosi, a Democratic Representative from California, commented about the controversy that she feels optimistic about things being fixed, saying "I have faith in technology" as well as "while there are glitches, there are solutions, as well." Democrats in Congress have accused Republican critics of HealthCare.gov of acting in bad faith. "We want the process to improve, but we're not interested in torpedoing the process," said Representative Xavier Becerra, another Democrat from California and chairman of the House Democratic Caucus. Republican Senator Marco Rubio has drafted legislation as a result of the controversy to delay the individual mandate. The proposed legislation has drawn scattered Democratic support. Professor and author Victor Lombardi commented to Bloomberg Businessweek that the website's issues "don't sound catastrophic", and he added that history "may judge this project as the catalyst that revolutionized the United States health-care system" such that "no one will remember a few hiccups at launch." Although the law that decreed the creation of HealthCare.gov has been divisive and political speculation has taken place, polling done by the Gallup organization around the time of the difficult roll-out still have found that a majority of Americans support keeping at least some aspects of Obamacare. Specifically, just 29% of the public favoured a complete repeal. However, a joint The Washington Post and ABC News survey stated that 56% of respondents consider the website's problems a harbinger of other problems with the health care measure. On October 29, 2013, Rep. Lee Terry (R, NE-2) introduced the Exchange Information Disclosure Act. The bill would require the United States Department of Health and Human Services to submit weekly reports to Congress about the how many people are using HealthCare.gov and signing up for health insurance. These reports would be due every Monday until March 31, 2015, and would be available to the public.
The bill would "require weekly updates on the number of unique website visitors, new accounts, and new enrollments in a qualified health plan, as well as the level of coverage," separating the data by state. The bill would also require reports on efforts to fix the broken portions of the website. The House was scheduled to vote on it on January 10, 2014. Kathleen Sebelius resigned as Secretary of Health and Human Services on April 10, 2014. She was replaced by Sylvia Mathews Burwell on June 9.
Centers for Medicare and Medicaid Services eHealthInsurance Health care in the United States Health care reform in the United States Health care reforms proposed during the Obama administration Health insurance coverage in the United States Health insurance marketplace List of failed and overbudget custom software projects The Mythical Man-Month Provisions of the Patient Protection and Affordable Care Act United States Department of Health and Human Services Building a secure, compliant healthcare web portal means designing for privacy and reliability from the first line of code: encrypt patient data in transit and at rest, enforce role-based access control with least-privilege defaults, log every access to sensitive records, and plan early for the regulations that apply to you (India's DPDP Act for domestic operations, HIPAA for US-facing clients). Security and compliance are architecture decisions, not features you bolt on at the end.
This article walks through the approach we take to healthcare web development at StackOrbit Labs — the engineering trade-offs, the data-protection layers, and the compliance considerations to plan for. It is a practical guide, not legal advice; for regulatory sign-off, work with a qualified compliance or legal advisor. Most business web apps optimise for conversion and speed. A healthcare portal carries an additional, non-negotiable weight: the data it handles can harm a real person if it leaks, and the system has to keep working when someone needs it at 2 a.m.
If you are weighing whether to build custom or buy off-the-shelf, our guide on SaaS development timelines, costs, and when to build your own product covers that trade-off in detail. The guiding principle is separation and containment : keep sensitive data isolated, minimise where it travels, and make every component assume the others might be compromised.
For Indian deployments, also consider data residency — keeping patient data hosted within India (most major cloud providers offer Mumbai or Hyderabad regions) simplifies your DPDP posture and reduces latency for users across Tamil Nadu and the rest of the country. Data protection in a healthcare portal is layered. No single control is sufficient; the strength comes from combining them.
Every byte of patient data should be encrypted on the wire (TLS 1.2 or higher, enforced — no plaintext fallback) and on disk. Managed databases and object storage from major providers offer encryption at rest with little overhead; the discipline is making sure backups and exports inherit the same protection rather than slipping out as plaintext dumps. Role-based access control (RBAC) maps real-world roles — patient, doctor, nurse, receptionist, administrator — to specific permissions. Least privilege extends this to machines: the service account your app uses to query the database should be able to read and write only the tables it needs, not administer the whole server. When an account is compromised, least privilege is what keeps a single foothold from becoming a full breach.
Healthcare systems need to answer "who looked at this patient's record, and when?" That requires an append-only audit trail covering reads as well as writes to sensitive data. Crucially, audit logs themselves must not contain the sensitive data they track — log the actor, the action, the record ID, and the timestamp, not the patient's diagnosis. This is the part founders most often underestimate. Compliance is not a certificate you buy at the end; it is a set of requirements that shape design from day one. The two frameworks most relevant to healthcare portals built from India are: The Digital Personal Data Protection Act, 2023 (DPDP Act) governs how personal data of individuals in India is collected, processed, and stored. Health data is sensitive, so the practical implications include obtaining clear consent, collecting only what you need (data minimisation), giving users rights over their data, securing it appropriately, and being prepared to report breaches. Building consent capture, data-access requests, and deletion workflows into the portal from the start is far cheaper than retrofitting them.
If your portal serves patients or providers in the United States, HIPAA (the Health Insurance Portability and Accountability Act) applies. It sets standards for safeguarding protected health information through administrative, physical, and technical safeguards — encryption, access controls, audit controls, and Business Associate Agreements with vendors who touch the data. Many Indian agencies serve US healthcare clients; if that is your market, HIPAA shapes your hosting choices, your vendor contracts, and your logging from the outset.
A grounding caveat: the items below are engineering considerations to plan for, not a compliance checklist or legal opinion . Regulations evolve, and how they apply depends on your specific data, users, and jurisdiction. Validate your approach with a qualified legal or compliance professional before going live. 3. Software Implementation, Frameworks & Protocols Security and usability are often framed as opposites. In healthcare they are not — a portal that is hard to use gets bypassed, and bypassed security is no security at all. The two audiences have different needs.
For patients , the priorities are clarity and trust. Plain-language labels, a simple appointment and records flow, accessible design (proper contrast, keyboard navigation, screen-reader support), and mobile-first layouts — a large share of Indian users will access the portal from a phone on a mobile connection. Strong authentication should be frictionless: OTP and well-implemented multi-factor that protects without frustrating.
For staff , the priorities are speed and accuracy. Clinicians work under time pressure, so the interface must surface the right information fast, prevent data-entry errors with validation, and make audit-relevant actions obvious. Role-aware interfaces help here: staff see only what their role permits, which both protects data and reduces clutter. Done well, the security model is mostly invisible to the people using the portal — they experience a fast, clear, reliable tool, while the protection works quietly underneath.
It depends heavily on scope. A focused portal can start in the range of a custom web application from around Rs 50,000 , while a full-stack healthcare solution with multiple roles, integrations, audit logging, and compliance workflows typically starts from about Rs 1,00,000. Pricing scales with the number of user roles, third-party integrations (labs, payments, messaging), and the depth of compliance work required, so a scoped quote is the only honest figure. Tell us about your project for an estimate.
Yes. React and Next.js are well suited to healthcare portals because they let you keep sensitive logic server-side, render securely, and build fast, accessible interfaces. Security comes from architecture and discipline — where data lives, how it is encrypted, and how access is controlled — not from the framework itself. The stack is a strong foundation; the engineering practices around it are what make it compliant.
Only if your portal handles protected health information of individuals in the United States, or you serve US healthcare providers. For purely domestic Indian operations, India's DPDP Act is the primary framework. Many Coimbatore and Tamil Nadu agencies serve both markets, so it is common to design for DPDP and HIPAA together. Confirm your obligations with a compliance professional, as this is a planning consideration rather than legal advice.
A minimal viable portal can take a few weeks; a full-featured, compliance-ready system with multiple roles and integrations usually runs several months. The compliance and security work — threat modelling, access control design, audit logging, testing — is a meaningful share of the timeline and should not be compressed. The hardest part of healthcare web development is not writing the code — it is the discipline to make privacy, security, and reliability structural rather than optional. Get the architecture, data protection, and compliance posture right at the start, and the portal becomes something patients and clinics can genuinely trust.
If you are planning a healthcare portal or any sensitive web application and want a partner who treats security as a first-class concern, explore our web development services or get in touch with the team in Coimbatore to talk through your requirements. What HIPAA requires for patient portal security: encryption, MFA, access controls, audit logs, and BAAs explained. Get a free compliance assessment.
Patient portals give patients direct online access to their medical records, test results, appointment scheduling, billing, and secure messaging with providers. For any medical practice offering that access, every piece of information flowing through the portal qualifies as electronic protected health information (ePHI), and every aspect of how that portal is built, managed, and monitored falls under the HIPAA Security Rule (45 CFR Part 164) .
The HHS Office for Civil Rights (OCR) has confirmed in enforcement guidance that patient portals are covered systems. A misconfigured portal, a vendor without a signed Business Associate Agreement (BAA), or inadequate access controls can result in a reportable breach, one that triggers patient notification obligations, OCR investigation, and potential civil monetary penalties.
This guide breaks down what HIPAA specifically requires for medical practice patient portal security, the most common compliance gaps OCR investigators find, and the controls your practice needs to have operational. For a broader overview of the regulatory framework, see our HIPAA cybersecurity requirements guide . The HIPAA Security Rule organizes security obligations into three categories: technical safeguards, administrative safeguards, and physical safeguards. All three apply to your patient portal environment, even when the portal is hosted by a third-party vendor. NIST Special Publication 800-66 Revision 2 provides detailed implementation guidance for each category, written specifically for healthcare covered entities.
Technical safeguards are the controls embedded directly in technology systems. For patient portals, four specifications carry direct applicability: HIPAA designates encryption at rest as "addressable" rather than "required", a distinction that trips up many practices. Addressable means you must implement the control or document, in writing, why an equally protective alternative provides the same level of protection. OCR has cited inadequate encryption in multiple enforcement actions. For any system storing ePHI, including your patient portal database, AES-256 encryption at rest is the de facto industry standard. Verify your portal vendor's encryption documentation before signing any agreement.
4. Practical Deployment, Analysis & Case Studies For a deeper look at securing health records at the system level, see our resource on healthcare data breach prevention . Multi-factor authentication (MFA) does not appear by name in the HIPAA Security Rule, the regulation predates widespread MFA adoption. However, OCR's enforcement posture and the HHS 405(d) Healthcare Industry Cybersecurity Practices publication both treat MFA as an expected control for any externally accessible system containing ePHI.
For staff access to the portal backend, treat MFA as non-negotiable. For patient-facing portal access, enabling MFA by default reduces credential theft exposure significantly. Our post on password managers and credential hygiene covers recommendations that apply directly to healthcare portal accounts. The HIPAA minimum necessary standard (45 CFR §164.502(b)) requires staff to access only the ePHI needed to perform their job functions. In a patient portal environment, this translates to role-based access control (RBAC) with distinct permission sets for each staff category: When evaluating patient portal vendors, confirm that RBAC configuration is available and that access changes require a formal, documented approval process, not just an administrator toggle.
HIPAA requires automatic logoff under the access control standard (§164.312(a)(2)(iii)). For staff-facing portal interfaces, sessions should terminate after 15 minutes of inactivity. Patient-facing sessions can extend to 30-60 minutes, but indefinite sessions leave open the risk of unauthorized access on shared or unattended devices, a common scenario in home settings where patients access portals on shared family computers.
Complete a practice-specific risk analysis (§164.308(a)(1)) covering all ePHI the portal stores, transmits, and receives. Identify threats, assess likelihood and impact, and assign residual risk ratings with remediation timelines. Obtain signed Business Associate Agreements before any ePHI flows through the vendor's system. Include subcontractors, cloud hosting providers used by your portal vendor must also be covered.
Assign unique user IDs, implement role-based access control, enforce MFA for all staff, and set session timeouts at 15 minutes for staff interfaces and 30-60 minutes for patient-facing sessions. Activate ePHI access logging and establish a documented schedule for log review. Retain logs for a minimum of six years under HIPAA's documentation retention requirement.
Confirm AES-256 encryption at rest and TLS 1.3 for all ePHI in transit. Request written documentation of encryption controls from your vendor before go-live. Deliver annual documented security awareness training covering phishing, password management, and incident reporting. Test your contingency and breach notification procedures at least annually.
HIPAA's administrative safeguards (45 CFR §164.308) govern how your practice manages ePHI security at the organizational level. For patient portals, three requirements carry the most enforcement weight. OCR has cited failure to conduct an adequate risk analysis in the majority of its published resolution agreements. This is not a vendor-provided questionnaire or a pre-filled template, it is a documented, practice-specific assessment. For a patient portal, your risk analysis must: A static risk analysis that predates your current portal configuration is not compliant. The analysis must be updated whenever you make material changes, adding integrations, switching vendors, or expanding patient-facing features all qualify as triggering events. Our healthcare risk assessment service helps practices meet this requirement with a thorough, OCR-defensible methodology.
Every staff member who accesses the patient portal must receive documented security awareness training. OCR routinely requests training records during investigations following a breach. Training must cover phishing recognition , password management, and incident reporting procedures, and must be repeated at least annually. Your portal requires a documented data backup plan and a disaster recovery procedure. If your vendor experiences an outage, staff need written procedures for handling patient communications and access requests during downtime. Review your vendor's uptime SLA and business continuity commitments as part of your BAA review process.
5. Performance Evaluation & Extended Technical Observations Mental health and behavioral health practices face additional access control requirements for sensitive psychotherapy notes. Our guide on HIPAA cybersecurity requirements covers the specific obligations that apply to behavioral health ePHI accessed through a portal.
Nearly every patient portal in a medical practice today is operated by a third-party software vendor. Under HIPAA (45 CFR §164.308(b)), any vendor that creates, receives, maintains, or transmits ePHI on your behalf is a business associate, and a signed BAA must exist before ePHI flows through that vendor's system. There is no grace period. Your practice, as the covered entity, is responsible for ensuring the agreement is in place and contains all required provisions.
For a detailed breakdown of required agreement provisions, see our guide on HIPAA cybersecurity requirements for covered entities . Vendor marketing materials and self-reported "HIPAA compliant" claims are not substitutes for documented security controls. Before finalizing any agreement involving ePHI, request: Specialty practices, including cosmetic medical spas and aesthetic medicine providers, face the same patient portal security obligations as traditional medical offices. Our post on HIPAA compliance for dental offices covers how the Security Rule applies in adjacent specialty settings.
Physical safeguards under HIPAA (45 CFR §164.310) apply to any physical environment where ePHI is accessed or stored. For a patient portal, the most directly relevant concerns are workstation security and mobile device controls. Workstations used to access the portal backend must have screen locks active, be positioned to prevent unauthorized viewing of patient data, and be governed by a written workstation use policy. In shared clinical spaces, check-in desks, nursing stations, shared exam room terminals, privacy screens for monitors displaying ePHI are a practical control that many practices overlook until an OCR investigation highlights the gap.
If staff access the portal on mobile devices, those devices require enrollment in a mobile device management (MDM) solution, remote wipe capability in the event of loss or theft, and full-disk encryption. A documented bring-your-own-device (BYOD) policy must be in place and acknowledged by all staff with portal access. Many practices simplify this obligation by restricting portal admin access to managed, practice-owned devices only.
For cloud-hosted portals, your physical safeguard obligations at the data center layer transfer to your vendor, which makes the BAA and SOC 2 Type II report essential documents. Verify that the SOC 2 scope includes physical data center security for the facilities hosting your ePHI. Understanding network segmentation also helps you isolate portal traffic from other clinical systems on your office network, a step that limits exposure when a workstation or shared network resource is compromised. Our post on EDR vs. MDR vs. XDR explains how endpoint detection solutions fit into a layered HIPAA security posture for practices with multiple devices accessing the portal.
OCR cites failure to conduct an adequate risk analysis in the majority of its published resolution agreements. A risk analysis completed before your current portal was deployed, or one based on a vendor-provided template, does not satisfy this requirement. Your practice must document a current, practice-specific analysis that reflects the actual ePHI flows through your portal today. Failure to maintain an up-to-date risk analysis is one of the fastest paths to a significant OCR settlement.
HIPAA requires covered entities to retain documentation of policies, procedures, and actions taken, including audit logs, for a minimum of six years from the date of creation or the date when the document was last in effect, whichever is later (45 CFR §164.316(b)(2)). Log review is not optional. Your practice must have a documented schedule for examining audit logs and a process for escalating anomalies, such as after-hours access, unusual geographic logins, or access patterns inconsistent with a staff member's role. Many practices use a managed security service to automate log correlation and anomaly detection rather than relying on manual review.
If your portal vendor retains logs on your behalf, confirm in writing that the retention period meets HIPAA's six-year requirement and that you have the ability to retrieve logs during an OCR investigation or internal review. Vendor-controlled log deletion on a shorter retention schedule has created compliance exposure in past OCR cases. Patient portals are fully subject to the HIPAA Security Rule. Technical safeguards, administrative safeguards, and physical safeguards all apply, regardless of whether your portal is hosted in-house or by a third-party vendor. A signed BAA, current risk analysis, MFA for staff, AES-256 encryption, and at least six years of audit log retention are the baseline controls OCR expects to find in place.
Bellator Cyber Guard's healthcare security specialists review your patient portal configuration, vendor agreements, and HIPAA documentation to identify compliance gaps before OCR does. Yes. Patient portals store and transmit electronic protected health information (ePHI), which makes them covered systems under the HIPAA Security Rule (45 CFR Part 164). The HHS Office for Civil Rights has confirmed in enforcement guidance that patient portals are subject to all three categories of HIPAA safeguards: technical, administrative, and physical. This applies regardless of whether the portal is operated by the practice directly or hosted by a third-party vendor.
Harvested Online Documentation & Reference Sources • https://en.wikipedia.org/wiki/HTTPS • https://en.wikipedia.org/wiki/Adobe%20Inc. • https://en.wikipedia.org/wiki/HealthCare.gov • https://www.stackorbitlabs.com/blog/healthcare-web-portal-approach • https://bellatorcyber.com/blog/medical-practice-patient-portal-security-requirements-hipaa
Extracted Research Figures & Simulation Topologies
Total 3 diagrams and telemetry visual outputs extracted directly from the complete technical documentation.


Breach Emulation & Defense Validation Architecture
Standardized testing pipeline mapping threat vectors directly into simulated inspection engines.
(AttackIQ / SafeBreach)
(Burp Suite Pro)
(Cisco Packet Tracer)
(Metasploit Engine)
(KnowBe4 Training)
Sample Simulation Code & Telemetry Log
Automated tool orchestration script and command window outputs for Secure Healthcare Web Portal With Encrypted Records.
[*] Initializing Burp Suite Spider & Vulnerability Engine for Secure Healthcare Web Portal With Encrypted Records... [✓] Burp Extender / Macro Automation Hook Synced ──────────────────────────────────────────────────────────────────────── [11:42:01.104] AUDIT Crawled dynamic endpoints | Injecting input vectors [11:42:01.218] FINDING Cymulate / Burp: Input sanitation check executed in parameter 'q' [11:42:01.312] VERIFY SafeBreach payload validation: Out-of-band interaction confirmed [11:42:01.405] REPORT Severity: Evaluated | Remediation: Enforce context-aware validation ──────────────────────────────────────────────────────────────────────── [✓] Burp Suite Audit Completed: Verified across OWASP Top 10 vectors
| Vulnerability Vector | Testing Tool | Injection Target | Severity | Remediation Status |
|---|---|---|---|---|
| SQL Injection (SQLi) | Burp Suite Professional | POST /api/auth/login | CRITICAL | PARAMETERIZED |
| Cross-Site Scripting (XSS) | SafeBreach / Cymulate | GET /search?q= | HIGH | CSP ENFORCED |
| Broken Object Level Access | Picus Security Audit | GET /user/account/840 | HIGH | RBAC APPLIED |
| Security Misconfiguration | AttackIQ Suite | HTTP Security Headers | MEDIUM | RESOLVED |